
















Copyright: ©Author(s) 2026.
World J Clin Cases. Sep 16, 2026; 14(26): 126833
Published online Sep 16, 2026. doi: 10.12998/wjcc.126833
Published online Sep 16, 2026. doi: 10.12998/wjcc.126833
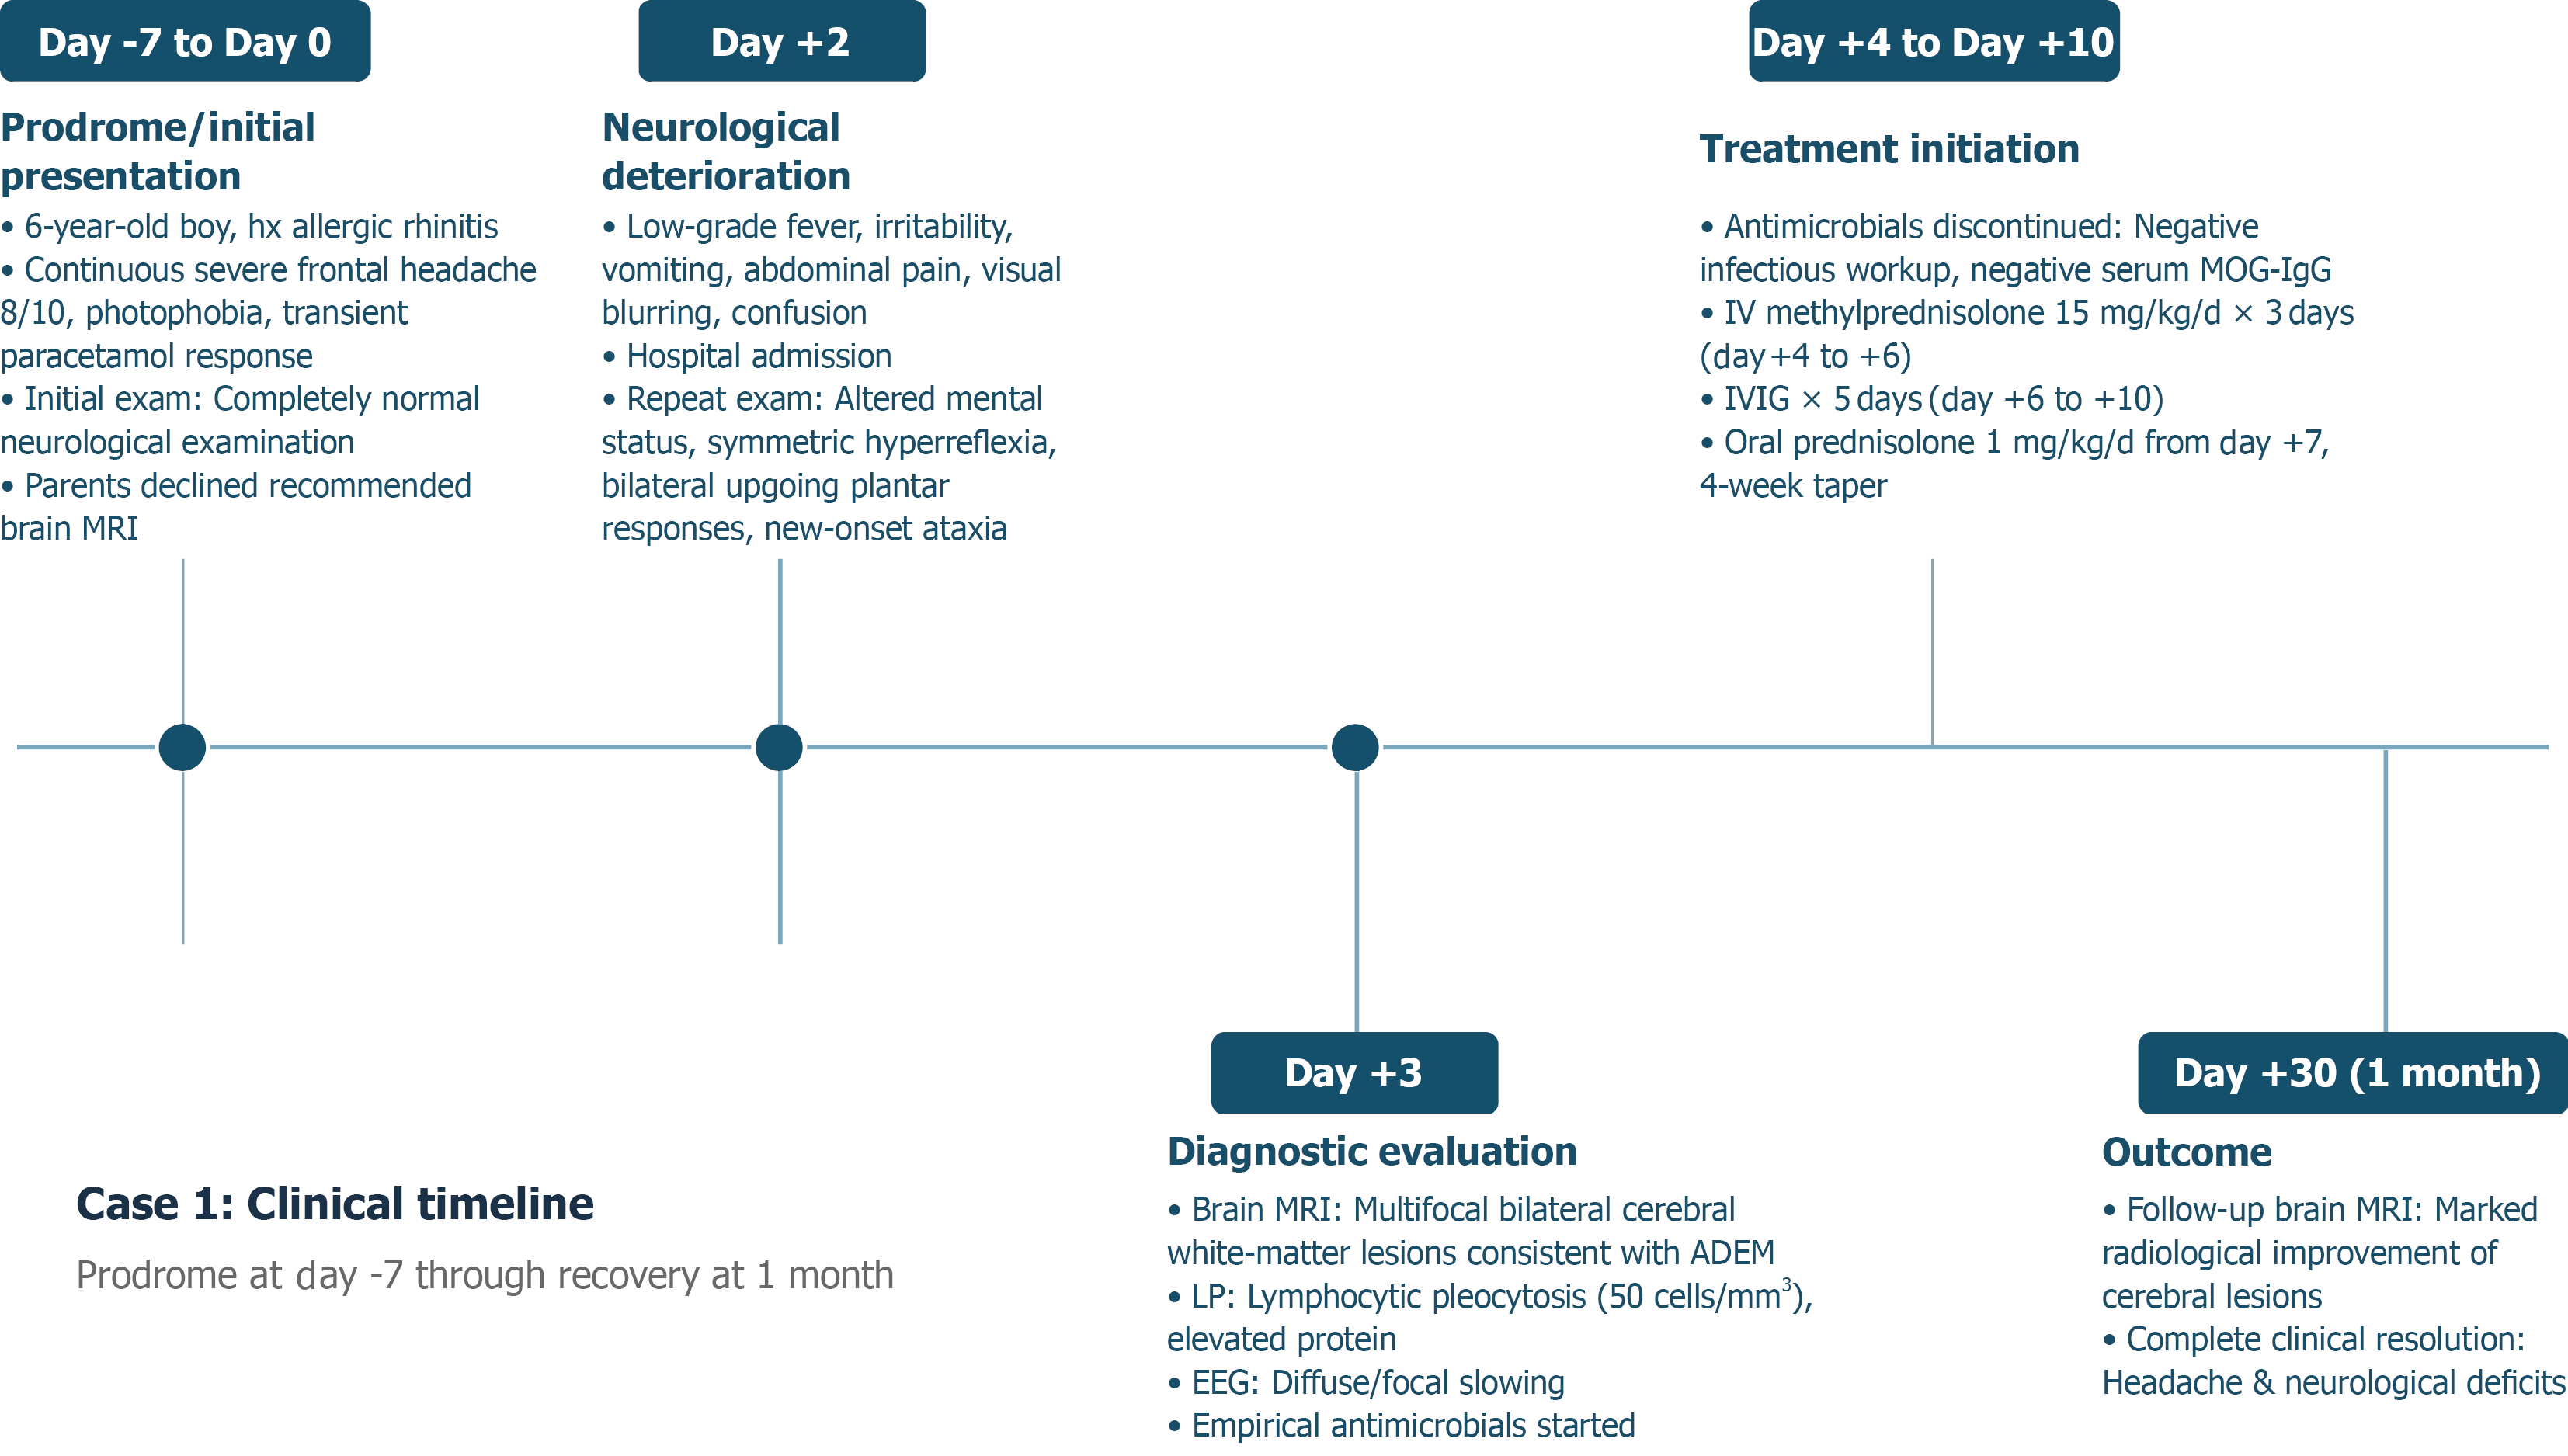
Figure 1 Comprehensive clinical and chronological timeline for case 1.
Illustrating the progression from prodromal headache (day -7) through clinical deterioration, diagnostic evaluation, acute immunomodulatory therapy (intravenous methylprednisolone and intravenous immunoglobulin), and 1-month follow-up resolution. MOG-IgG: Myelin oligodendrocyte glycoprotein immunoglobulin G; IVIG: Intravenous immunoglobulin; MRI: Magnetic resonance imaging; EEG: Electroencephalography; ADEM: Acute disseminated encephalomyelitis.
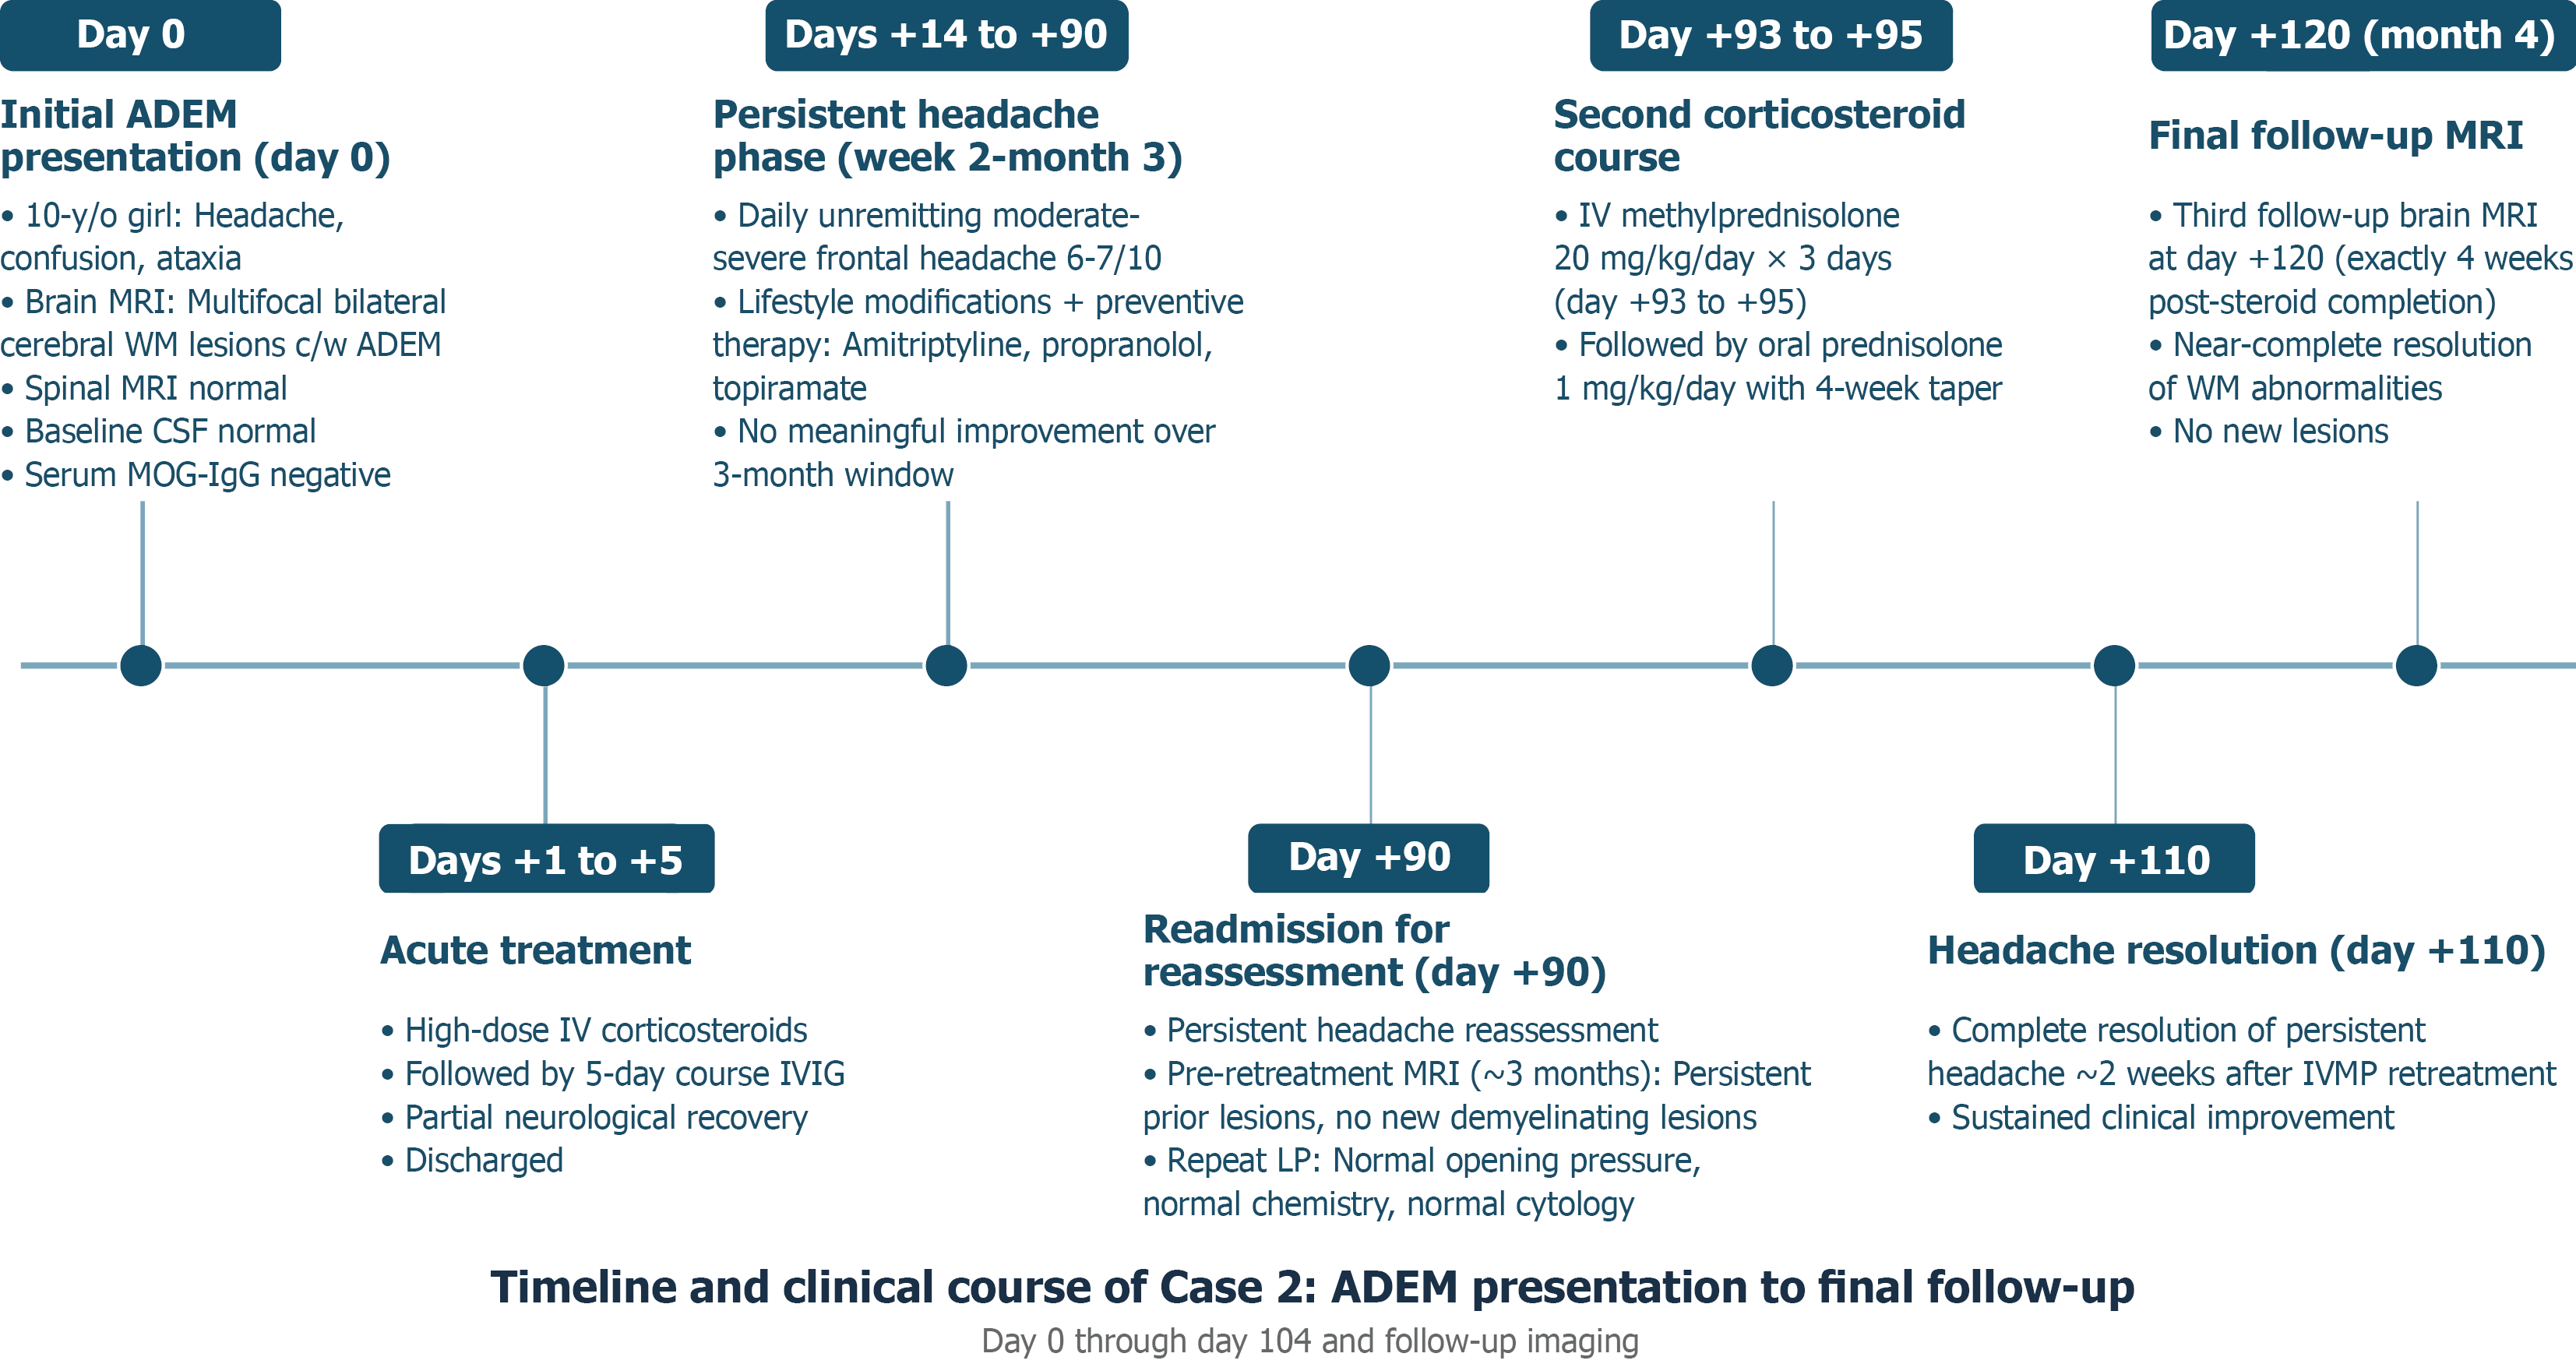
Figure 2 Comprehensive clinical and chronological timeline for case 2.
Detailing the entire trajectory from initial acute disseminated encephalomyelitis presentation (day 0), acute treatment, the 3-month persistent headache and preventive medication window (days +14 to +90), readmission assessment (day +90), repeat corticosteroid course (days +93 to +95), subsequent headache resolution (approximately day +110), to final follow-up imaging (day +120). MRI: Magnetic resonance imaging; ADEM: Acute disseminated encephalomyelitis; CSF: Cerebrospinal fluid; MOG-IgG: Myelin oligodendrocyte glycoprotein immunoglobulin G; IVIG: Intravenous immunoglobulin; IVMP: Intravenous methylprednisolone; IV: Intravenous.
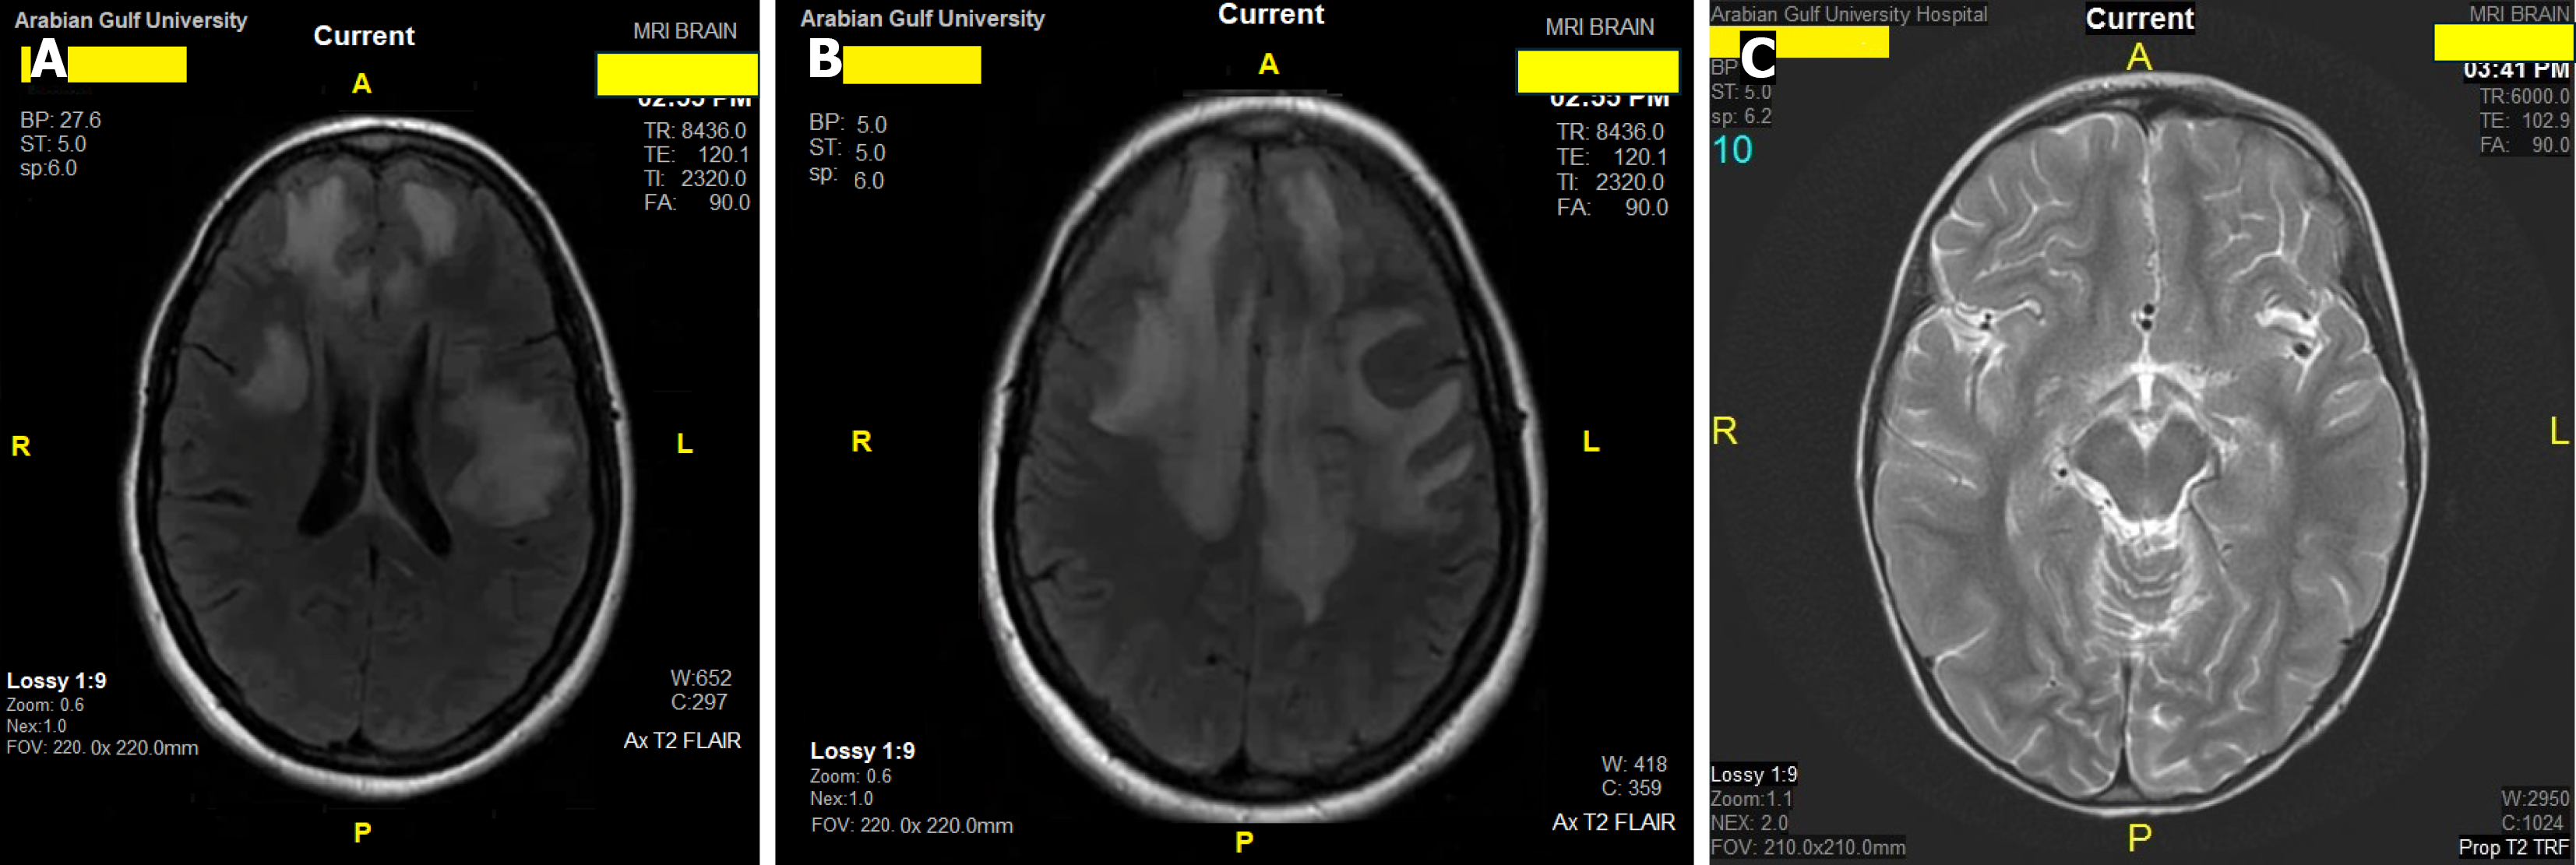
Figure 3 Case 1.
A and B: Axial T2-weighted fluid-attenuated inversion recovery brain magnetic resonance imaging (MRI) of case 1 obtained during initial acute presentation (day +3). Demonstrating multiple large, asymmetric white-matter lesions with poorly defined margins and relative periventricular sparing, accompanied by bilateral fairly symmetric hyperintensities involving the basal ganglia (more prominent on the left) with mild mass effect and no restricted diffusion. Institutional metadata has been de-identified in accordance with privacy guidelines; C: Axial T2-weighted brain MRI of case 1 obtained at 1-month follow-up (day +30). Demonstrating marked interval radiological improvement and near-complete resolution of the previously observed cerebral white-matter and basal ganglia abnormalities. Institutional metadata has been de-identified. FLAIR: Fluid-attenuated inversion recovery.
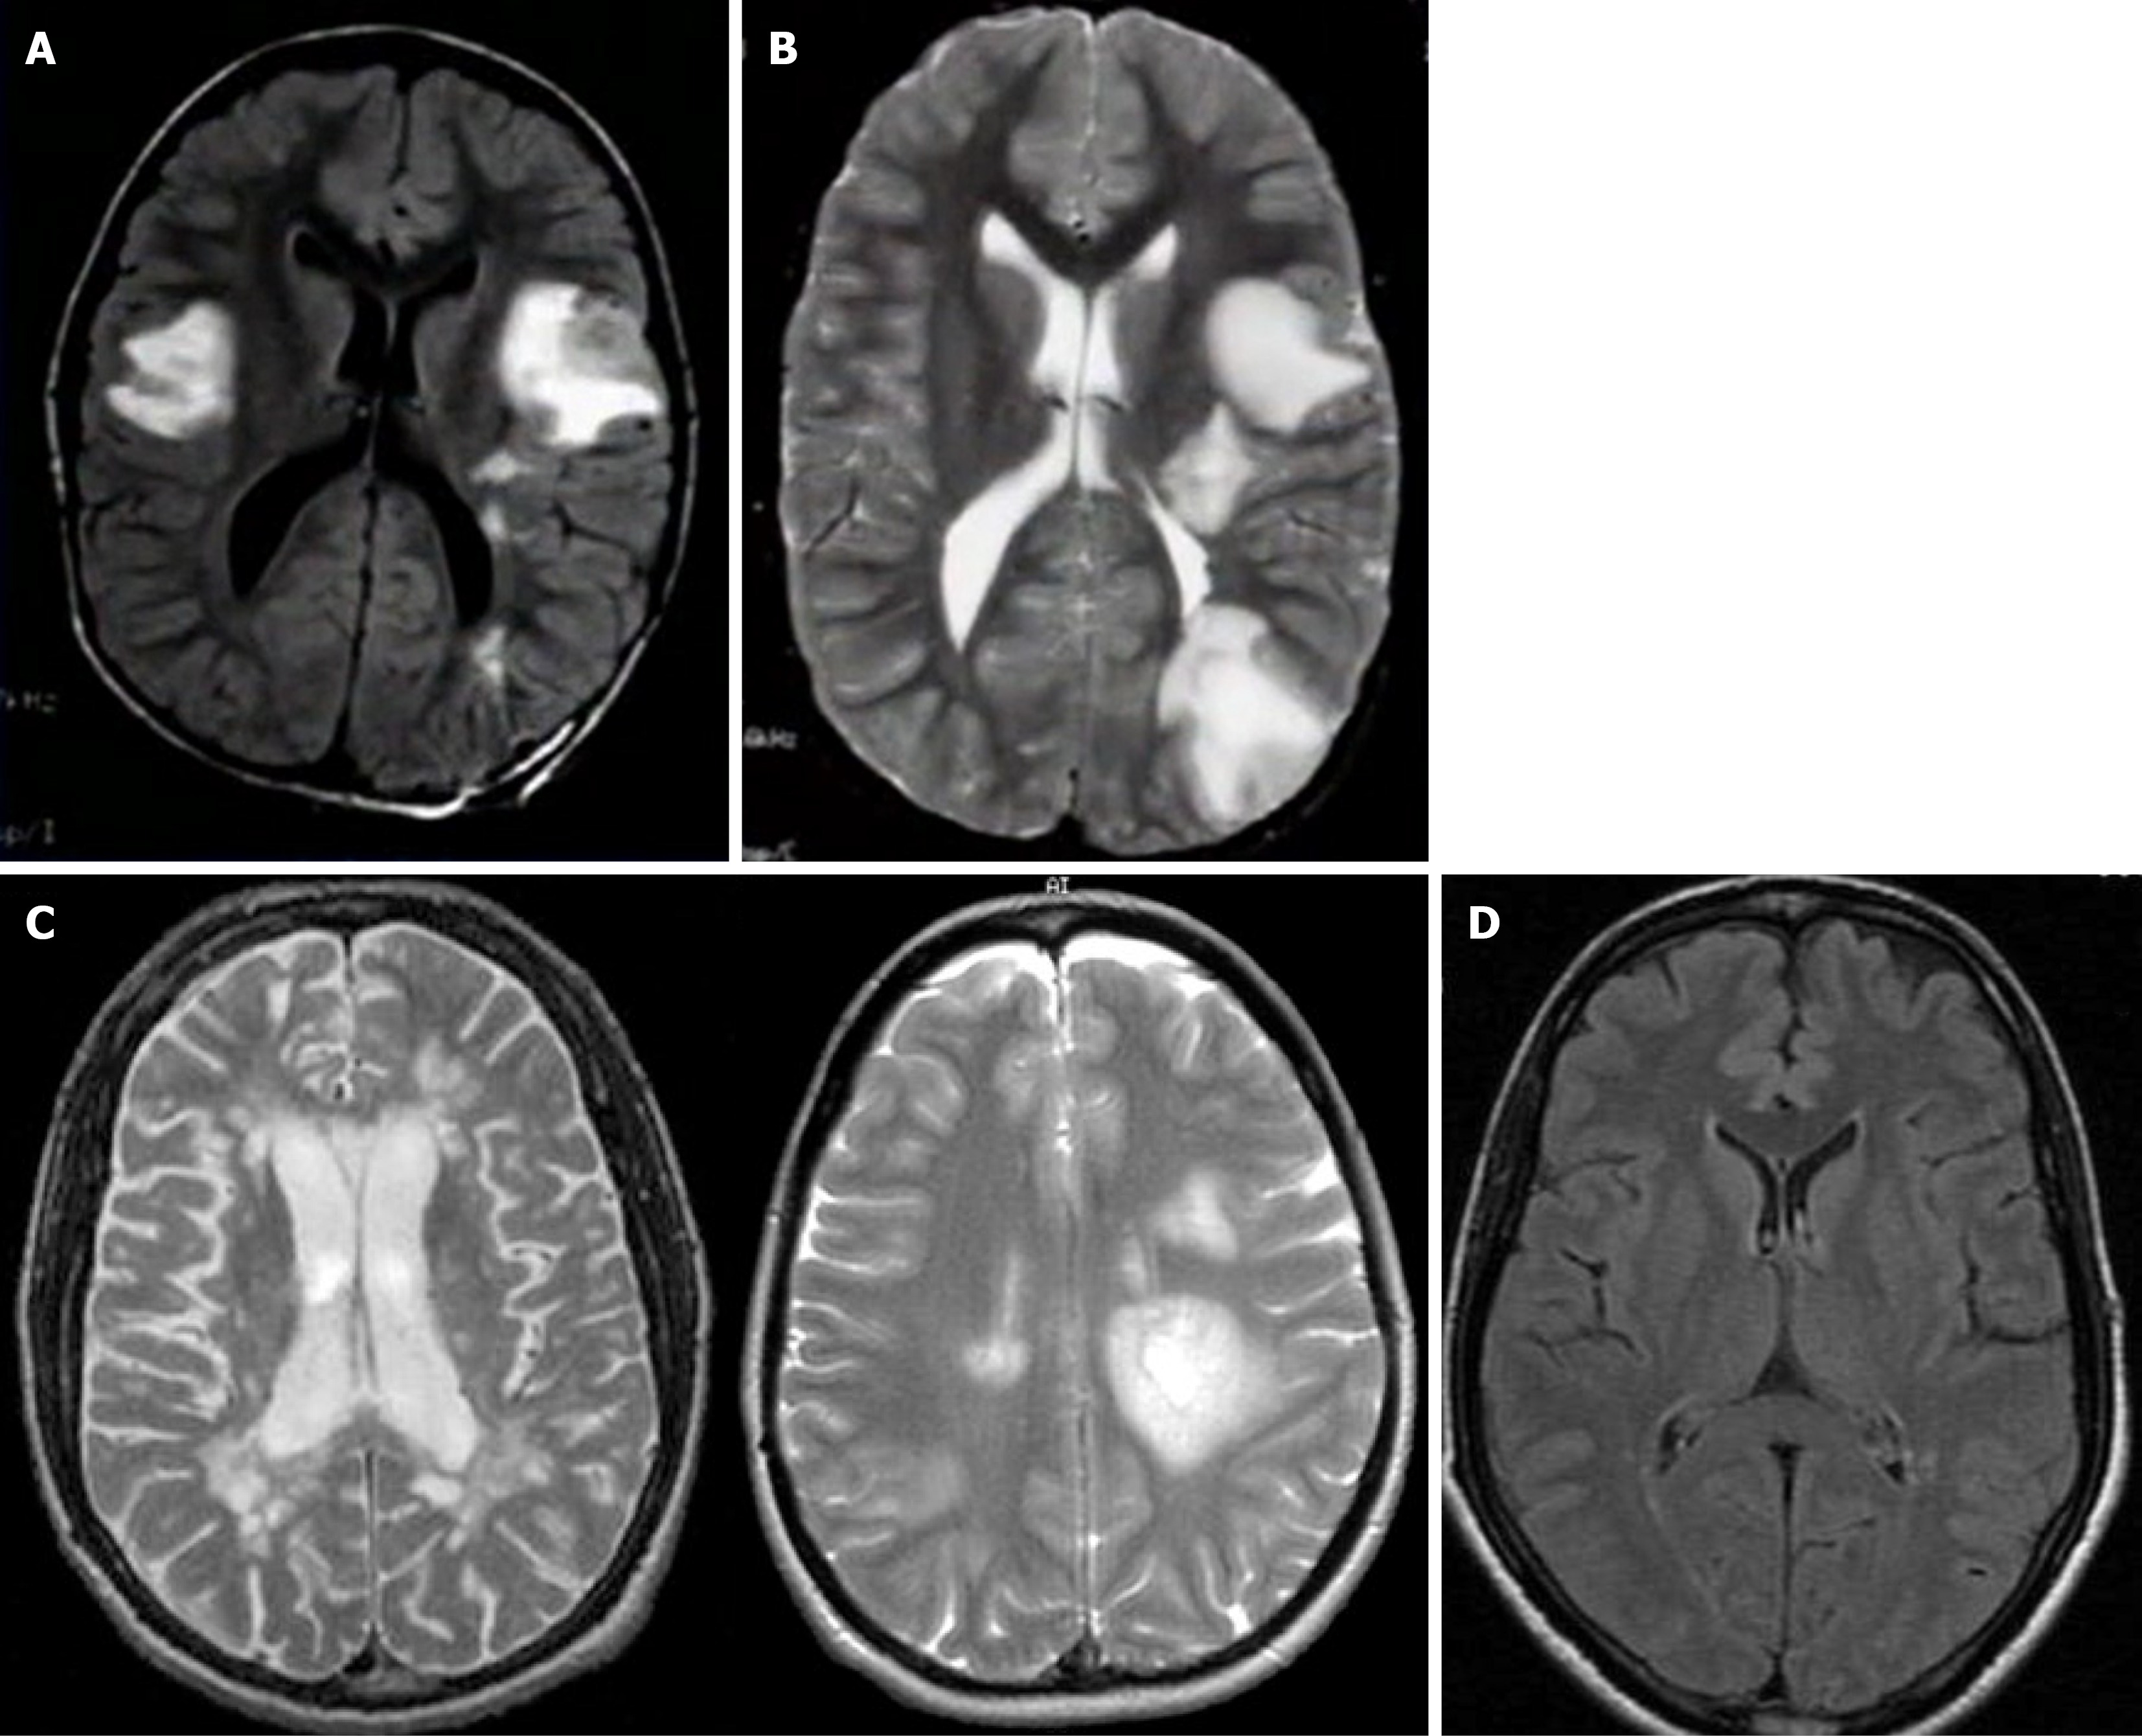
Figure 4 Case 2.
A and B: Brain magnetic resonance imaging (MRI) of case 2 at initial acute presentation (day 0). Axial T2-weighted fluid-attenuated inversion recovery (FLAIR) sequence (A) and axial T2-weighted fast spin-echo sequence (B), both demonstrating large, confluent, poorly marginated bilateral cerebral white-matter hyperintensities consistent with acute disseminated encephalomyelitis, with no restricted diffusion or pathological contrast enhancement; C: Pre-retreatment follow-up brain MRI of case 2 obtained at 3-month readmission (day +90, before corticosteroid retreatment). Showing persistent white-matter hyperintensities without new demyelinating lesions; D: Final follow-up axial T2-weighted FLAIR brain MRI of case 2 obtained at month 4 (day +120, exactly 4 weeks following the completion of repeat corticosteroid therapy). Demonstrating near-complete resolution of the prior cerebral white-matter lesions and absence of new demyelinating activity.
- Citation: Al-Beltagi M, Nazeer JA, Elbeltagi RM. Contrasting diagnostic challenges of headache before and after acute disseminated encephalomyelitis in children: Two case reports and review of literature. World J Clin Cases 2026; 14(26): 126833
- URL: https://www.wjgnet.com/2307-8960/full/v14/i26/126833.htm
- DOI: https://dx.doi.org/10.12998/wjcc.126833