
















Copyright: ©Author(s) 2026.
World J Clin Cases. Sep 16, 2026; 14(26): 126222
Published online Sep 16, 2026. doi: 10.12998/wjcc.126222
Published online Sep 16, 2026. doi: 10.12998/wjcc.126222
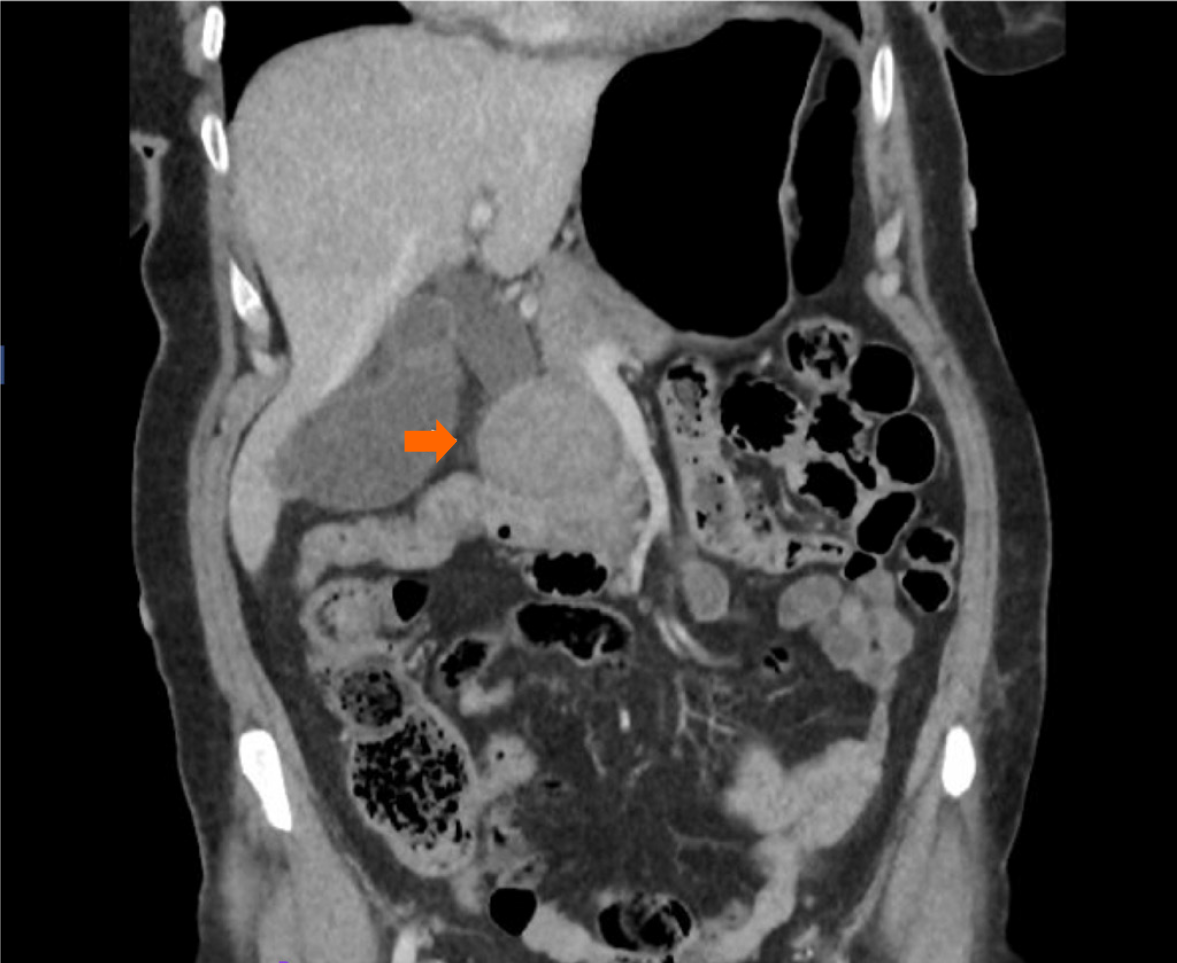
Figure 1
Coronal computed tomography of the abdomen showing a hyperdense filling defect in the common bile duct (arrowhead).
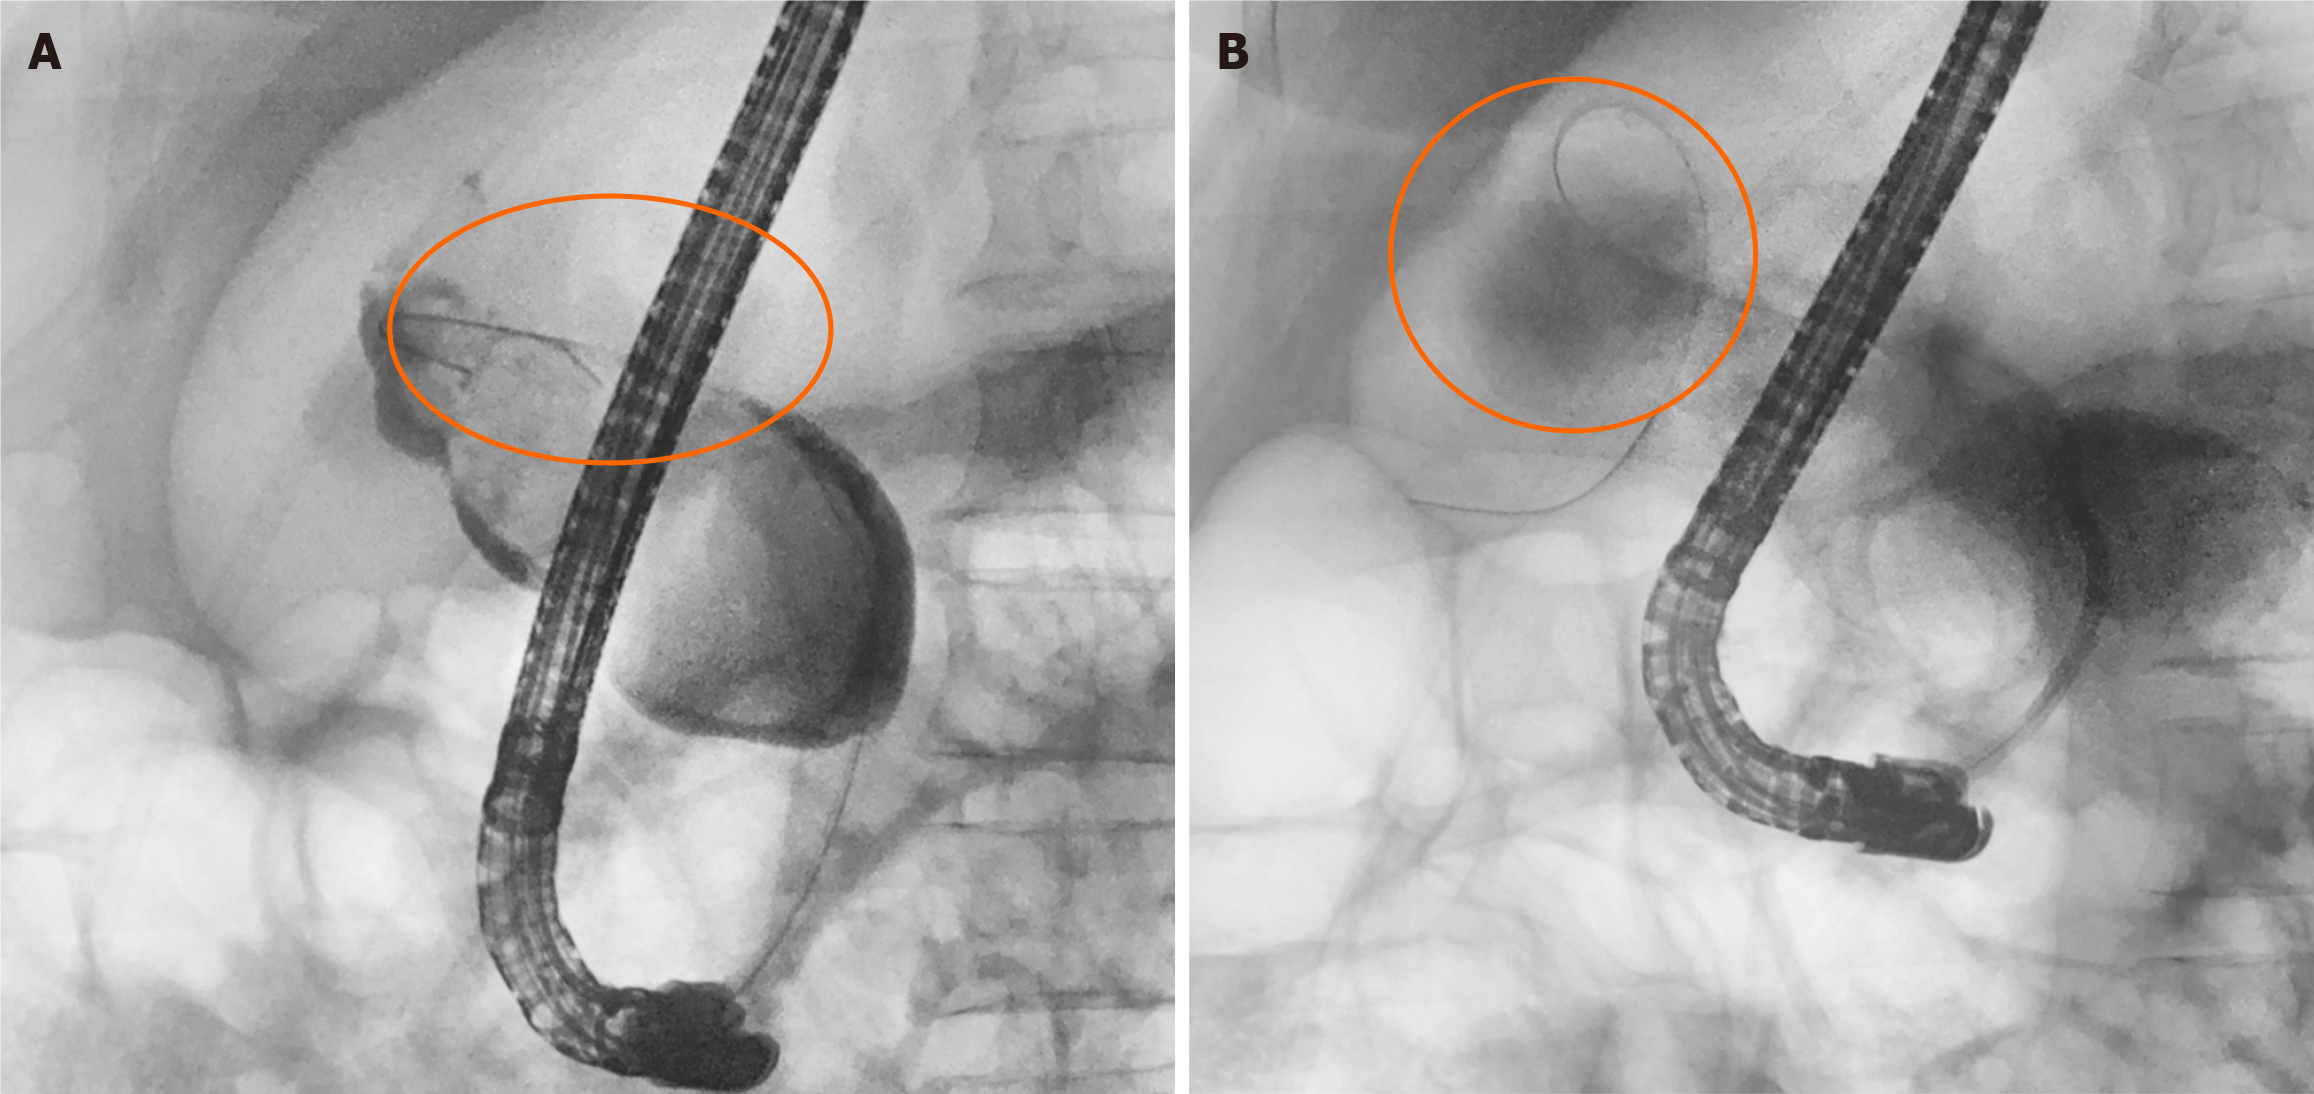
Figure 2 Direct visualization of biliary tract via endoscopic retrograde cholangiopancreatography with fluoroscopy.
A: Fluoroscopic image showing a large filling defect in the lower and middle third of the main bile duct (orange circle); B: Fluoroscopic image showing contrast extravasation and the guide wire escaping the normal confines of the biliary architecture, concerning for bile duct perforation (orange circle).
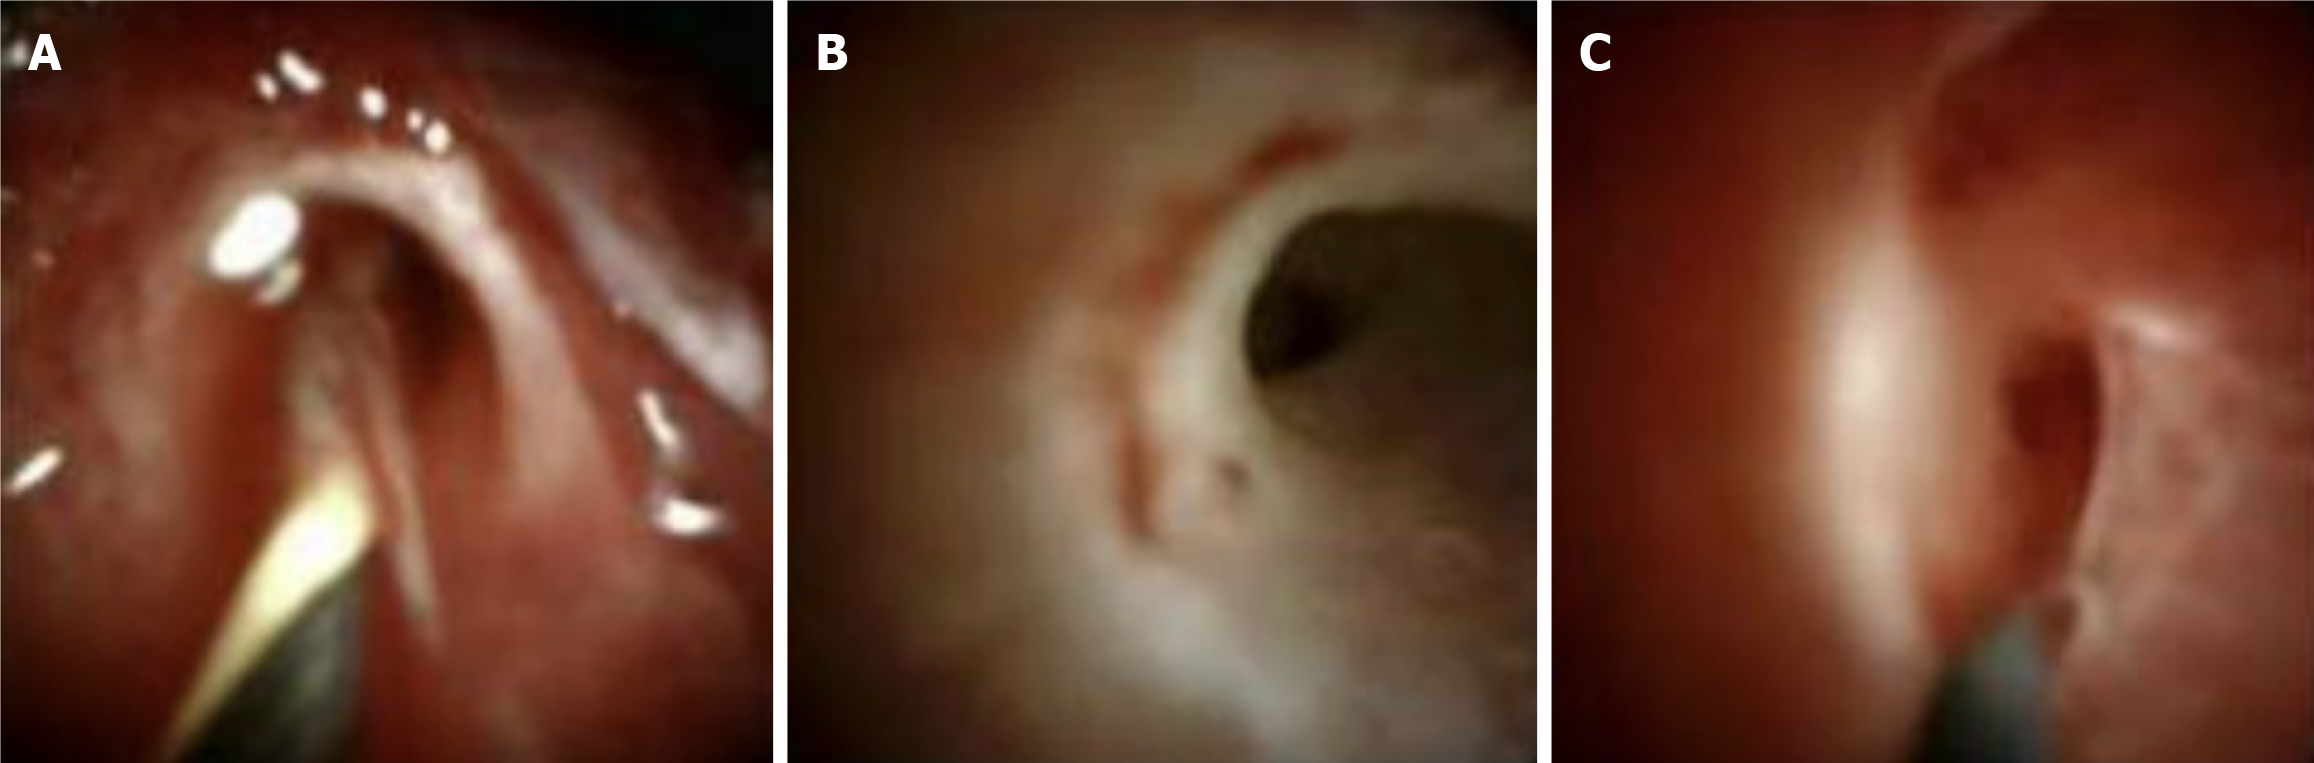
Figure 3 Direct visualization of biliary tract via endoscopic retrograde cholangiopancreatography with cholangioscopy.
A: Cholangioscopic image showing partial suction of a large blood clot in the middle third of the common bile duct (CBD). The proximal bile duct could not be visualized beyond this point due to the large clot; B: Cholangioscopic image showing mucosal erythema in the CBD; C: Cholangioscopic image showing an intraductal guide wire in the distal CBD with active bleeding, concerning for hemobilia.
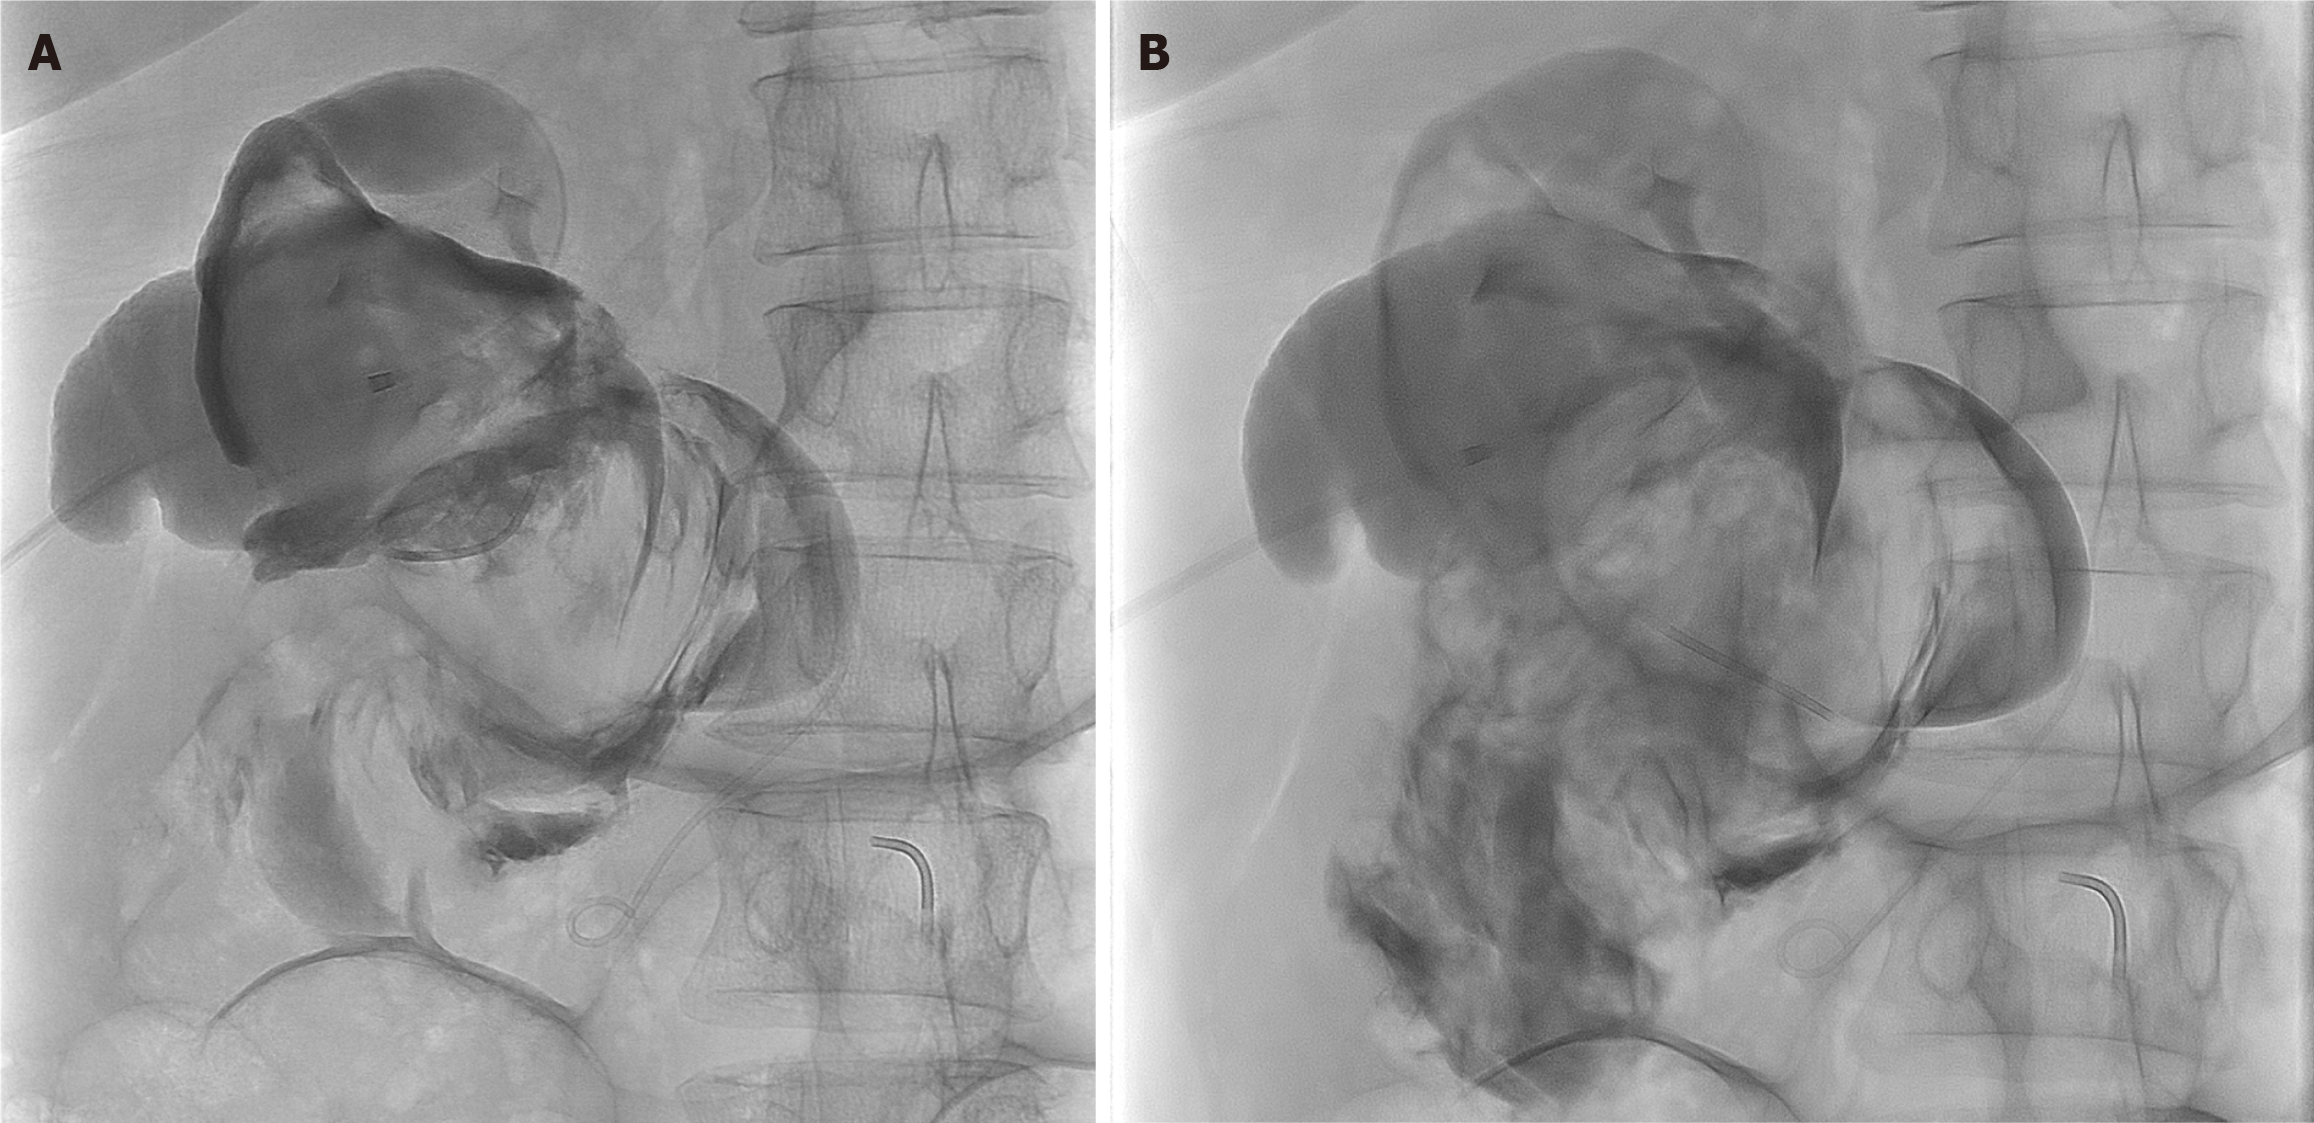
Figure 4 Cholecystostomy cholangiogram showing common bile duct extravasation.
Fluoroscopic images obtained via injection of contrast through percutaneously placed cholecystostomy tube. A: Early-phase image showing opacification of the gallbladder and proximal biliary tree, confirming the appropriate position of the tube; B: Progressive-phase image obtained with continued contrast injection, demonstrating extravasation of the contrast into an irregular, poorly marginated collection consistent with perforation of the bile duct and active bile leak.

Figure 5 Timeline of overall diagnosis and treatment course.
CT: Computed tomography; ERCP: Endoscopic retrograde cholangiopancreatography; CBD: Common bile duct.
- Citation: Bautista LYA, Lee M, Devgan K, Longo J, Singh S, Bakdash K, Ahmed M, Agrawal R. Preoperative cholangioscopic identification of traumatic type IVa choledochal cyst perforation after motor vehicle collision: A case report. World J Clin Cases 2026; 14(26): 126222
- URL: https://www.wjgnet.com/2307-8960/full/v14/i26/126222.htm
- DOI: https://dx.doi.org/10.12998/wjcc.126222