
















Copyright: ©Author(s) 2026.
World J Clin Oncol. Sep 24, 2026; 17(9): 125491
Published online Sep 24, 2026. doi: 10.5306/wjco.125491
Published online Sep 24, 2026. doi: 10.5306/wjco.125491
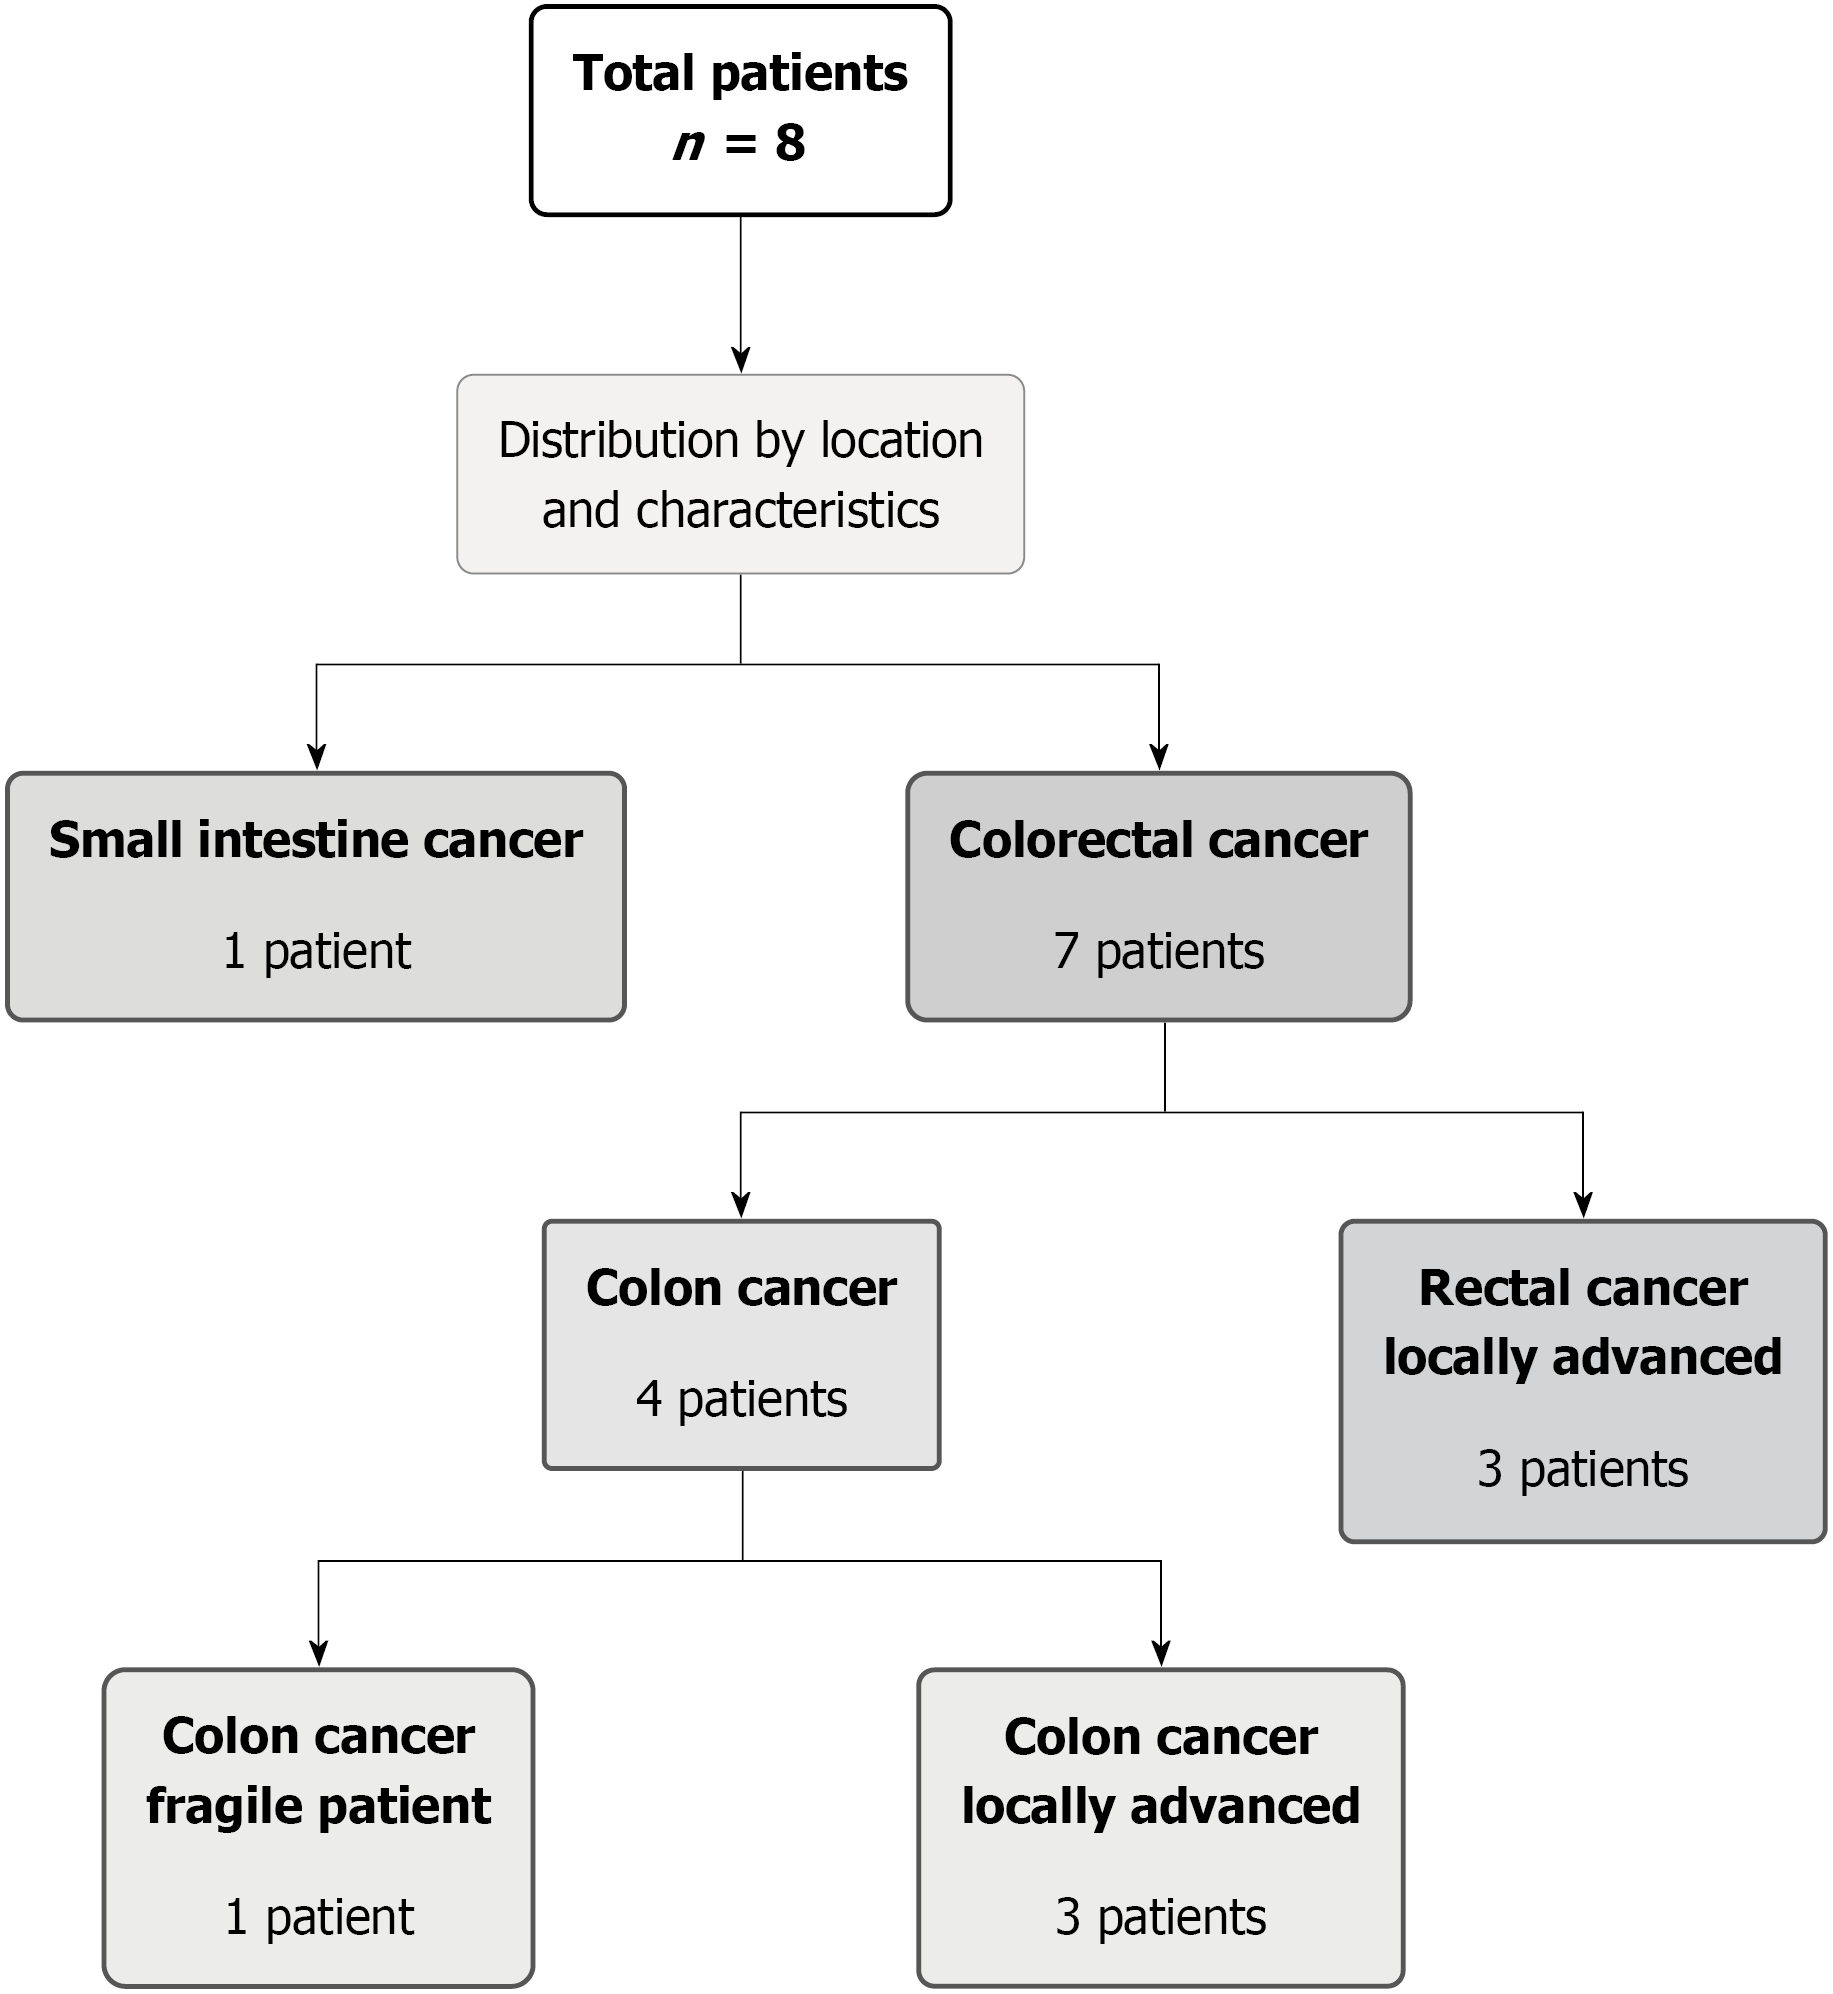
Figure 1
Patient flowchart.
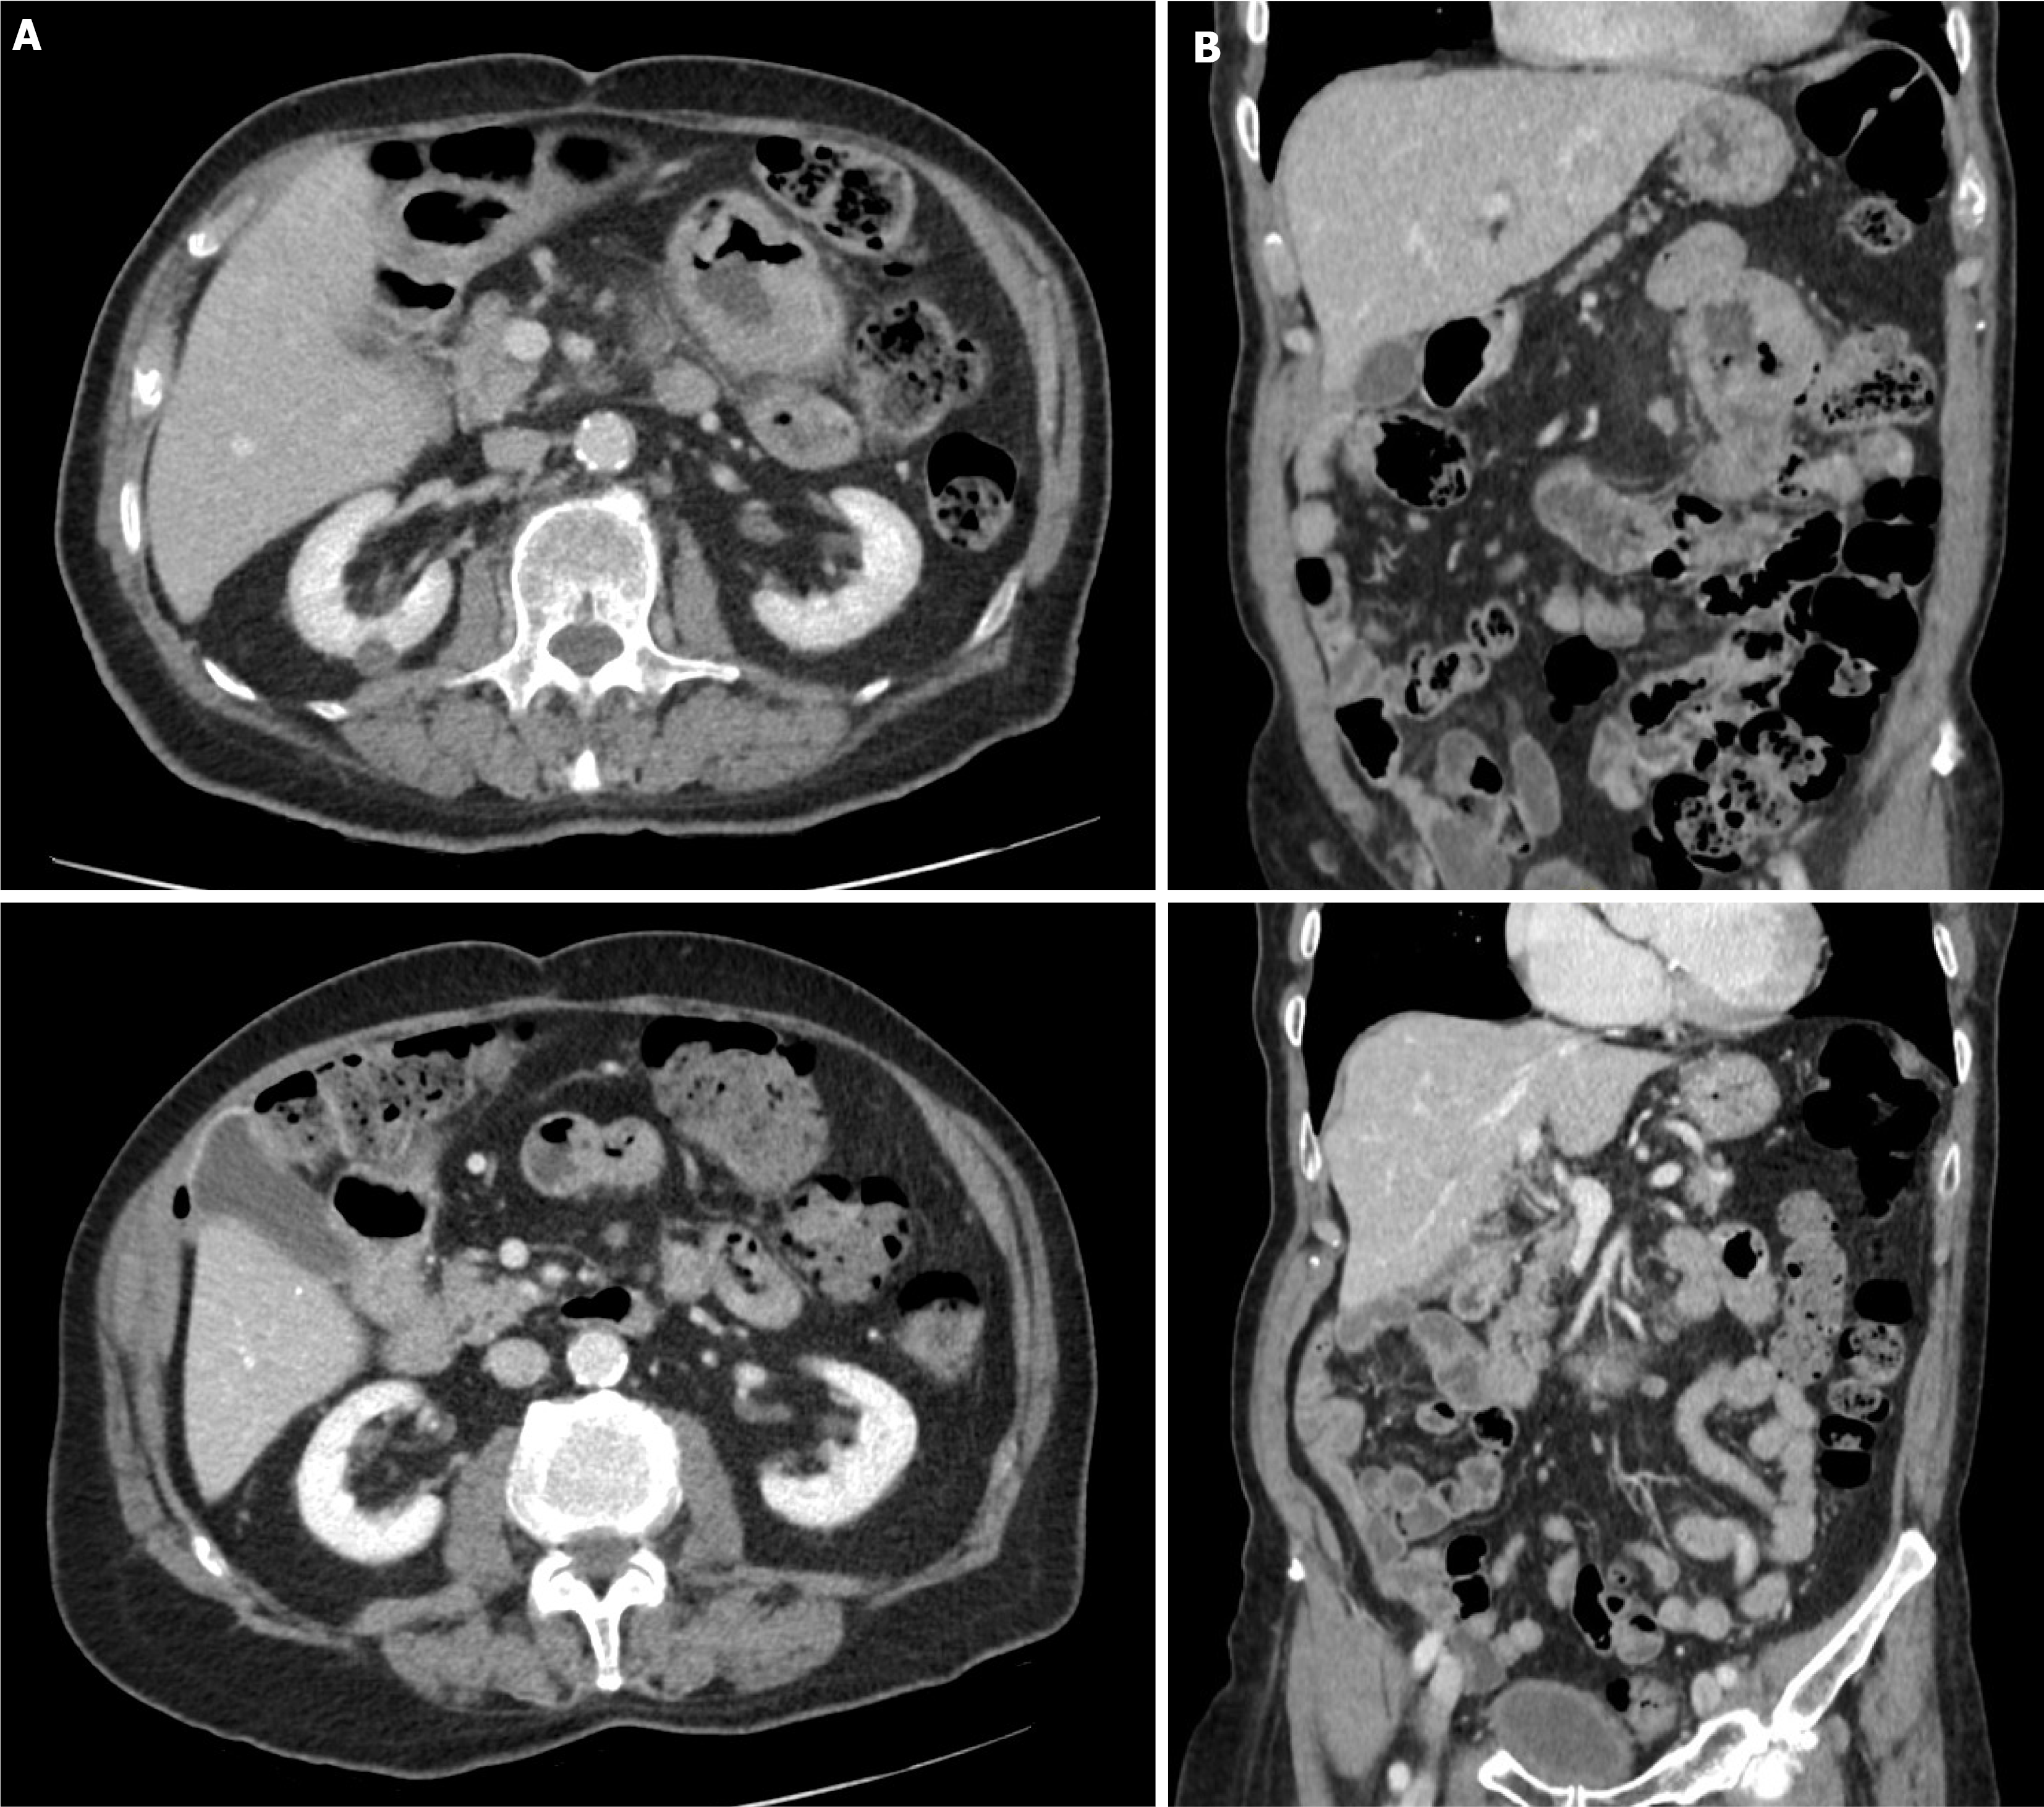
Figure 2 Case 1.
A: Axial and sagittal abdominal computed tomography (CT) images obtained at diagnosis; B: Axial and sagittal abdominal CT images obtained after completion of immune checkpoint inhibitor therapy.
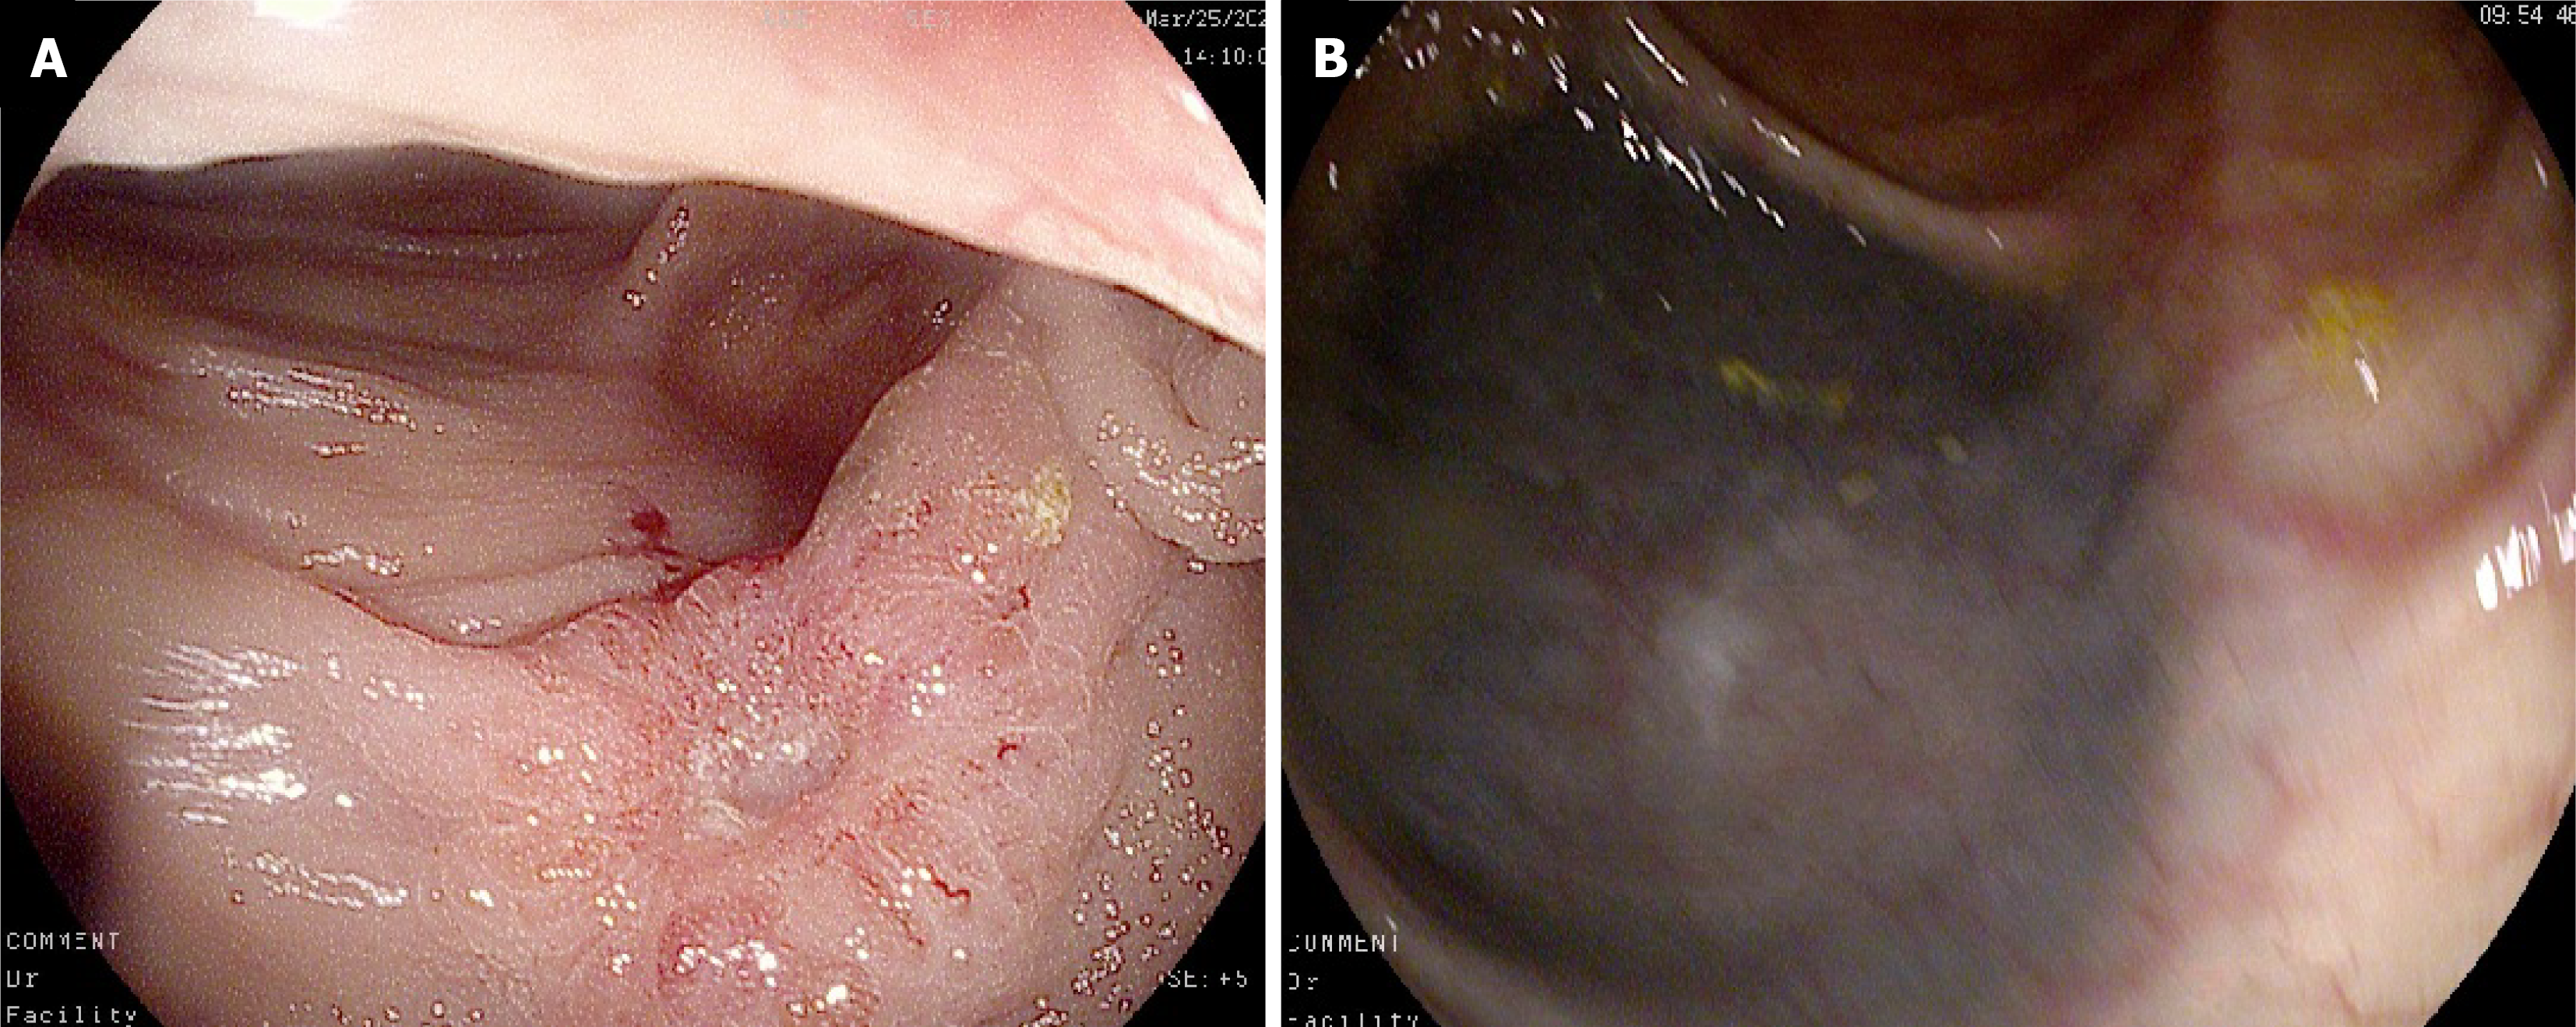
Figure 3 Case 2.
A: Colonoscopy at diagnosis; B: Colonoscopy after completion of immune checkpoint inhibitor therapy, showing the site of prior tattoo marking.
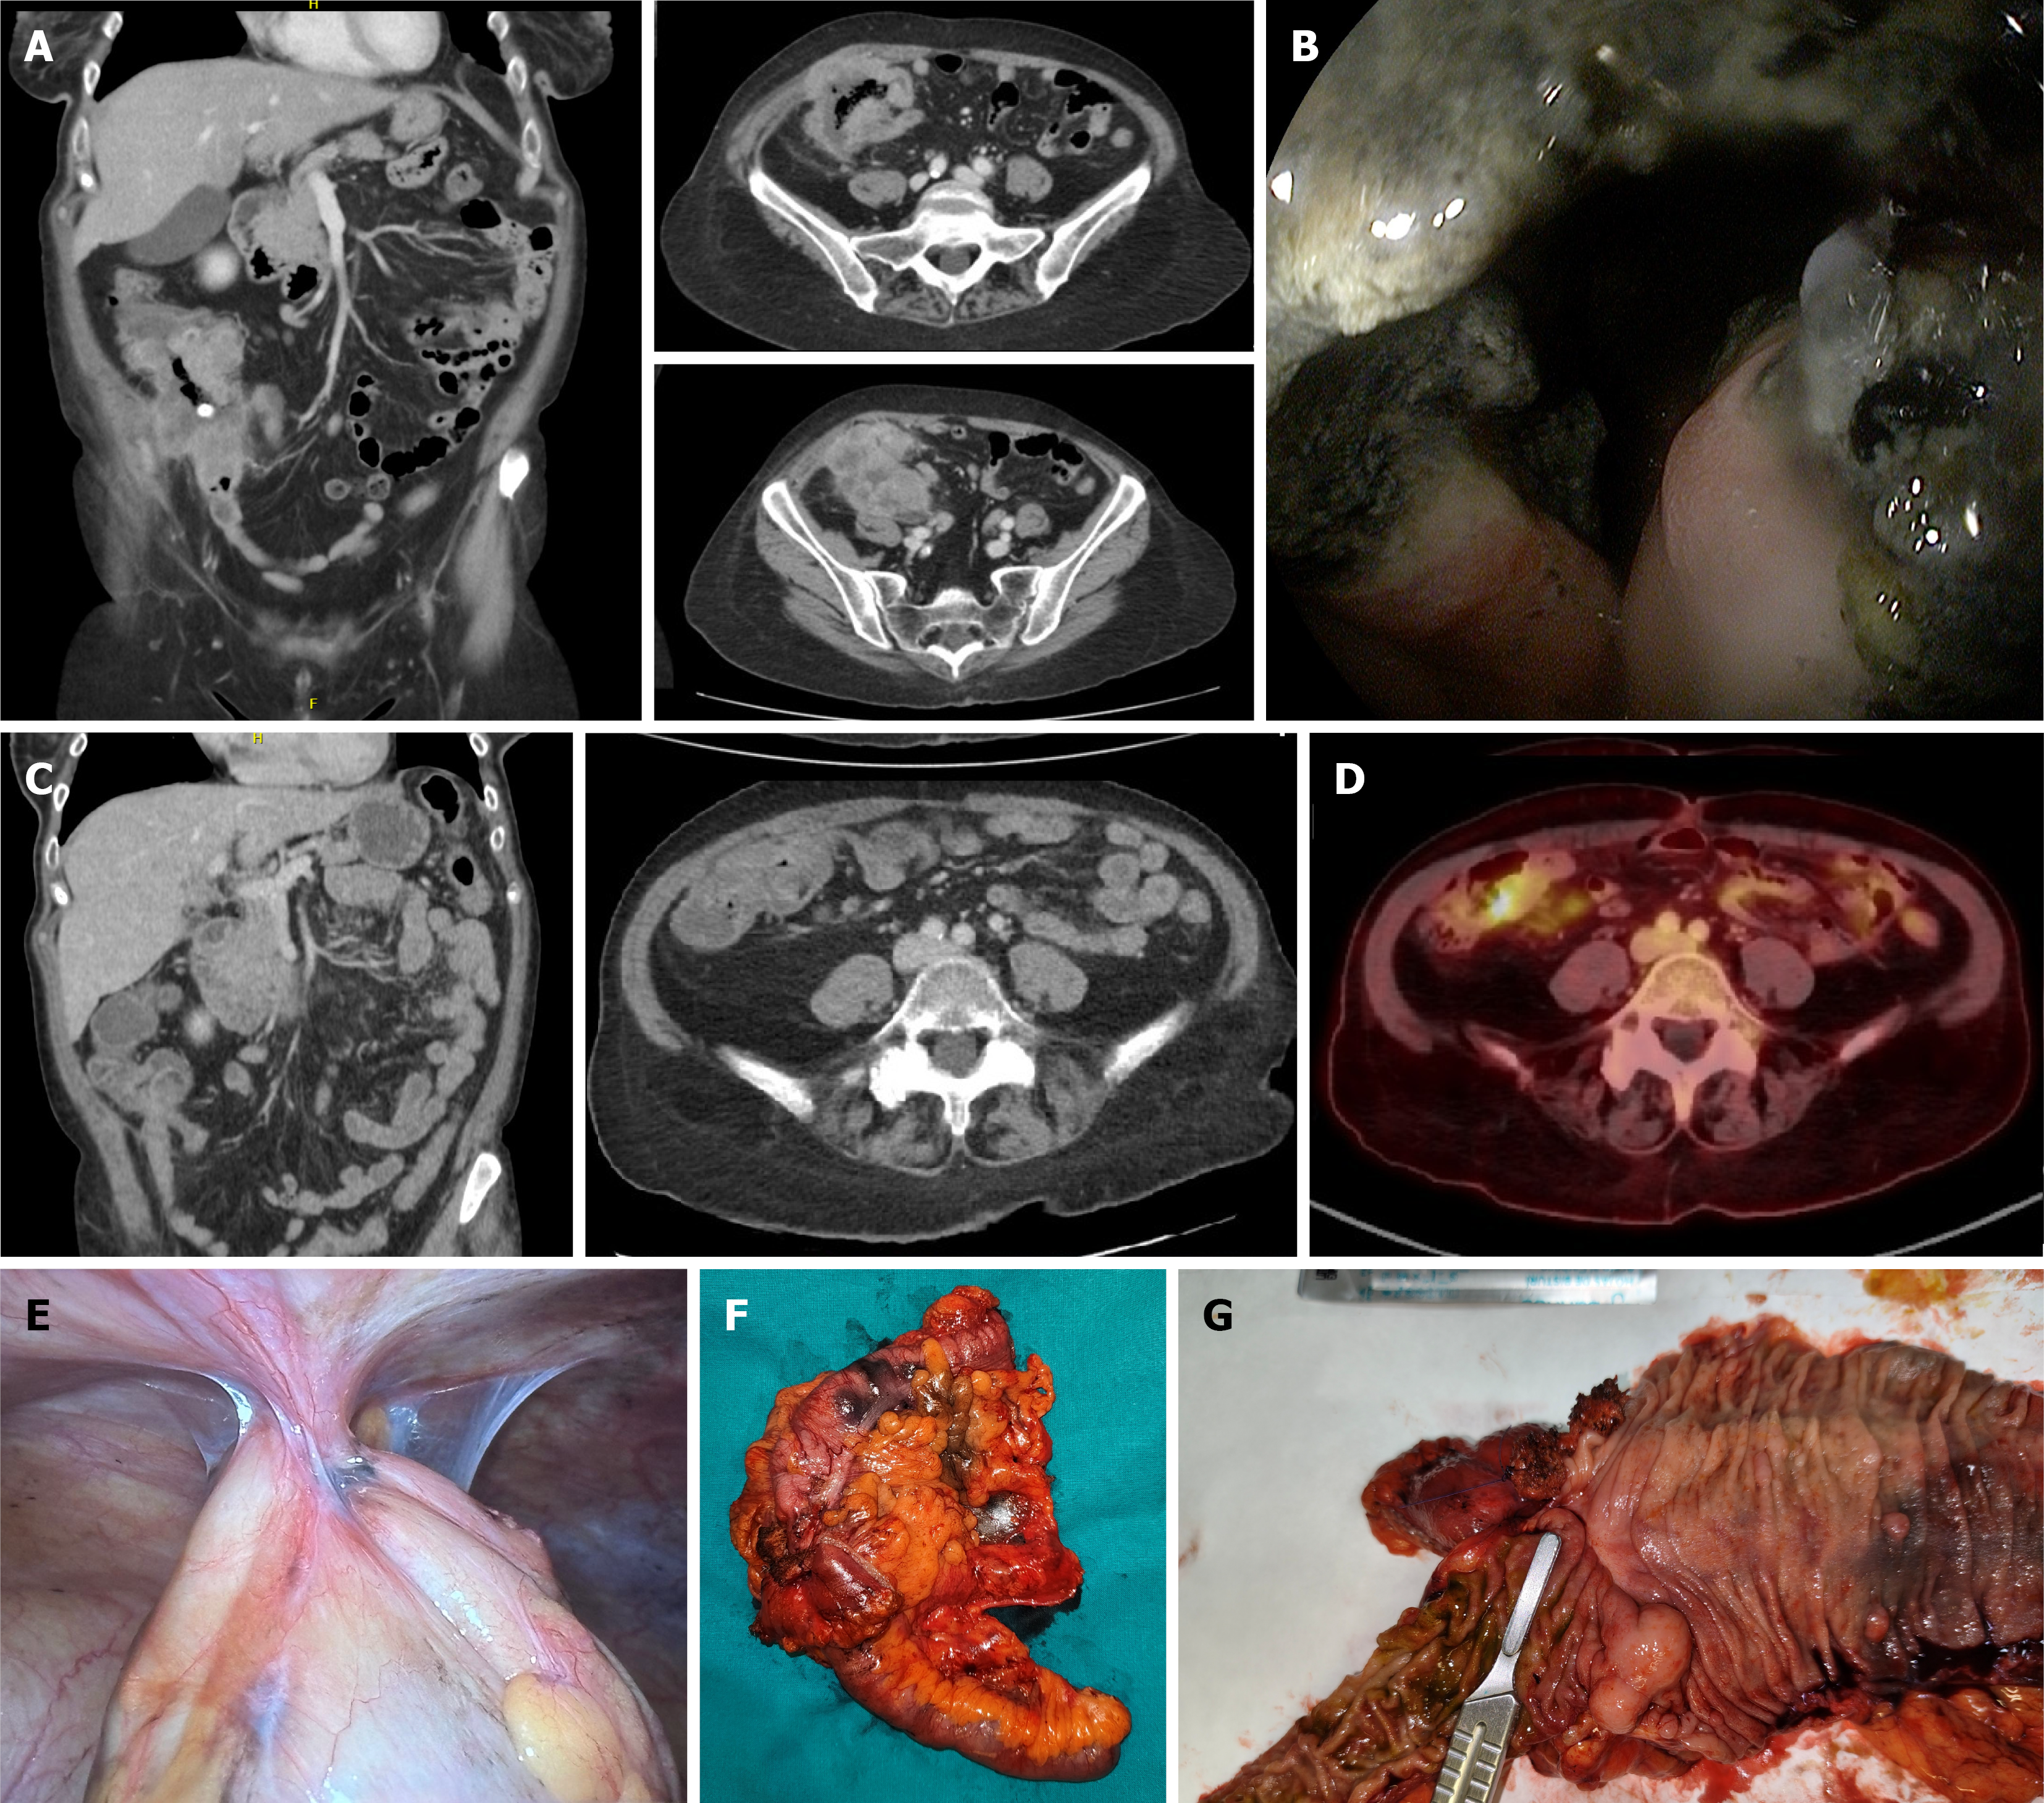
Figure 4 Case 3.
A: Coronal and axial abdominal computed tomography (CT) images at diagnosis; B: Colonoscopy at diagnosis; C: Coronal and axial abdominal CT images after completion of neoadjuvant therapy; D: PET/TAC prior to surgery; E: Intraoperative findings; F: Right hemicolectomy specimen; G: Macroscopic examination of the surgical specimen showing residual lesion.
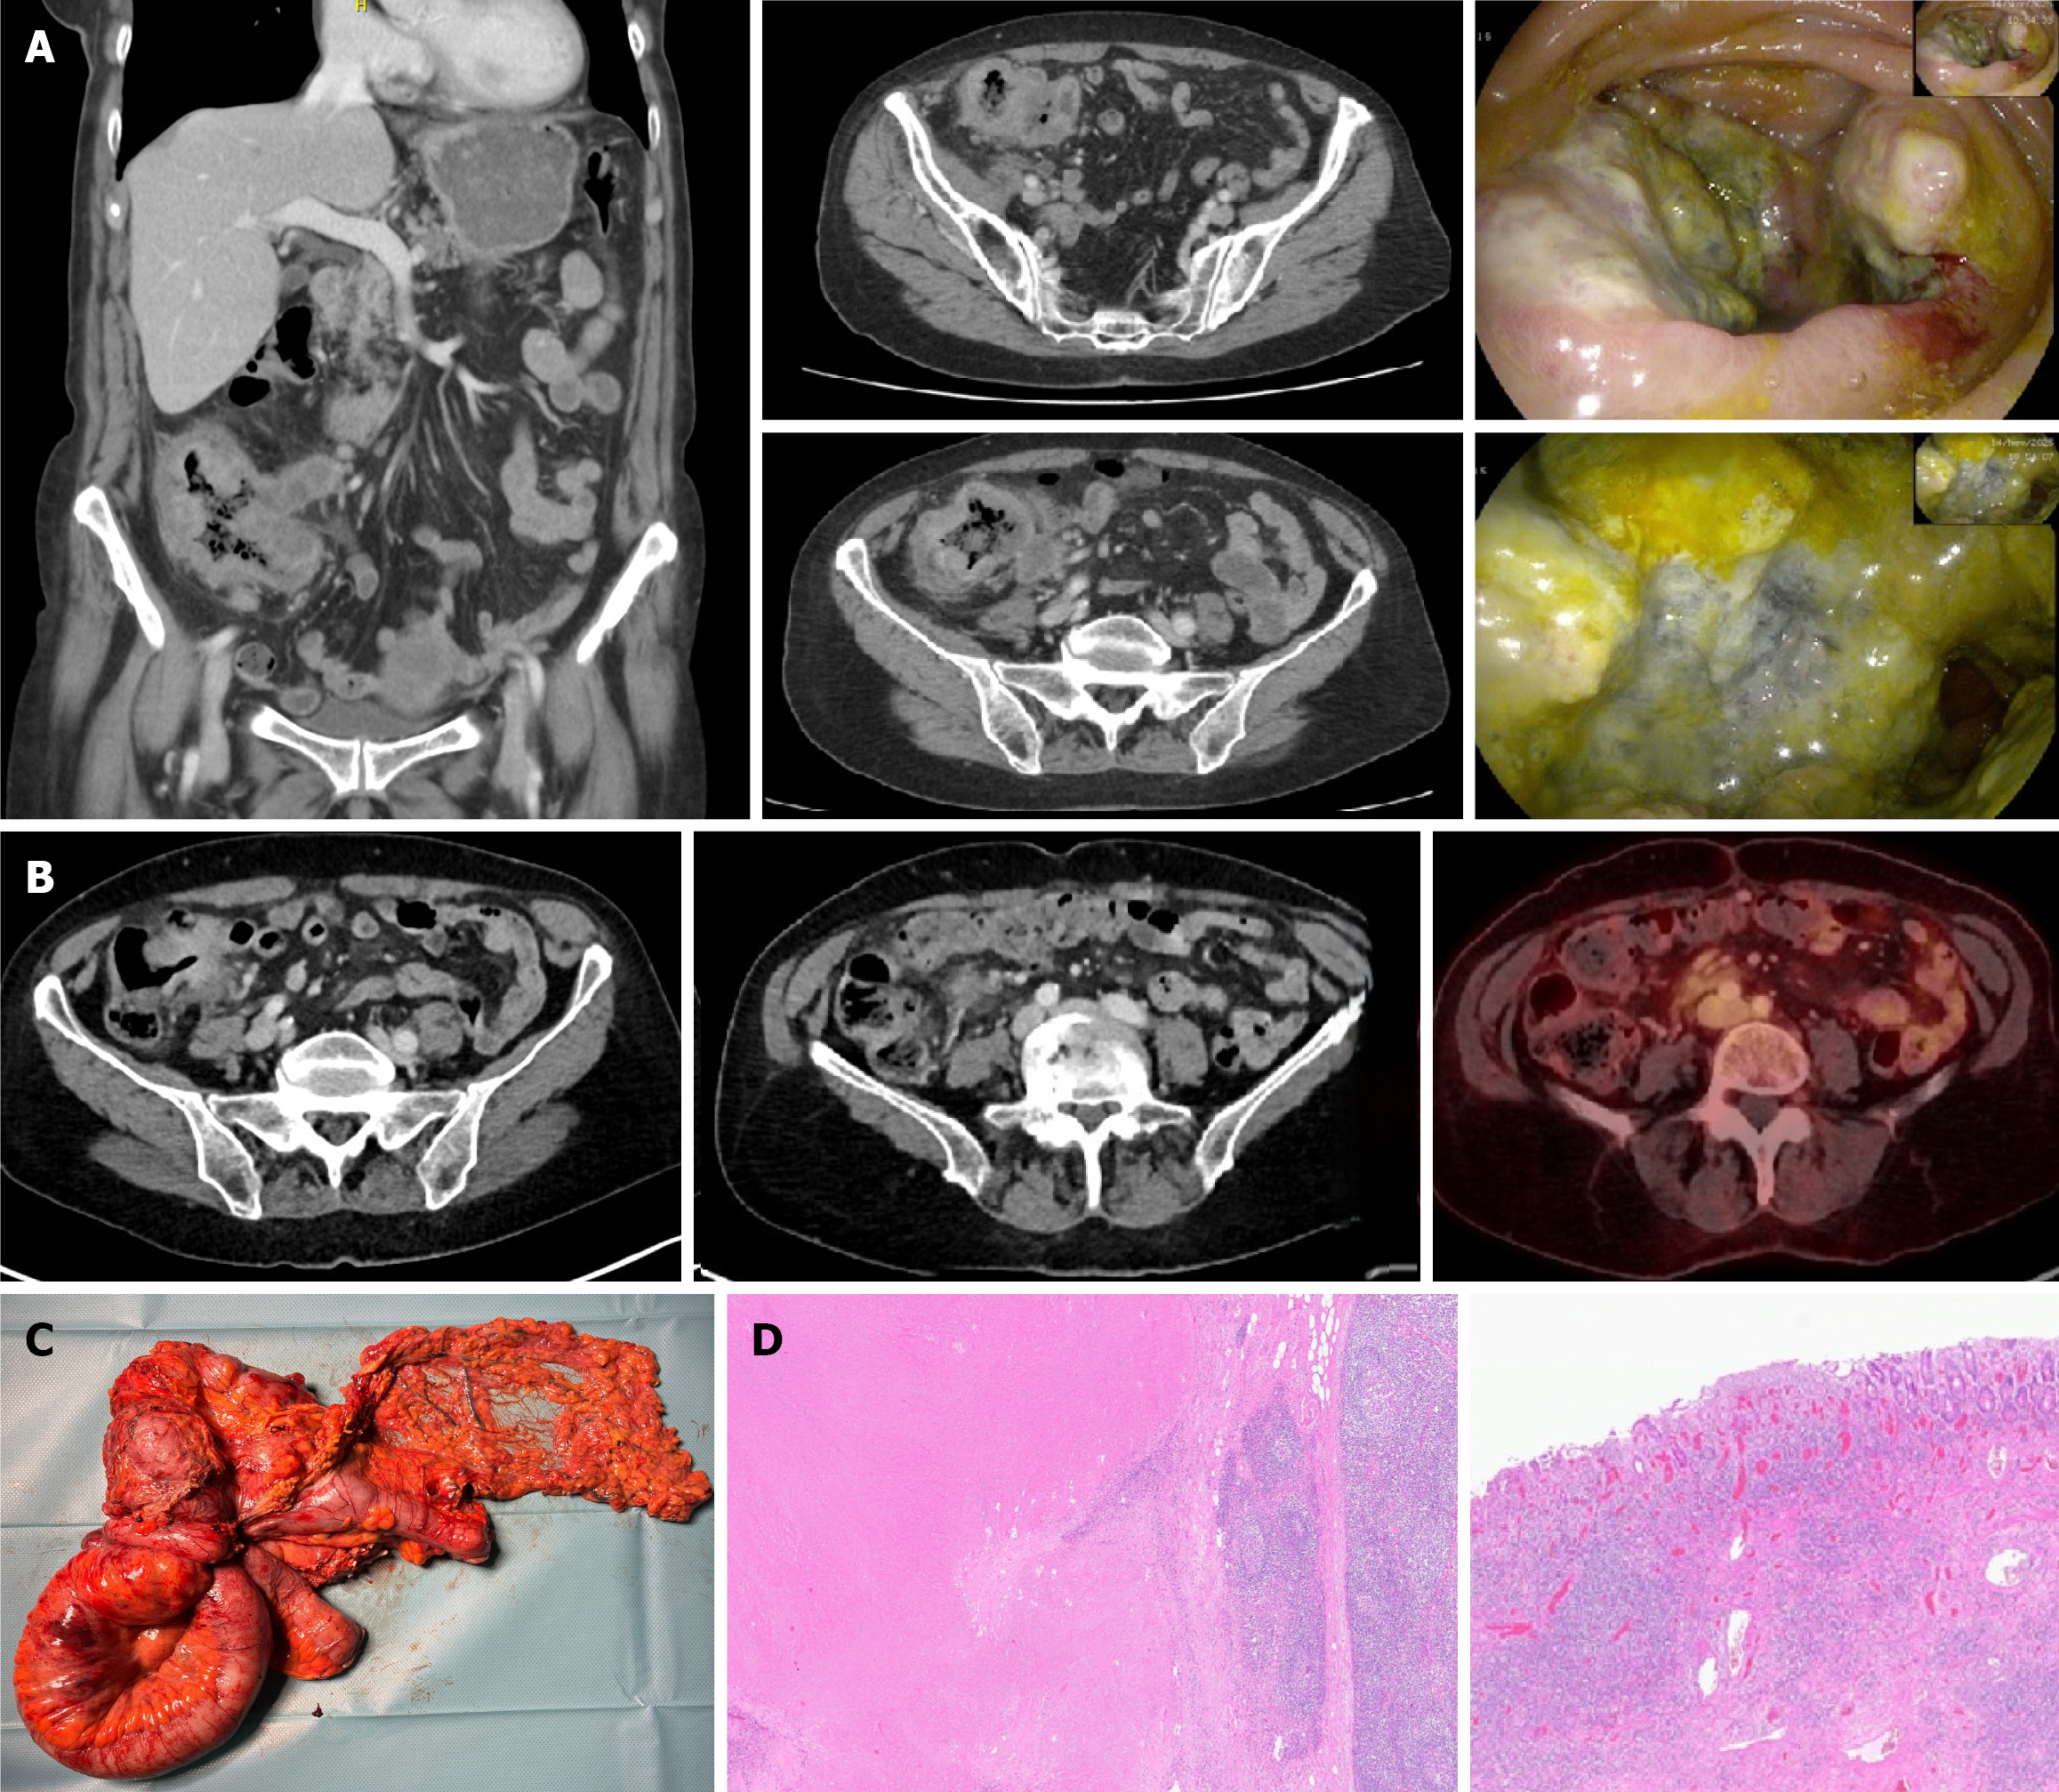
Figure 5 Case 4.
A: Coronal and axial abdominal computed tomography (CT) images and colonoscopy at diagnosis; B: Post-treatment abdominal CT and positron emission tomography/computed tomography after completion of neoadjuvant therapy; C: Right hemicolectomy specimen; D: Microscopy showing an ulcerated cecal tumour bed with fibroinflammatory changes and granulation tissue, without residual viable tumour cells, consistent with a complete pathological response. Reactive lymph node changes and extensive tumour necrosis related to treatment are also observed.
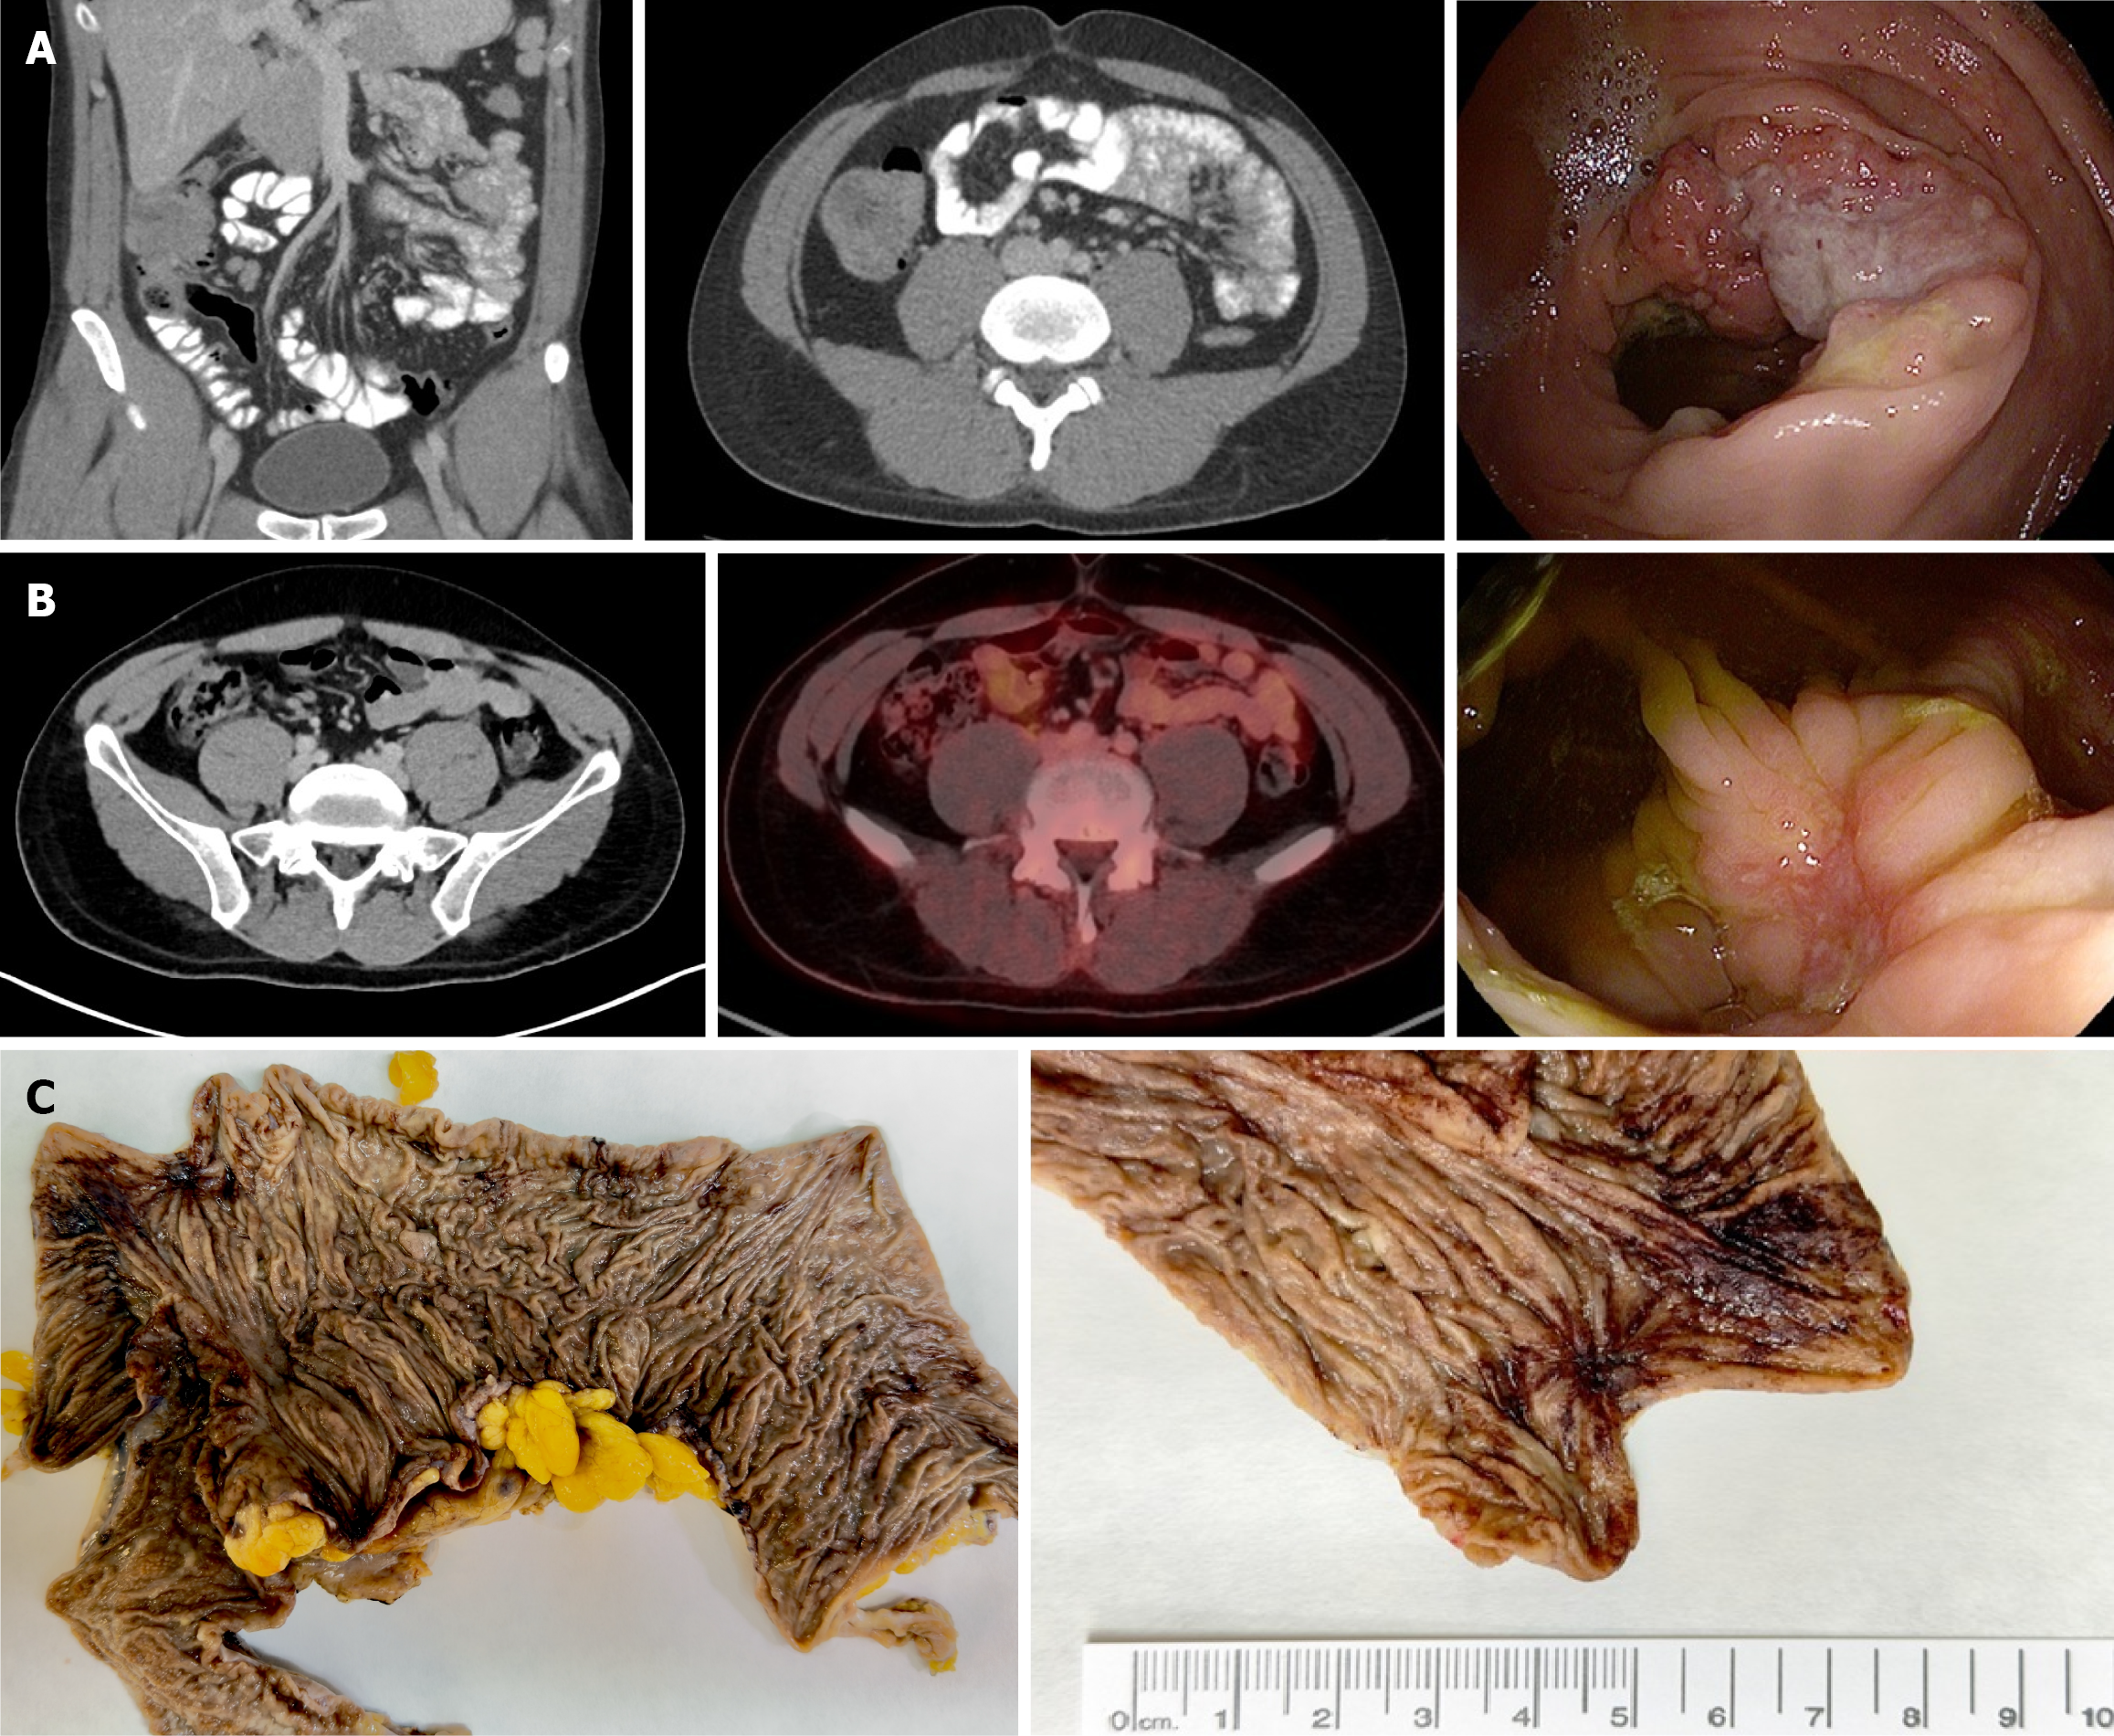
Figure 6 Case 5.
A: Coronal and axial abdominal computed tomography (CT) images and colonoscopy at diagnosis; B: Post-treatment abdominal CT, positron emission tomography/computed tomography, and colonoscopy after completion of neoadjuvant therapy; C: Gross pathology of the opened right hemicolectomy specimen showing an excavated lesion at the ileocecal junction extending into the ascending colon, corresponding to the treated tumor bed; detailed view of a 2 cm × 1.5 cm residual lesion at the post-treatment site.
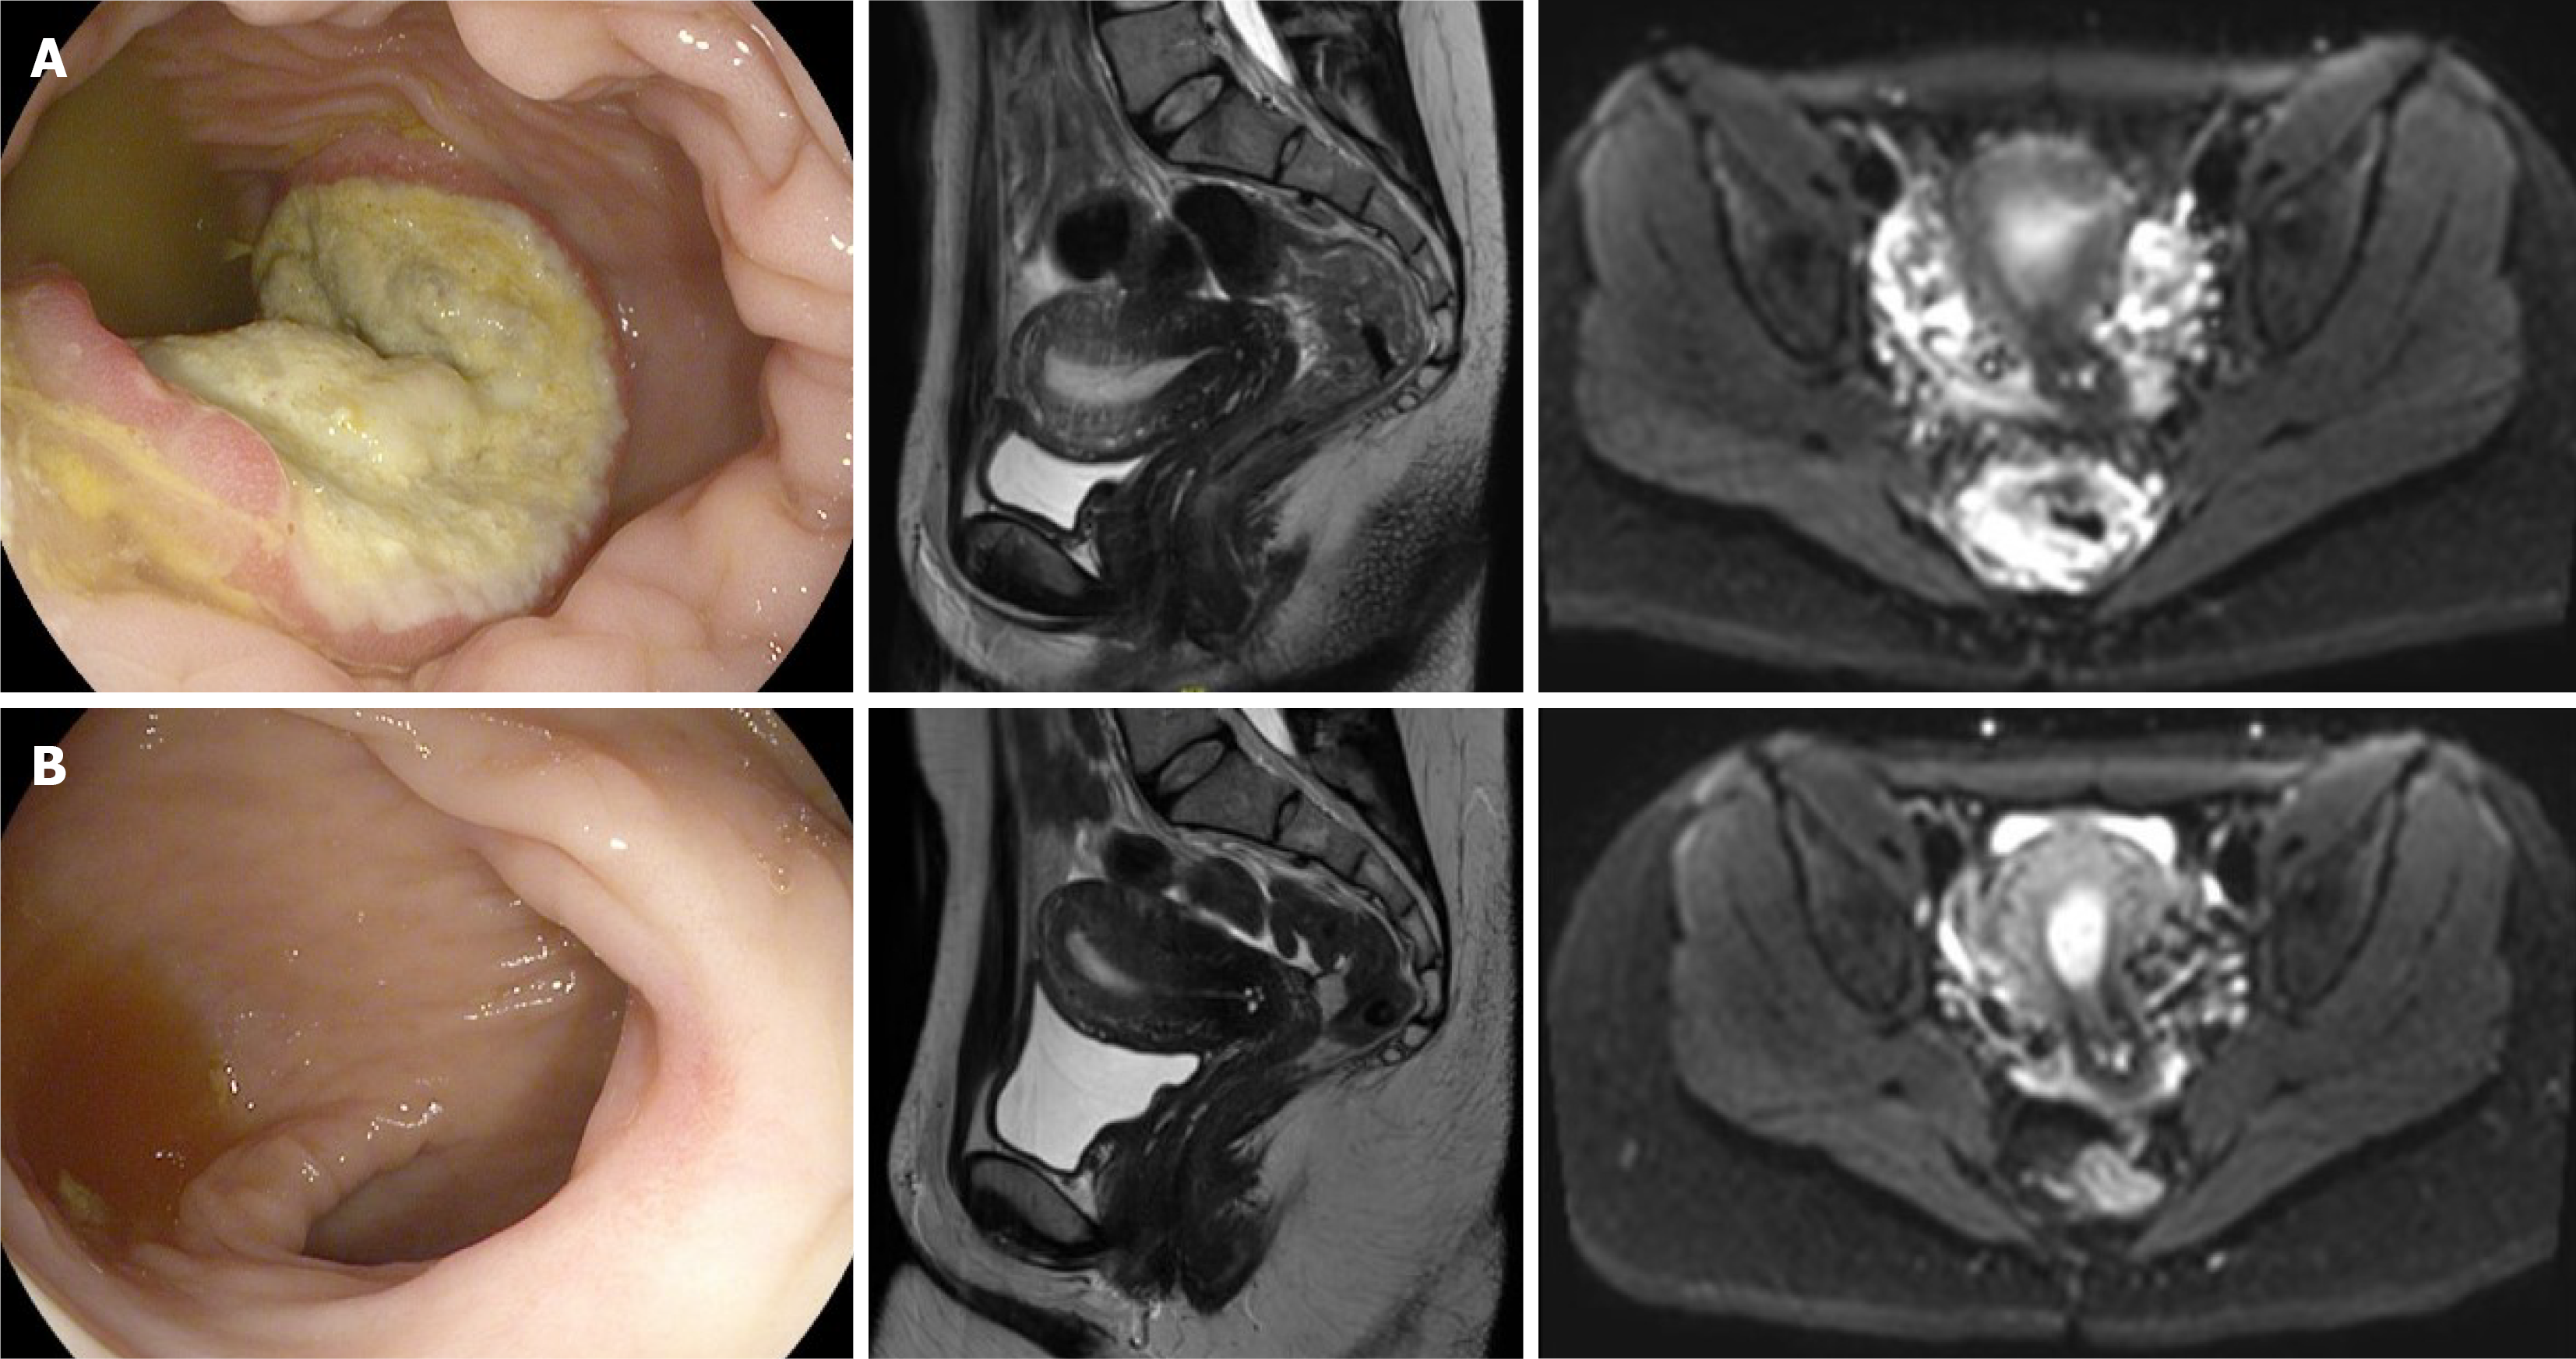
Figure 7 Case 6.
A: Colonoscopy, sagittal magnetic resonance imaging (MRI), and axial diffusion-weighted MRI at diagnosis; B: Rectoscopy and MRI at 6 months post-treatment, demonstrating a complete clinical response.
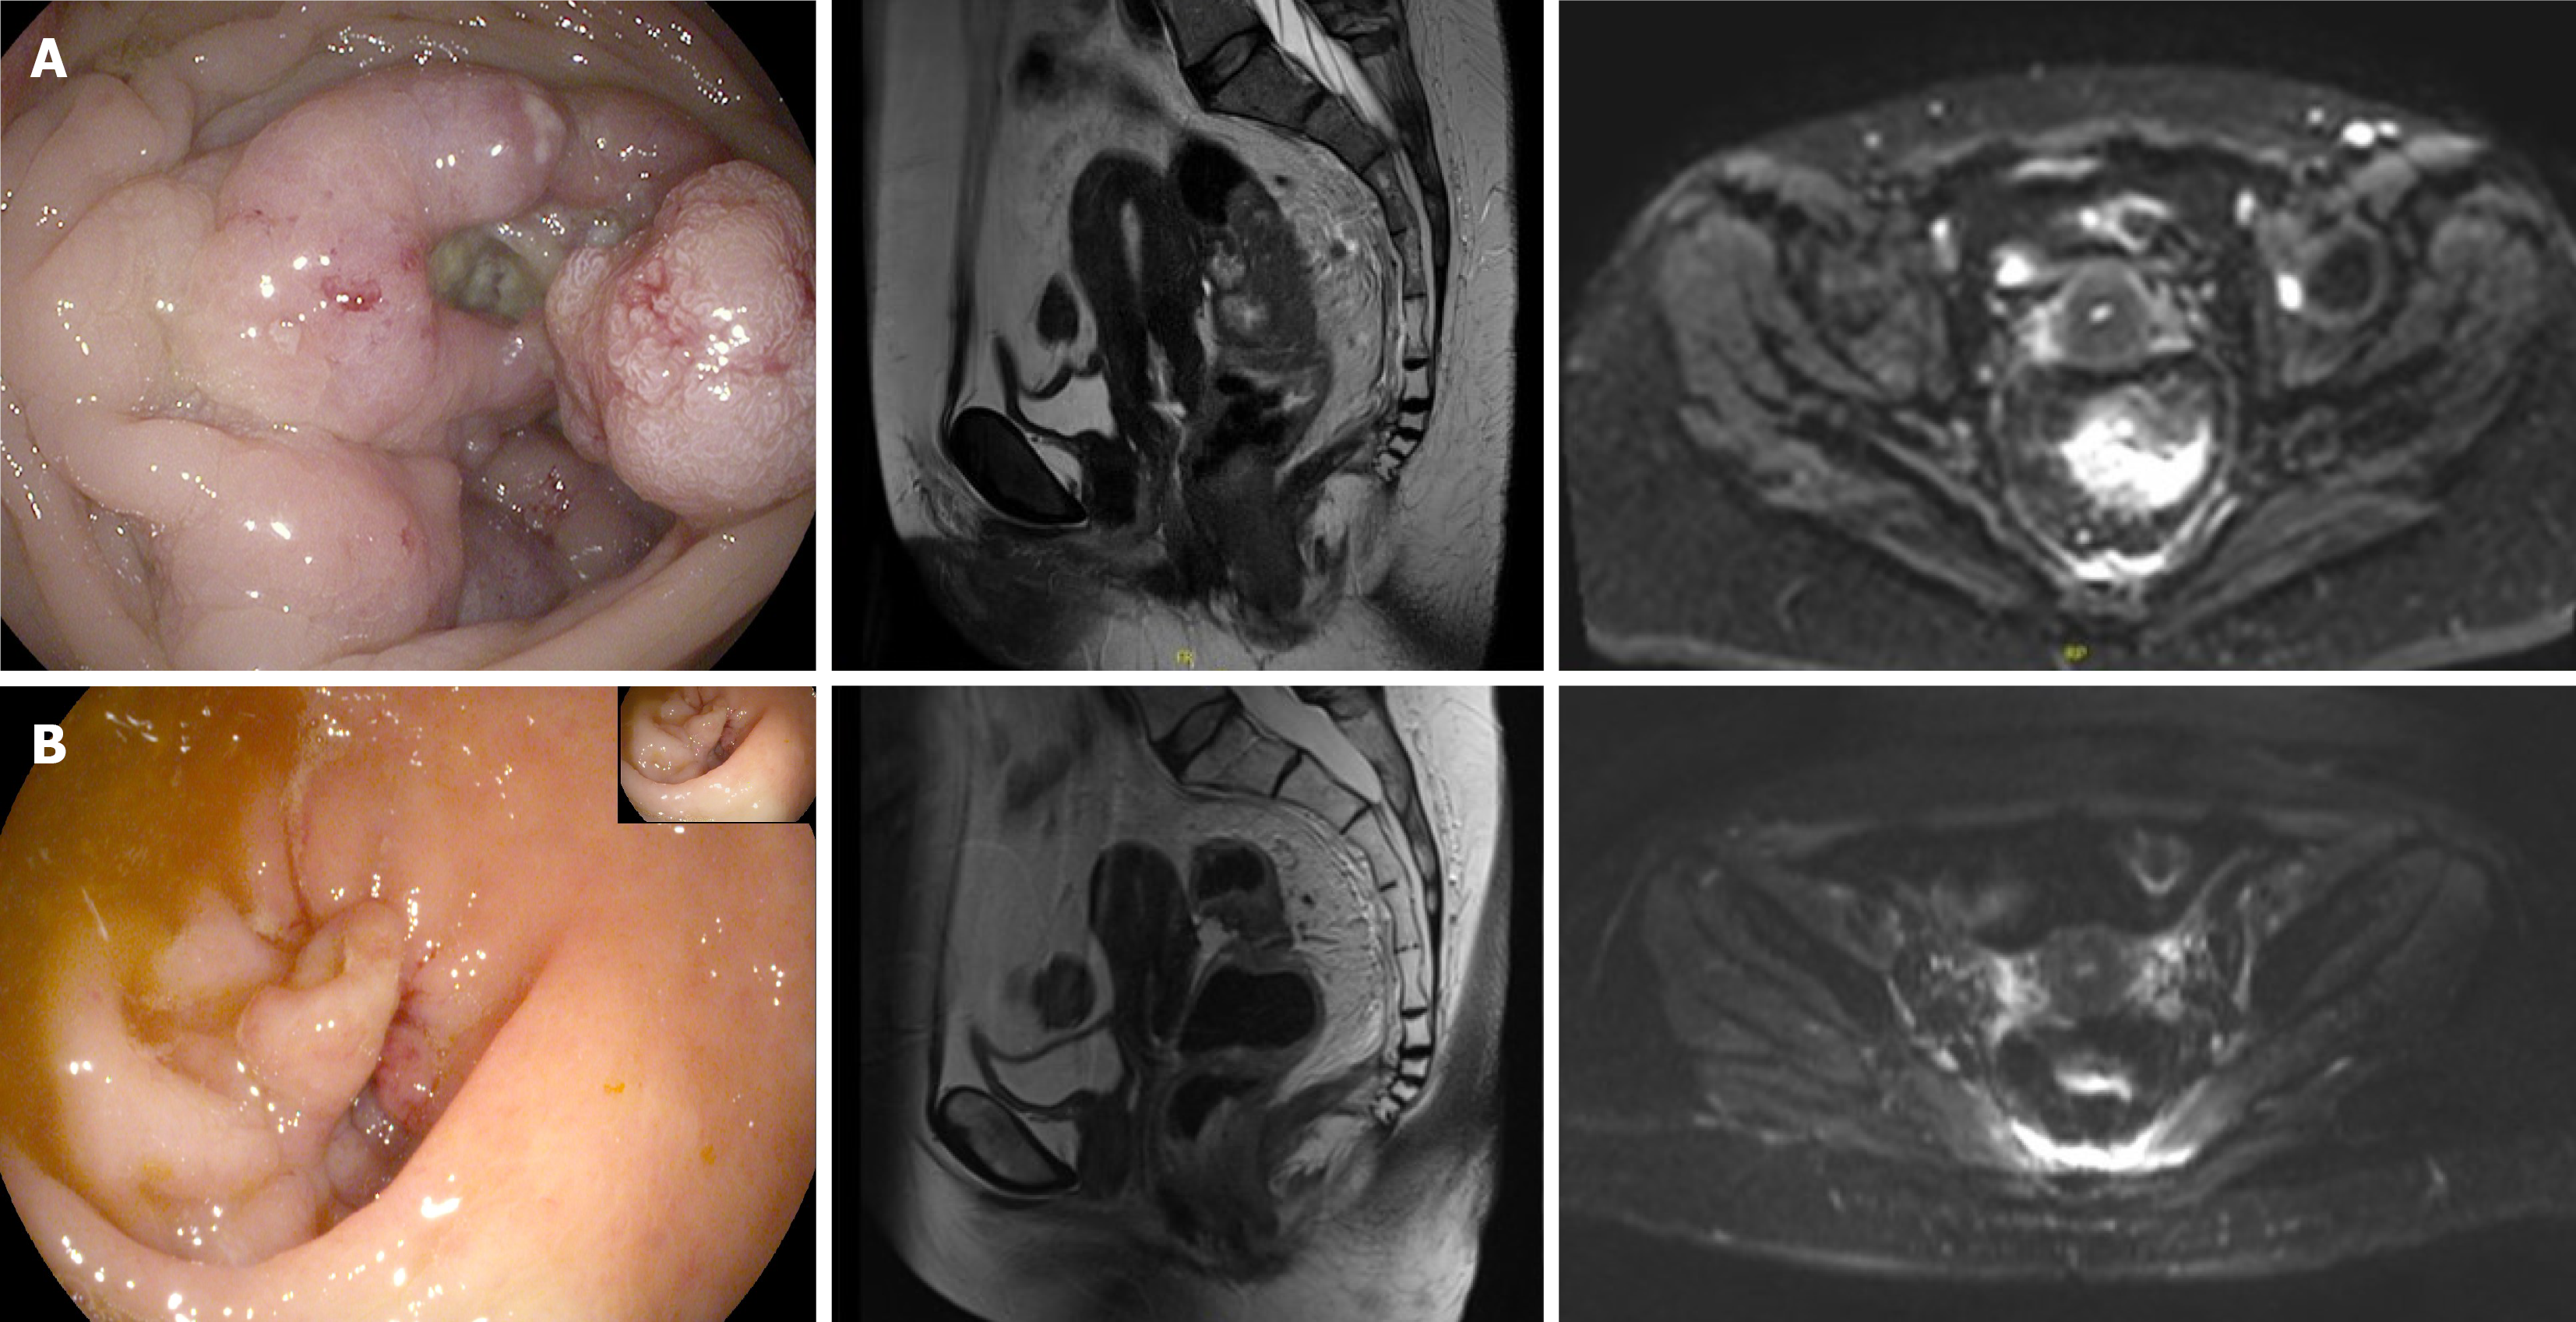
Figure 8 Case 7.
A: Colonoscopy, sagittal magnetic resonance imaging (MRI), and diffusion-weighted MRI at diagnosis; B: Rectoscopy showing residual stenosis, and post-treatment MRI demonstrating tumour response.
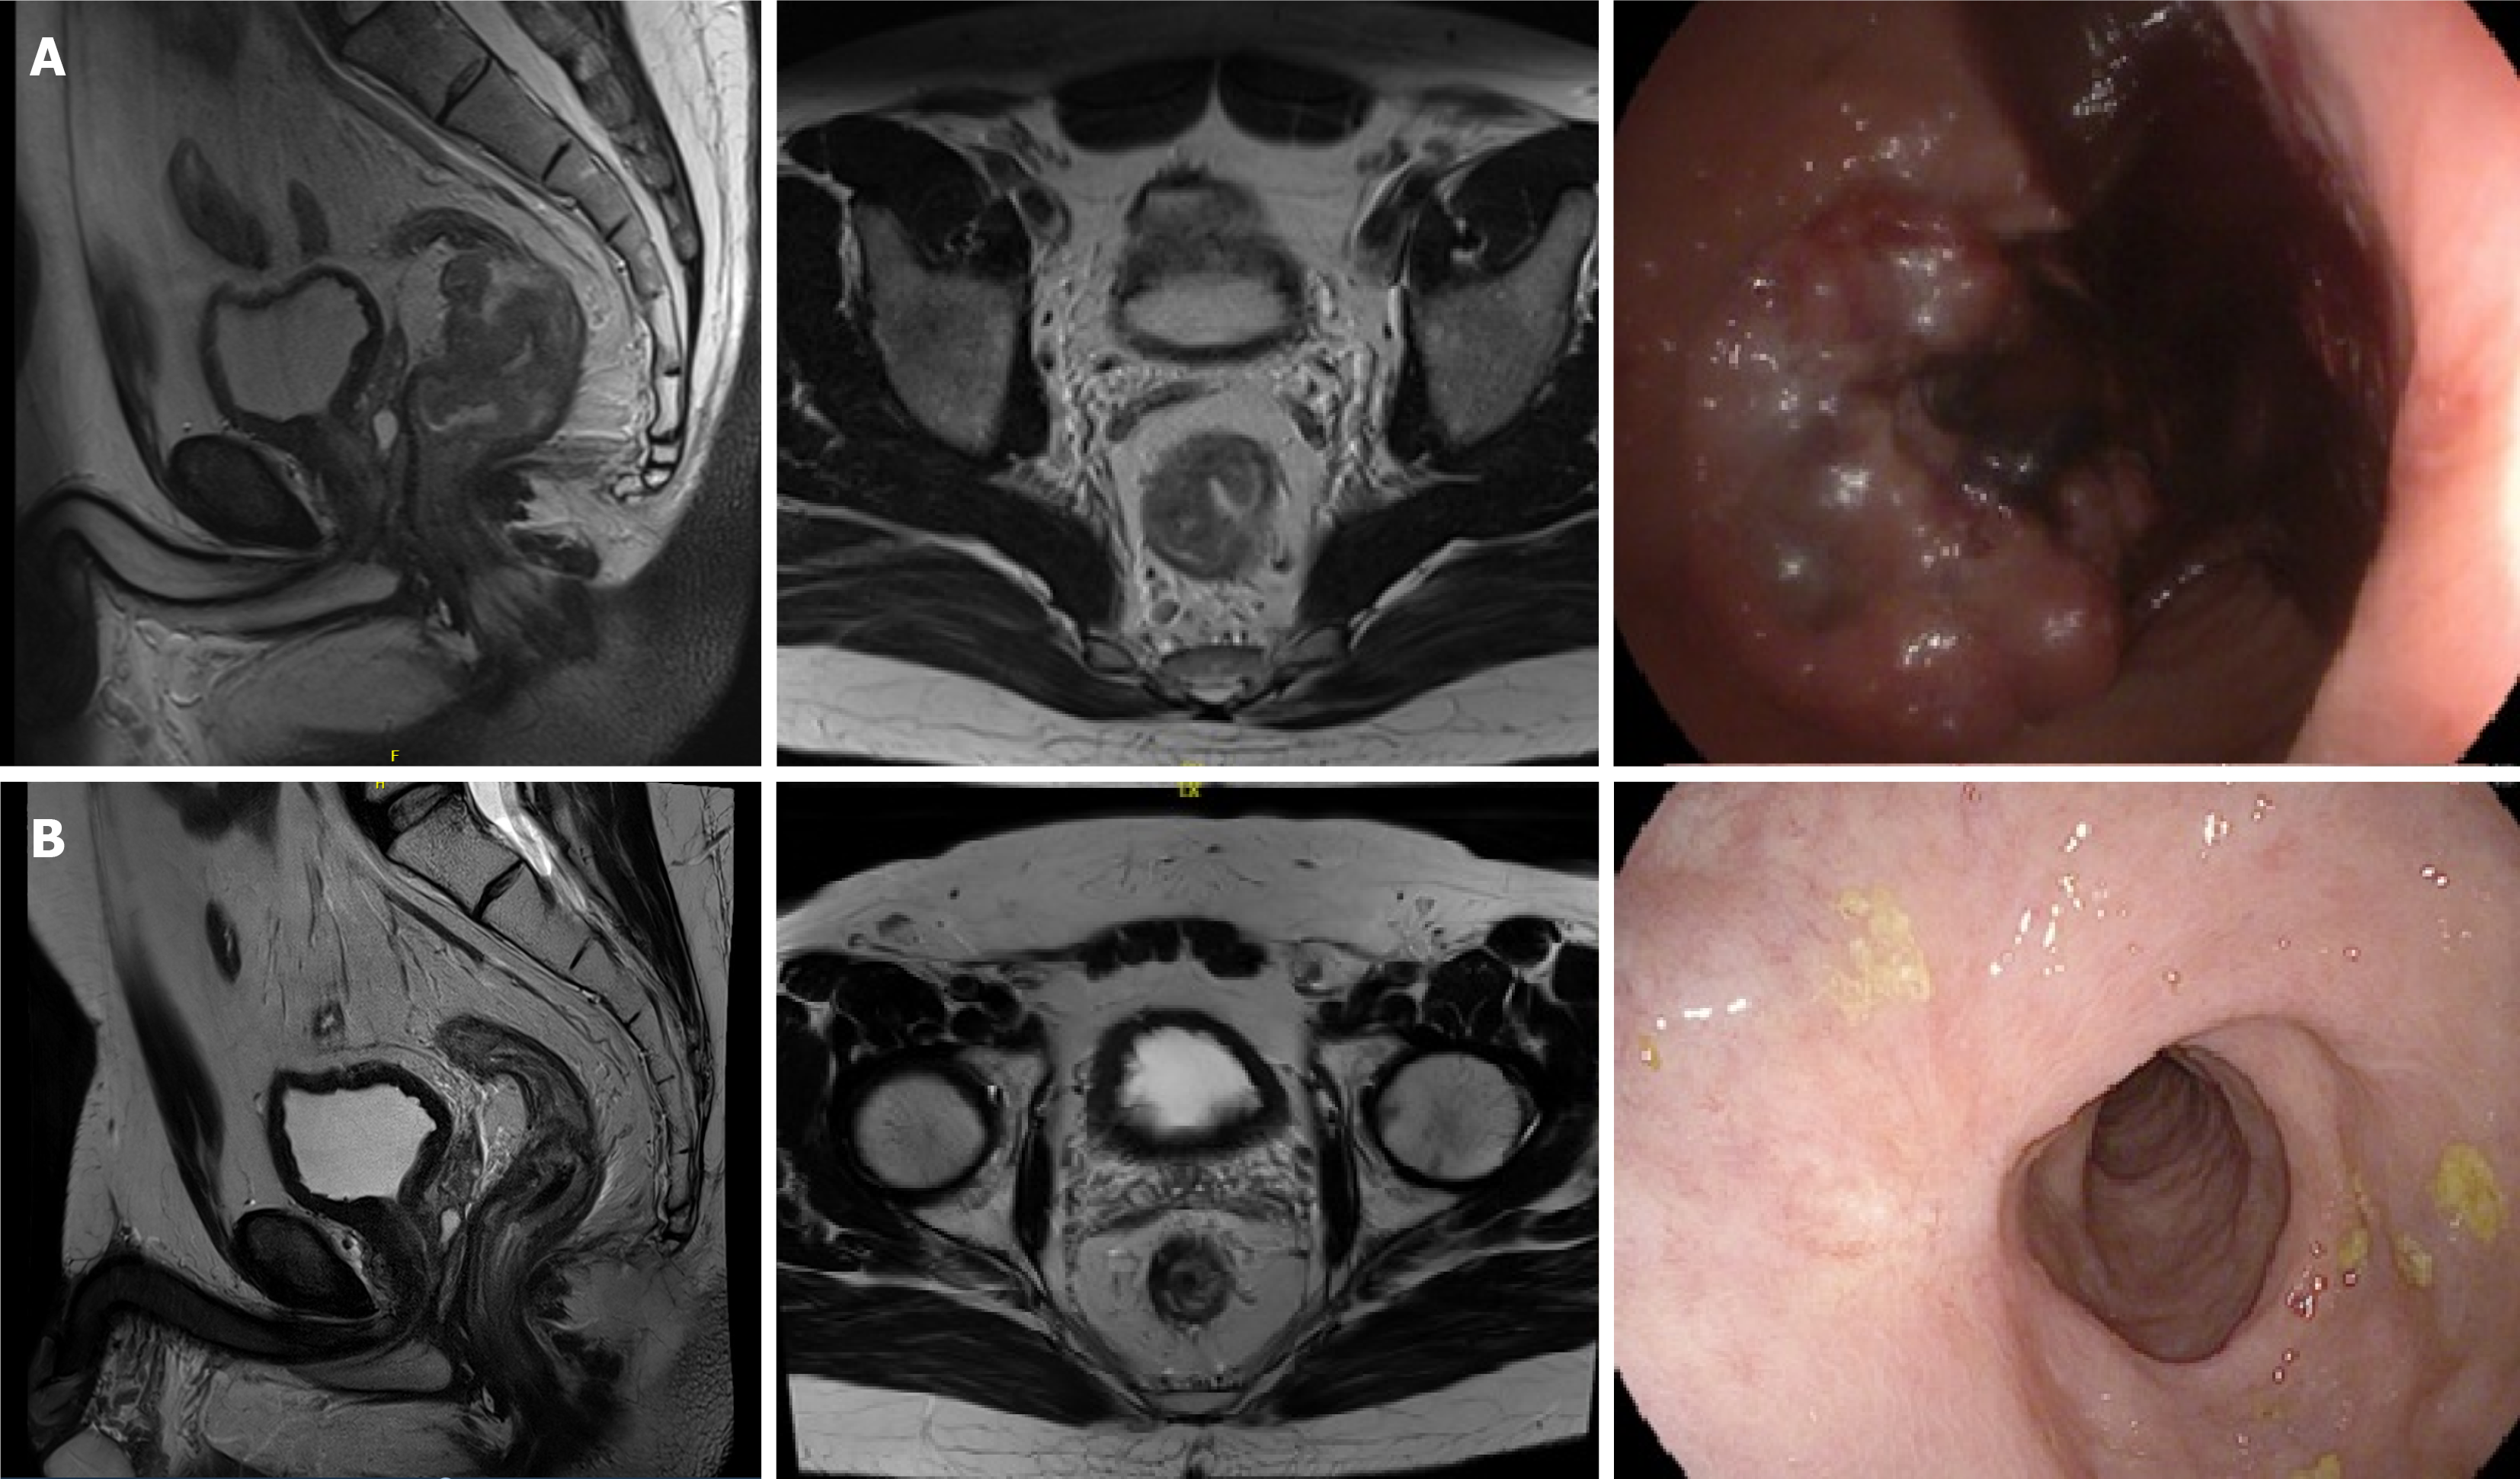
Figure 9 Case 8.
A: Sagittal and axial magnetic resonance imaging (MRI) and colonoscopy at diagnosis; B: Sagittal and axial MRI and colonoscopy after completion of neoadjuvant immune checkpoint inhibitor therapy.
- Citation: Manuel-Vazquez A, Soria Tristán M, Luján DR, Gortázar de las Casas S, Valle Rubio A, Ramos Rodríguez JL, García-Septiem J. Rethinking treatment for non-metastatic deficient mismatch repair colorectal and small bowel cancers. World J Clin Oncol 2026; 17(9): 125491
- URL: https://www.wjgnet.com/2218-4333/full/v17/i9/125491.htm
- DOI: https://dx.doi.org/10.5306/wjco.125491