
















Published online Oct 15, 2026. doi: 10.4251/wjgo.124433
Revised: July 23, 2026
Accepted: August 26, 2026
Published online: October 15, 2026
Processing time: 116 Days and 18.5 Hours
Postoperative ileus (POI) commonly complicates recovery after laparoscopic colorectal cancer surgery. Transcutaneous electrical nerve stimulation (TEA) may promote gastrointestinal motility, but its role in this setting is unclear.
To evaluated the efficacy and safety of TEA for POI in patients undergoing lap
This prospective study included 100 patients who underwent laparoscopic radical resection for colorectal cancer in the Department of Gastrointestinal Oncology, the Second Affiliated Hospital of Hainan Medical University, from December 2025 to March 2026. Among them, 50 patients who received TEA combined with routine postoperative care were assigned to the experimental group, while 50 patients who underwent the same surgical procedure and received routine nursing care and prokinetic therapy without TEA were assigned to the control group. Baseline characteristics, time to first flatus, time to first defecation, time to liquid diet in
There were no significant differences in sex, age, disease characteristics, or other baseline variables between the experimental and control groups (P > 0.05). Compared with the control group, patients in the experimental group had significantly shorter time to first flatus, time to first defecation, time to liquid diet intake, drainage tube removal time, and postoperative length of hospital stay, with statistically significant differences between the two groups (P < 0.05). The PONV score at 24 hours after surgery was significantly lower in the experimental group than in the control group (P < 0.05), whereas no significant difference was observed in the PONV score at 48 hours after surgery (P > 0.05). Pain VAS scores at 12 hours and 24 hours after surgery were significantly lower in the experimental group than in the control group (P < 0.05), while no significant difference was found at 48 hours after surgery (P > 0.05). In addition, sleep VAS scores at 24 hours and 48 hours after surgery were significantly higher in the experimental group than in the control group (P < 0.05). Although the incidence of postoperative gastro
TEA may effectively promote the recovery of gastrointestinal function, alleviate POI, and shorten postoperative hospital stay in patients undergoing laparoscopic surgery for colorectal cancer in Hainan. It may also reduce early PONV, relieve early postoperative pain, and improve postoperative sleep quality. This intervention is simple to perform, safe, and well-tolerated, with no serious adverse reactions observed. Therefore, TEA may have clinical application value as an adjunctive perioperative rehabilitation strategy for patients with colorectal cancer undergoing laparoscopic surgery.
Core Tip: This prospective study confirms that transcutaneous electrical nerve stimulation effectively promotes gastrointestinal function recovery after laparoscopic colorectal cancer surgery, shortening flatus/defecation time and hospital stay, reducing early postoperative nausea, vomiting and pain, improving sleep quality with good safety, providing a non-invasive rehabilitation strategy for patients in Hainan.
- Citation: Zhong X, Lin SG, Zhang DY, Li PP, Bai FH. Clinical observation of transcutaneous electrical nerve stimulation on postoperative ileus after laparoscopic surgery for colorectal cancer. World J Gastrointest Oncol 2026; 18(10): 124433
- URL: https://www.wjgnet.com/1948-5204/full/v18/i10/124433.htm
- DOI: https://dx.doi.org/10.4251/wjgo.124433
Colorectal cancer is a highly prevalent malignant tumor of the digestive tract worldwide, ranking third in incidence among both males and females, with its incidence and mortality rates remaining among the highest of all malignancies[1]. With the rapid development of minimally invasive surgical techniques, laparoscopic radical resection for colorectal cancer has become the preferred surgical approach in clinical practice due to its advantages of minimal trauma, low intraoperative blood loss, and rapid postoperative recovery[2]. Nevertheless, the incidence of postoperative ileus (POI) remains as high as 40%-60%, which is mainly characterized by inhibited gastrointestinal peristalsis, cessation of anal exhaust and defecation, abdominal distension, nausea and vomiting, and other symptoms[3]. Although POI is a self-limiting complication, it aggravates patients’ physical discomfort, impairs quality of life, prolongs hospital stay, and increases the economic burden of medical care[4]. At present, conventional interventions for POI after colorectal cancer surgery include fasting, gastrointestinal decompression, intravenous fluid replacement, nutritional support, and prokinetic drugs. However, such treatments yield unsatisfactory outcomes in some patients[5], and pharmacological interventions are accompanied by certain adverse reactions. Traditional Chinese medicine external therapy and physical intervention have gradually become research hotspots for promoting the recovery of postoperative gastrointestinal function. Transcutaneous electrical nerve stimulation (TEA) is a non-invasive physical therapy that regulates gas
A total of 50 patients who underwent laparoscopic radical resection for colorectal cancer in the Department of Gastrointestinal Oncology, the Second Affiliated Hospital of Hainan Medical University, from December 2025 to March 2026 were prospectively selected as the experimental group; meanwhile, 50 patients who underwent the same surgery during the same period but did not receive TEA treatment were enrolled as the control group. To minimize selection bias, patient allocation was not based on investigator discretion or patient preference. Instead, a computer-generated random number sequence was used to assign enrolled patients to either the experimental group or the control group in a 1:1 ratio. The randomization sequence was concealed in opaque, sealed envelopes that were opened sequentially by an inde
Inclusion criteria: (1) Confirmed diagnosis of colorectal cancer (tumor-nodes-metastasis stage I-III) by preoperative colonoscopy and pathological biopsy; (2) Underwent laparoscopic radical resection for colorectal cancer (Dixon procedure, Miles procedure, etc.) with a smooth surgical process and no intraoperative complications such as massive hemorrhage or organ injury; (3) Developed POI symptoms (cessation of anal exhaust and defecation for ≥ 24 hours, accompanied by abdominal distension, nausea, etc.); (4) Aged > 18 years, regardless of gender; and (5) Patients and their family members provided informed consent, with complete clinical data and ability to complete follow-up throughout the study.
Exclusion criteria: (1) Complicated with severe dysfunction of heart, liver, kidney, lung and other organs, unable to tolerate surgery and TEA intervention; (2) Preoperative presence of gastrointestinal motility disorders, intestinal obstruction, intestinal adhesion and other diseases; (3) Allergic to TEA electrode pads or conductive gel; (4) Complicated with mental illness or cognitive dysfunction, unable to cooperate with intervention and follow-up; (5) Intraoperative conversion to open surgery, or postoperative occurrence of severe complications such as infection and hemorrhage; and (6) Pregnant or lactating women.
Both groups received the conventional enhanced recovery after surgery (ERAS) protocol[9], including early postoperative ambulation, fluid management, nutritional support, analgesia, and gradual oral intake. For the detailed procedures, please refer to Figures 1 and 2.


The experimental group received additional TEA treatment on the basis of conventional treatment: Instrument: Transcutaneous electrical nerve stimulator. Acupoints: Bilateral Zusanli (ST36), located 3 cun below the lateral knee joint, on the tibialis anterior muscle. Timing: Started 6 hours after surgery, twice a day, 30 minutes each time, until gastro
Treatment course: Once each in the morning and afternoon, continuous intervention until discharge. Precautions: The patient’s response was closely observed during the intervention. If adverse reactions such as skin redness, itching, dizziness, or palpitations occurred, the intervention was stopped immediately, and the position of the electrode pads or the current intensity was adjusted. After the intervention, the local skin was cleaned to avoid long-term application of electrode pads on the same site, so as to prevent skin damage. This study was approved by the Ethics Committee of the Second Affiliated Hospital of Hainan Medical University (approval No. 2026-K102-01).
(1) Primary indicators: Time to first anal exhaust (time from the end of surgery to the first anal exhaust). Time to first anal defecation (time from the end of surgery to the first anal defecation); (2) Secondary indicators: Postoperative hospital stay (time from the day of surgery to discharge); time to first ambulation after surgery; time to tolerate liquid diet and semi-liquid diet; (3) Symptom scores: Postoperative nausea and vomiting (PONV) score (0-3 points): 0 points: No nausea or vomiting; 1 point: Nausea only; 2 points: Transient vomiting; 3 points: Severe vomiting. Visual analogue scale (VAS) pain score (0-10 points); VAS sleep score (0-10 points); and (4) Complications and safety: The incidence of postoperative complications such as abdominal distension, nausea and vomiting, intestinal adhesion, and intestinal obstruction in both groups; the incidence of adverse reactions such as skin damage, allergy, dizziness, and palpitations in the experimental group during TEA intervention was recorded.
The sample size was estimated a priori based on the primary outcome (time to first flatus). Referring to the randomized controlled study by Zhou et al[10], in which the time to first flatus was 55.63 ± 16.74 hours in the TEA group and 72.60 ± 20.92 hours in the control group, the expected intergroup difference (Δ) was 16.97 hours, and the pooled standard deviation (σ) was calculated as 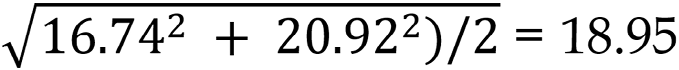 hours. Using the standard formula for two independent samples: n = 2 × (Z1-α/2 + Z1-β)2 × σ2/Δ2, with a two-sided significance level (α) of 0.05 and a statistical power (1-β) of 0.80 (Z1-α/2 = 1.96, Z1-β = 0.84), the required sample size was calculated as n = 2 × (1.96 + 0.84)2 × 18.952/16.972 = 19.57, indicating that at least 20 patients per group were needed. Accounting for a 10% potential dropout or invalid data rate, the adjusted sample size was 20/(1 - 0.10) = 22.22, rounded up to 23 patients per group, or 46 patients in total. In this study, we ultimately enrolled 100 patients (50 per group). SPSS 27.0 statistical software was used for data analysis. Measurement data conforming to normal distribution were expressed as mean ± SD, and independent samples t-test was used for comparison between groups; measurement data with non-normal distribution were expressed as median (interquartile range), and Mann-Whitney U test was used for comparison between groups. Count data were expressed as n (%), and χ2 test was used for comparison between groups. P < 0.05 was considered statistically significant.
The experimental group consisted of patients who underwent laparoscopic radical resection for colorectal cancer in the Department of Gastrointestinal Oncology, the Second Affiliated Hospital of Hainan Medical University, from December 2025 to March 2026. The control group included patients who underwent the same surgical procedure in our hospital during the same period and only received routine nursing and gastrointestinal motility-promoting treatment after surgery (without TEA intervention). There were no statistically significant differences in baseline data such as age, body mass index, gender, operation duration, intraoperative blood loss, past medical history, and American Society of Anesthesiologists classification between the two groups (all P > 0.05), indicating that the two groups were comparable (Table 1).
| Indicators | Experimental group (n = 50) | Control group (n = 50) | P value |
| Gender | Male: 34 (68); female: 16 (32) | Male: 30 (0.6); female: 20 (0.4) | 0.405 |
| Age (years) | 63.80 ± 13.532 | 63.52 ± 11.193 | 0.308 |
| Body mass index (kg/m2) | 22.224 ± 2.655 | 23.064 ± 1.640 | 0.083 |
| Smoking history | Yes (18); no (32) | Yes (26); no (24) | 0.107 |
| Drinking history | Yes (16); no (34) | Yes (25); no (25) | 0.067 |
| Hypertension | Yes (13); no (37) | Yes (12); no (38) | 0.817 |
| Diabetes mellitus | Yes (12); no (38) | Yes (7); no (43) | 0.202 |
| American Society of Anesthesiologists classification | I (5); II (33); III (12) | I (1); II (31); III (18) | 0.140 |
| Surgical site | Colon (19); rectum (16); colon + rectum (15) | Colon (14); rectum (15); colon + rectum (21) | 0.409 |
| Operation duration (minutes) | 210.42 ± 80.318 | 192.98 ± 60.092 | 0.087 |
| Intraoperative blood loss (mL) | 43.50 ± 31.073 | 52.80 ± 32.122 | 0.769 |
Compared with the non-TEA group, the TEA group had significantly shorter time to first anal exhaust, time to first oral liquid intake, time to first defecation, time to drainage tube removal, and postoperative hospital stay (all P < 0.05), suggesting that TEA can effectively promote the recovery of postoperative gastrointestinal function (Table 2).
| Indicators | Experimental group (n = 50) | Control group (n = 50) | T value | P value |
| Time to first anal exhaust (hours) | 55.60 ± 21.687 | 67.16 ± 27.792 | -2.266 | 0.023 |
| Time to first liquid diet intake (hours) | 79.14 ± 36.583 | 93.26 ± 31.094 | -2.624 | 0.009 |
| Time to first anal defecation (days) | 3.36 ± 0.964 | 3.86 ± 1.246 | -2.211 | 0.027 |
| Time to drainage tube removal (days) | 7.44 ± 2.666 | 8.16 ± 2.034 | -2.600 | 0.009 |
| Postoperative hospital stay (days) | 9.58 ± 3.453 | 11.34 ± 4.231 | -3.211 | 0.001 |
The PONV score of the experimental group at 24 hours after surgery was significantly lower than that of the control group, and the difference was statistically significant (P < 0.05); there was no statistically significant difference in PONV score between the two groups at 48 hours after surgery (P > 0.05), indicating that TEA can effectively improve early PONV symptoms. The VAS pain scores of the experimental group at 12 hours and 24 hours after surgery were both lower than those of the control group, and the differences were statistically significant (P < 0.05); the VAS pain scores at 48 hours after surgery were similar between the two groups, with no statistically significant difference (P > 0.05), indicating that TEA has a better relieving effect on early postoperative pain. The VAS sleep scores of the experimental group at 24 hours and 48 hours after surgery were both higher than those of the control group, and the differences were statistically significant (P < 0.05), suggesting that TEAS can significantly improve the postoperative sleep quality of patients. The incidence of gastrointestinal symptoms in the two groups was 22% and 38%, respectively, with no statistically significant difference between the two groups (P > 0.05), but the incidence in the experimental group was numerically lower, showing a certain improvement trend. No serious complications such as intestinal adhesion or intestinal obstruction occurred in either group, and the overall safety was good (Tables 3 and 4).
| Indicators | Experimental group (n = 50) | Control group (n = 50) | t value/χ2 value | P value |
| Postoperative PONV score at 24 hours (points) | 0.480 ± 0.614 | 0.880 ± 0.521 | -3.560 | < 0.001 |
| Postoperative PONV score at 48 hours (points) | 0.020 ± 0.141 | 0.100 ± 0.303 | -1.676 | 0.094 |
| Gastrointestinal symptoms | 11 (22) | 19 (38) | 3.048 | 0.081 |
| Indicators | Experimental group (n = 50) | Control group (n = 50) | T value | P value |
| VAS pain score at 12 hours after surgery (points) | 5.880 ± 1.459 | 6.510 ± 1.264 | -2.216 | 0.027 |
| VAS pain score at 24 hours after surgery (points) | 4.280 ± 1.278 | 5.200 ± 1.348 | -3.258 | 0.001 |
| VAS pain score at 48 hours after surgery (points) | 2.140 ± 0.881 | 2.460 ± 0.813 | -1.724 | 0.085 |
| VAS sleep score at 24 hours after surgery (points) | 5.740 ± 1.065 | 5.240 ± 1.153 | -2.258 | 0.024 |
| VAS sleep score at 48 hours after surgery (points) | 6.800 ± 1.088 | 6.220 ± 1.166 | -2.624 | 0.009 |
All 50 patients in the experimental group completed the full course of TEA intervention. During the intervention, only 2 cases had slight local skin redness, without pruritus, burns, allergies, or systemic adverse reactions such as dizziness, palpitations, or nausea, with an adverse reaction rate of 3.33%. After adjusting the position of the electrode pads and shortening the single application time, the symptom of skin redness relieved spontaneously, which did not affect the subsequent intervention and the patient’s recovery.
POI is a physiological and pathological response characterized by temporary inhibition of gastrointestinal peristalsis after abdominal surgery. Its pathogenesis is complex, and it is currently believed to be associated with various factors such as surgical trauma, anesthetic drug inhibition, neuroendocrine disorders, inflammatory responses, and reduced post
Elderly patients account for a high proportion of colorectal cancer patients. Such patients have weak gastrointestinal mucosal barrier function and insufficient gastrointestinal motility, making them more prone to gastrointestinal peristalsis inhibition after surgery, which prolongs the course of ileus and increases the risk of complications. Therefore, it is of great clinical significance to find a safe, effective, and easy-to-operate intervention method to shorten the course of POI after laparoscopic colorectal cancer surgery in Hainan area and promote the recovery of patients’ gastrointestinal function.
In recent years, the concept of ERAS has been widely applied in abdominal surgery. TEA, as an important component of ERAS, has been proven to effectively reduce the intensity of activity pain in laparoscopic patients at 6 hours, 24 hours, and 48 hours after surgery[17]. This study adopted a prospective controlled design, focusing on the intervention effect of TEA on POI after laparoscopic colorectal cancer surgery. The results confirmed that TEA stimulation at bilateral Zusanli acupoints can significantly accelerate the recovery of gastrointestinal function after laparoscopic colorectal cancer surgery, effectively shorten the duration of ileus, and the time to first exhaust and defecation. At the same time, it can reduce the degree of PONV, relieve postoperative pain, and improve patients’ sleep quality with definite curative effect and good safety, providing a new feasible path for the clinical intervention of POI after laparoscopic colorectal cancer surgery.
As a non-invasive physical therapy method, the mechanism of TEA in intervening POI mainly focuses on the regulation of gastrointestinal motility, which can exert its effect through multiple pathways and targets, related to regulating gastrointestinal motility-related neural pathways, inhibiting inflammatory responses, and promoting the secretion of gastrointestinal hormones[18-20]. Zusanli acupoint is the He-sea acupoint of the Stomach Meridian and the lower He-sea acupoint of the stomach, which is a core acupoint for regulating gastrointestinal function, with the effects of regulating gastrointestinal function and promoting gastrointestinal peristalsis[21]. TEA transmits low-frequency pulsed current to gastrointestinal-related nerves through the skin to achieve precise regulation of gastrointestinal motility: First, it activates the vagus nerve pathway[22], directly promotes gastrointestinal smooth muscle contraction, and accelerates the recovery of gastrointestinal peristalsis function; second, it inhibits excessive sympathetic nerve excitement, reduces visceral hypersensitivity, thereby relieving postoperative pain and nausea and vomiting symptoms[23]; third, it inhibits the release of inflammatory factors, reduces intestinal mucosal and retroperitoneal inflammatory responses, relieves intestinal wall edema, reduces abdominal inflammatory exudation, decreases the total amount of drainage fluid, and shortens the indwelling time of drainage tubes, creating favorable conditions for the recovery of gastrointestinal peristalsis[24]; fourth, it regulates the levels of gastrointestinal hormones such as motilin and gastrin, promotes the orderly recovery of gastrointestinal motility, and fundamentally improves the state of postoperative gastrointestinal function inhibition[25].
Compared with traditional invasive electroacupuncture therapy, TEA has the advantages of non-invasive, painless, and easy-to-operate non-invasive physical intervention. It does not require needle puncture to break the skin, effectively avoiding problems such as patients’ fear of needles, pain, and local infection. Patients have higher acceptance and compliance, especially suitable for postoperative patients with weak physical condition, the elderly, those with multiple underlying diseases, or those intolerant to acupuncture, which is more in line with the rehabilitation needs of patients after laparoscopic colorectal cancer surgery. The results of this study are basically consistent with Clinical significance and benchmarking against existing literature. Beyond statistical significance, the clinical relevance of the observed improvements must be explicitly quantified. Based on the intergroup comparisons derived from the data presented in Table 2, the TEA group exhibited clinically meaningful advantages over the control group, with mean reductions of 11.6 hours in time to first flatus (67.16 ± 27.79 hours vs 55.60 ± 21.69 hours), 12.0 hours (0.5 days) in time to first defecation (3.86 ± 1.25 days vs 3.36 ± 0.96 days), and a shortening of postoperative hospital stay by 1.76 days (11.34 ± 4.23 days vs 9.58 ± 3.45 days). These numerical gains are not mere statistical artifacts but carry tangible clinical dividends. It is important to interpret these numerical gains beyond mere statistical significance. Although the 11.6-hour and 12.0-hour reductions in flatus and defecation, respectively, represent relatively moderate improvements on their own, they should not be viewed in isolation when evaluating the overall clinical impact. Critically, the 1.76-day (approximately 42 hours) reduction in postoperative hospital stay serves as the most integrative indicator of overall recovery, reflecting a substantially accelerated convalescence. A shorter hospitalization of nearly 2 days not only reduces patients’ exposure to hospital-related risks and facilitates earlier return to daily activities, but also translates into considerable cost savings and optimized bed utilization - benefits that are of direct relevance to both individual patients and regional healthcare systems. Collectively, these concurrent improvements - earlier defecation, faster oral intake, and shorter hospital stay - reflect a substantially accelerated overall recovery.
Benchmarking our results against the well-documented physiological course of postoperative recovery, laparoscopic surgery itself is known to confer a substantial advantage over traditional open surgery in terms of gastrointestinal motility preservation[13-16]. Within this context, the additional 12-hour earlier defecation observed in our TEA group represents a meaningful incremental gain that complements the inherent benefits of the minimally invasive approach, likely attributable to TEA’s distinct neuromodulatory effects on vagal and sympathetic pathways. In the context of ERAS implementation, the reduction in postoperative hospital stay from 11.34 days to 9.58 days, coupled with a mean de
The research conclusions of many researchers that transcutaneous electrical stimulation at Zusanli acupoint can significantly promote the recovery of gastrointestinal function after laparoscopic colorectal cancer surgery[26] and other studies on the treatment of POI, further confirming that distal lower extremity acupoint stimulation can safely and effectively promote the recovery of gastrointestinal motility after abdominal surgery, providing an objective basis for clinical acupoint selection.
Combined with the regional characteristics of Hainan area and the characteristics of patient population, the clinical value of this study is more prominent. Colorectal cancer patients in Hainan area are mainly middle-aged and elderly groups, often complicated with underlying diseases such as hypertension, diabetes, and obesity. Postoperatively, their body tolerance is low, the recovery speed of gastrointestinal function is relatively slow, and they have higher require
However, this study still has certain limitations: (1) Limitations in study design: This study is a single-center, prospective controlled study, not a randomized double-blind controlled trial. Although the baseline data of the two groups are comparable, there are still certain selection bias and information bias, which may have a certain impact on the extrapolation of the results; (2) Limited sample size and observation period: The sample size of this study is relatively limited, and the observation only lasted until the patient was discharged. No long-term follow-up was conducted, so it is impossible to clarify the impact of TEA on the long-term gastrointestinal function, quality of life, and tumor prognosis of patients, and the research depth needs to be further expanded; (3) No stratified comparison of intervention parameters: This study only used fixed acupoints and fixed stimulation parameters, and did not conduct stratified comparison of different stimulation frequencies, intervention durations, and acupoint compatibility, so it is impossible to determine the optimal scheme of TEA for intervening POI; (4) Insufficient in-depth mechanism research: This study only observed from the perspective of clinical efficacy, did not conduct in-depth detection of objective indicators such as inflammatory factors, gastrointestinal hormones, and intestinal barrier function, and did not conduct in-depth exploration of the molecular mechanism and neural regulation pathway of TEA in improving POI; and (5) Limited regional and population representativeness: This study only included patients from a single center in Hainan area, and the research conclusions are mainly applicable to the local population in Hainan. When promoting to other regions and populations with different physical conditions, it is still necessary to expand the sample size and carry out multi-center studies to verify.
TEA stimulation at bilateral Zusanli acupoints can safely and effectively promote the recovery of gastrointestinal function after laparoscopic colorectal cancer surgery, shorten the course of ileus and the time to drainage tube removal, relieve postoperative pain and nausea and vomiting symptoms, improve patients’ sleep quality. It is easy to operate and has high patient acceptance, which is in line with the rehabilitation characteristics of patients with laparoscopic colorectal cancer in Hainan area and has high clinical promotion value. In view of the limitations of this study, multi-center, large-sample, randomized double-blind controlled studies can be carried out in the future to optimize TEA intervention parameters, further explore its mechanism of action, and verify its clinical efficacy and long-term safety, so as to provide more reliable clinical basis for enhanced recovery after laparoscopic colorectal cancer surgery.
| 1. | Siegel RL, Kratzer TB, Wagle NS, Sung H, Jemal A. Cancer statistics, 2026. CA Cancer J Clin. 2026;76:e70043. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 414] [Cited by in RCA: 300] [Article Influence: 300.0] [Reference Citation Analysis (0)] |
| 2. | Batsis C. Proximal gastric cancer: advances of laparoscopic surgery. Surg Endosc. 2011;25:2761-2763. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 3] [Cited by in RCA: 4] [Article Influence: 0.3] [Reference Citation Analysis (0)] |
| 3. | Sommer NP, Schneider R, Wehner S, Kalff JC, Vilz TO. State-of-the-art colorectal disease: postoperative ileus. Int J Colorectal Dis. 2021;36:2017-2025. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 14] [Cited by in RCA: 42] [Article Influence: 8.4] [Reference Citation Analysis (6)] |
| 4. | Boeckxstaens GE, de Jonge WJ. Neuroimmune mechanisms in postoperative ileus. Gut. 2009;58:1300-1311. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 228] [Cited by in RCA: 275] [Article Influence: 16.2] [Reference Citation Analysis (6)] |
| 5. | Wang Y, Yang JW, Yan SY, Lu Y, Han JG, Pei W, Zhao JJ, Li ZK, Zhou H, Yang NN, Wang LQ, Yang YC, Liu CZ. Electroacupuncture vs Sham Electroacupuncture in the Treatment of Postoperative Ileus After Laparoscopic Surgery for Colorectal Cancer: A Multicenter, Randomized Clinical Trial. JAMA Surg. 2023;158:20-27. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 103] [Cited by in RCA: 92] [Article Influence: 30.7] [Reference Citation Analysis (7)] |
| 6. | Zhang M, Zhang H, Li P, Li J. Effect of transcutaneous electrical acupoint stimulation on the quality of postoperative recovery: a meta-analysis. BMC Anesthesiol. 2024;24:104. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 1] [Cited by in RCA: 10] [Article Influence: 5.0] [Reference Citation Analysis (1)] |
| 7. | Xiao Y, Yang F, Zhou J, Huang Y, Xiao Y. Effect of transcutaneous electrical acupoint stimulation on length of stay for patients after undergoing surgery for colorectal cancer: a systematic review and meta-analysis of randomized controlled trials. Front Med (Lausanne). 2025;12:1503714. [RCA] [PubMed] [DOI] [Full Text] [Cited by in RCA: 1] [Reference Citation Analysis (0)] |
| 8. | Li S, Liu KX, Deng XM, Fang XM, Xia ZY, Wang YL, Yu JB, Li JB, Shang Y, Zhou J. [Expert consensus on the prevention and treatment of postoperative gastrointestinal dysfunction]. Guoji Mazuixue Yu Fusu Zazhi. 2021;42:1133-1142. [DOI] [Full Text] |
| 9. | Chinese Society of Surgery, Chinese Society of Anesthesiology. [Chinese expert consensus and pathway management guidelines for enhanced recovery after surgery (2018 edition)]. Zhonghua Mazuixue Zazhi. 2018;38:8-13. [DOI] [Full Text] |
| 10. | Zhou X, Cao SG, Tan XJ, Liu XD, Li ZQ, Kong LX, Tian YL, Liu D, Shen S, Sun YQ, Jiang HT, Zhou YB. Effects of Transcutaneous Electrical Acupoint Stimulation (TEAS) on Postoperative Recovery in Patients with Gastric Cancer: A Randomized Controlled Trial. Cancer Manag Res. 2021;13:1449-1458. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 4] [Cited by in RCA: 45] [Article Influence: 9.0] [Reference Citation Analysis (1)] |
| 11. | Nishimura J, Satoh T, Fukunaga M, Takemoto H, Nakata K, Ide Y, Fukuzaki T, Kudo T, Miyake Y, Yasui M, Morita S, Sakai D, Uemura M, Hata T, Takemasa I, Mizushima T, Ohno Y, Yamamoto H, Sekimoto M, Nezu R, Doki Y, Mori M; Multi-center Clinical Study Group of Osaka, Colorectal Cancer Treatment Group (MCSGO). Combination antiemetic therapy with aprepitant/fosaprepitant in patients with colorectal cancer receiving oxaliplatin-based chemotherapy (SENRI trial): a multicentre, randomised, controlled phase 3 trial. Eur J Cancer. 2015;51:1274-1282. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 40] [Cited by in RCA: 56] [Article Influence: 5.1] [Reference Citation Analysis (0)] |
| 12. | Zhao JK, Chen NZ, Zheng JB, He S, Sun XJ. Laparoscopic versus open surgery for rectal cancer: Results of a systematic review and meta-analysis on clinical efficacy. Mol Clin Oncol. 2014;2:1097-1102. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 38] [Cited by in RCA: 35] [Article Influence: 2.9] [Reference Citation Analysis (0)] |
| 13. | Veldkamp R, Kuhry E, Hop WC, Jeekel J, Kazemier G, Bonjer HJ, Haglind E, Påhlman L, Cuesta MA, Msika S, Morino M, Lacy AM; COlon cancer Laparoscopic or Open Resection Study Group (COLOR). Laparoscopic surgery versus open surgery for colon cancer: short-term outcomes of a randomised trial. Lancet Oncol. 2005;6:477-484. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 1904] [Cited by in RCA: 1688] [Article Influence: 80.4] [Reference Citation Analysis (3)] |
| 14. | Leung KL, Kwok SP, Lam SC, Lee JF, Yiu RY, Ng SS, Lai PB, Lau WY. Laparoscopic resection of rectosigmoid carcinoma: prospective randomised trial. Lancet. 2004;363:1187-1192. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 729] [Cited by in RCA: 631] [Article Influence: 28.7] [Reference Citation Analysis (1)] |
| 15. | Reza MM, Blasco JA, Andradas E, Cantero R, Mayol J. Systematic review of laparoscopic versus open surgery for colorectal cancer. Br J Surg. 2006;93:921-928. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 293] [Cited by in RCA: 255] [Article Influence: 12.8] [Reference Citation Analysis (1)] |
| 16. | Guillou PJ, Quirke P, Thorpe H, Walker J, Jayne DG, Smith AM, Heath RM, Brown JM; MRC CLASICC trial group. Short-term endpoints of conventional versus laparoscopic-assisted surgery in patients with colorectal cancer (MRC CLASICC trial): multicentre, randomised controlled trial. Lancet. 2005;365:1718-1726. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 2561] [Cited by in RCA: 2260] [Article Influence: 107.6] [Reference Citation Analysis (7)] |
| 17. | Sun K, Xing T, Zhang F, Liu Y, Li W, Zhou Z, Fang L, Yu L, Yan M. Perioperative Transcutaneous Electrical Acupoint Stimulation for Postoperative Pain Relief Following Laparoscopic Surgery: A Randomized Controlled Trial. Clin J Pain. 2017;33:340-347. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 18] [Cited by in RCA: 30] [Article Influence: 3.3] [Reference Citation Analysis (0)] |
| 18. | Liu YL, Li SS, Yang YR, Zhao YH, Li WX, Hao JX, Zhang B, Fan XJ. Research progress on the molecular mechanism of electroacupuncture at "Zusanli" (ST36) for regulating gastrointestinal dysfunction. Zhen Ci Yan Jiu. 2023;48:1048-1054. [RCA] [PubMed] [DOI] [Full Text] [Cited by in RCA: 10] [Reference Citation Analysis (0)] |
| 19. | Liu Y, Sethi NS, Hinoue T, Schneider BG, Cherniack AD, Sanchez-Vega F, Seoane JA, Farshidfar F, Bowlby R, Islam M, Kim J, Chatila W, Akbani R, Kanchi RS, Rabkin CS, Willis JE, Wang KK, McCall SJ, Mishra L, Ojesina AI, Bullman S, Pedamallu CS, Lazar AJ, Sakai R; Cancer Genome Atlas Research Network, Thorsson V, Bass AJ, Laird PW. Comparative Molecular Analysis of Gastrointestinal Adenocarcinomas. Cancer Cell. 2018;33:721-735.e8. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 483] [Cited by in RCA: 418] [Article Influence: 52.3] [Reference Citation Analysis (4)] |
| 20. | Kalkan Ç, Soykan I. The Relations Among Serum Ghrelin, Motilin and Gastric Emptying and Autonomic Function in Autoimmune Gastritis. Am J Med Sci. 2018;355:428-433. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 3] [Cited by in RCA: 8] [Article Influence: 1.0] [Reference Citation Analysis (1)] |
| 21. | Li D, Sun RR, Li QL, Ma Q, Zeng YL, Jia XZ, Wang J. [Acupuncture combined with opioid drugs on moderate and severe cancer pain: a randomized controlled trial]. Zhongguo Zhen Jiu. 2020;40:257-261. [RCA] [PubMed] [DOI] [Full Text] [Cited by in RCA: 4] [Reference Citation Analysis (0)] |
| 22. | Yang ZK, Wu ML, Xin JJ, He W, Su YS, Shi H, Wang XY, Hu L, Jing XH, Litscher G. Manual acupuncture and laser acupuncture for autonomic regulations in rats: observation on heart rate variability and gastric motility. Evid Based Complement Alternat Med. 2013;2013:276320. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 20] [Cited by in RCA: 27] [Article Influence: 2.1] [Reference Citation Analysis (0)] |
| 23. | Schlünzen L, Vafaee MS, Cold GE. Acupuncture of LI-4 in anesthetized healthy humans decreases cerebral blood flow in the putamen measured with positron emission tomography. Anesth Analg. 2007;104:308-311. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 16] [Cited by in RCA: 18] [Article Influence: 0.9] [Reference Citation Analysis (0)] |
| 24. | Frischenschlager O, Pucher I. Psychological management of pain. Disabil Rehabil. 2002;24:416-422. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 28] [Cited by in RCA: 26] [Article Influence: 1.1] [Reference Citation Analysis (0)] |
| 25. | Liu Q, Zhang YQ, Yang ZL, Zhang XQ. [Transcutaneous electrical acupoint stimulation combined with ondansetron in preventing nausea and vomiting after modified radical mastectomy: a report of 40 cases]. Yixue Daobao. 38:747-750. [DOI] [Full Text] |
| 26. | Li H, Wen Q, Lu L, Hu H, He Y, Zhou Y, Wu X, Li N. Transcutaneous electrical acupoint stimulation combined with electroacupuncture for rapid recovery of patients after laparotomy for gastrointestinal surgery: a study protocol for a randomised controlled trial. BMJ Open. 2021;11:e053309. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 2] [Cited by in RCA: 9] [Article Influence: 1.8] [Reference Citation Analysis (0)] |