
















Copyright: ©Author(s) 2026.
World J Gastroenterol. Jan 21, 2027; 33(3): 124434
Published online Jan 21, 2027. doi: 10.3748/wjg.124434
Published online Jan 21, 2027. doi: 10.3748/wjg.124434
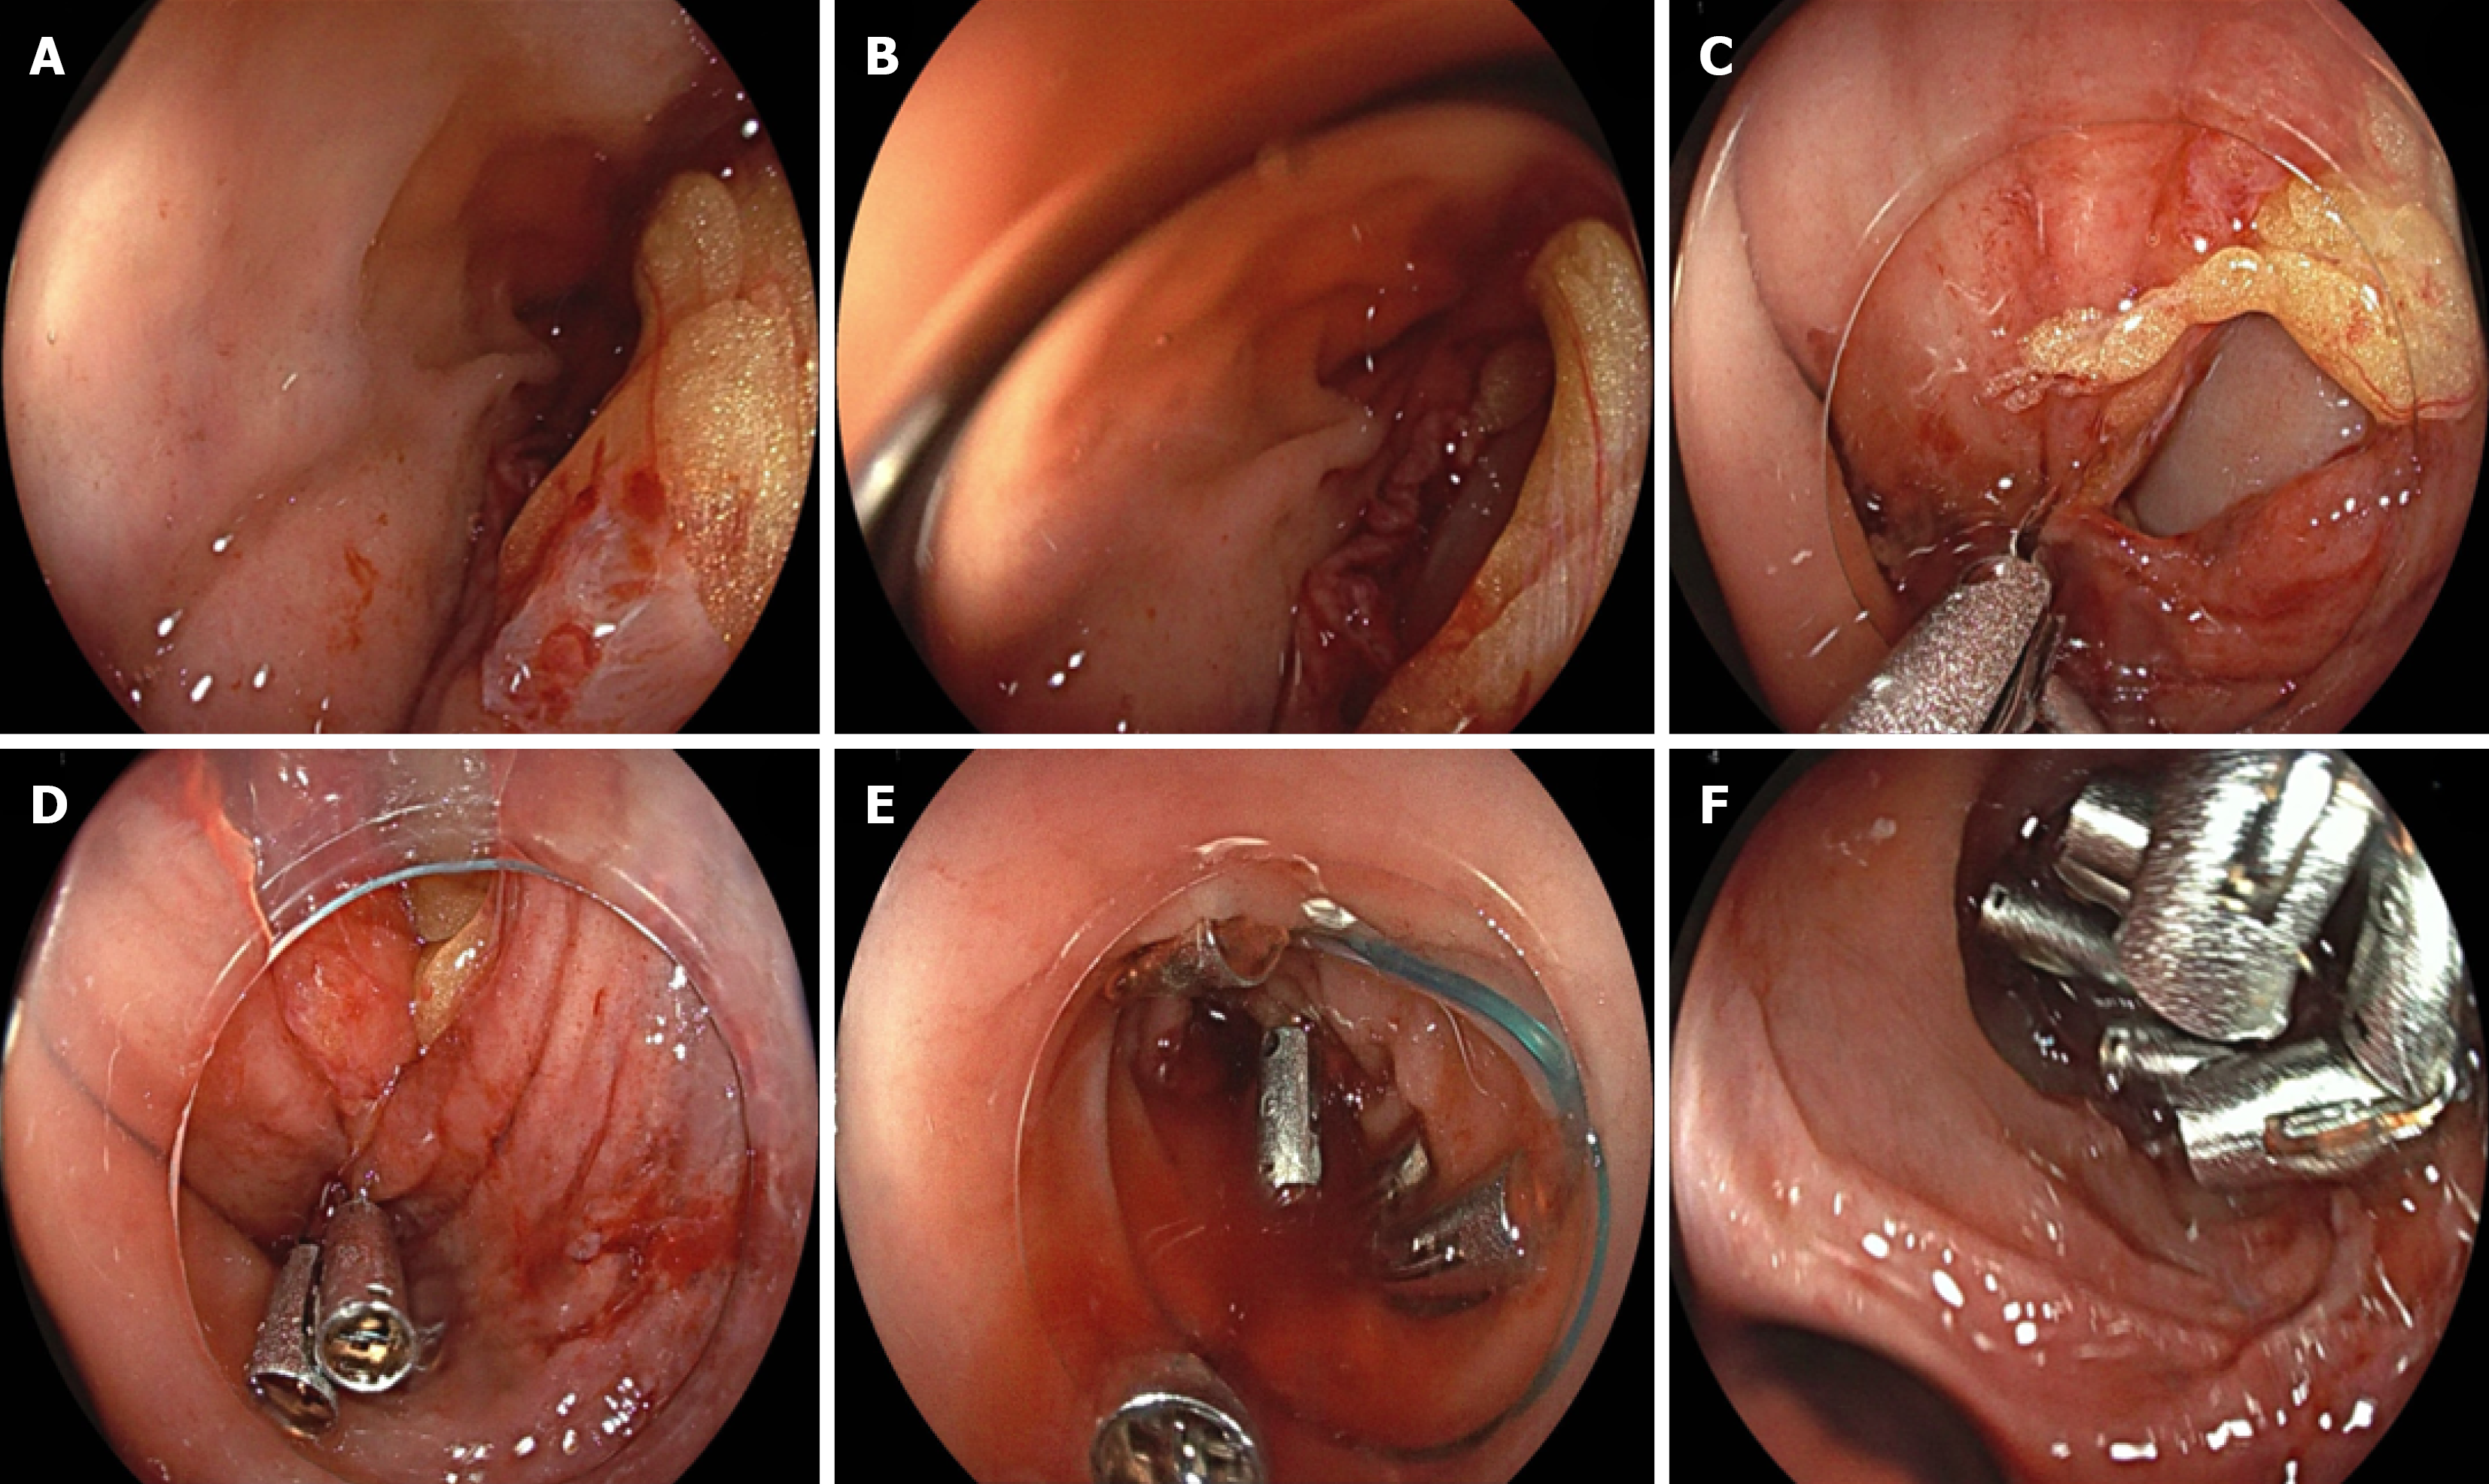
Figure 1 Endoscopic management of a proximal sigmoid colon perforation.
A-D: A longitudinal full-thickness laceration, extending beyond the endoscopic field of view and measuring approximately 5 cm × 4 cm, with serosal and mesenteric oozing and exposed intraabdominal viscera; C and D: Initial closure of the defect edges using through-the-scope clips to reduce the perforation size; E: A nylon loop was introduced and anchored to the defect margins with through-the-scope clip assistance; F: Gradual cinching of the nylon loop achieved complete purse-string closure.
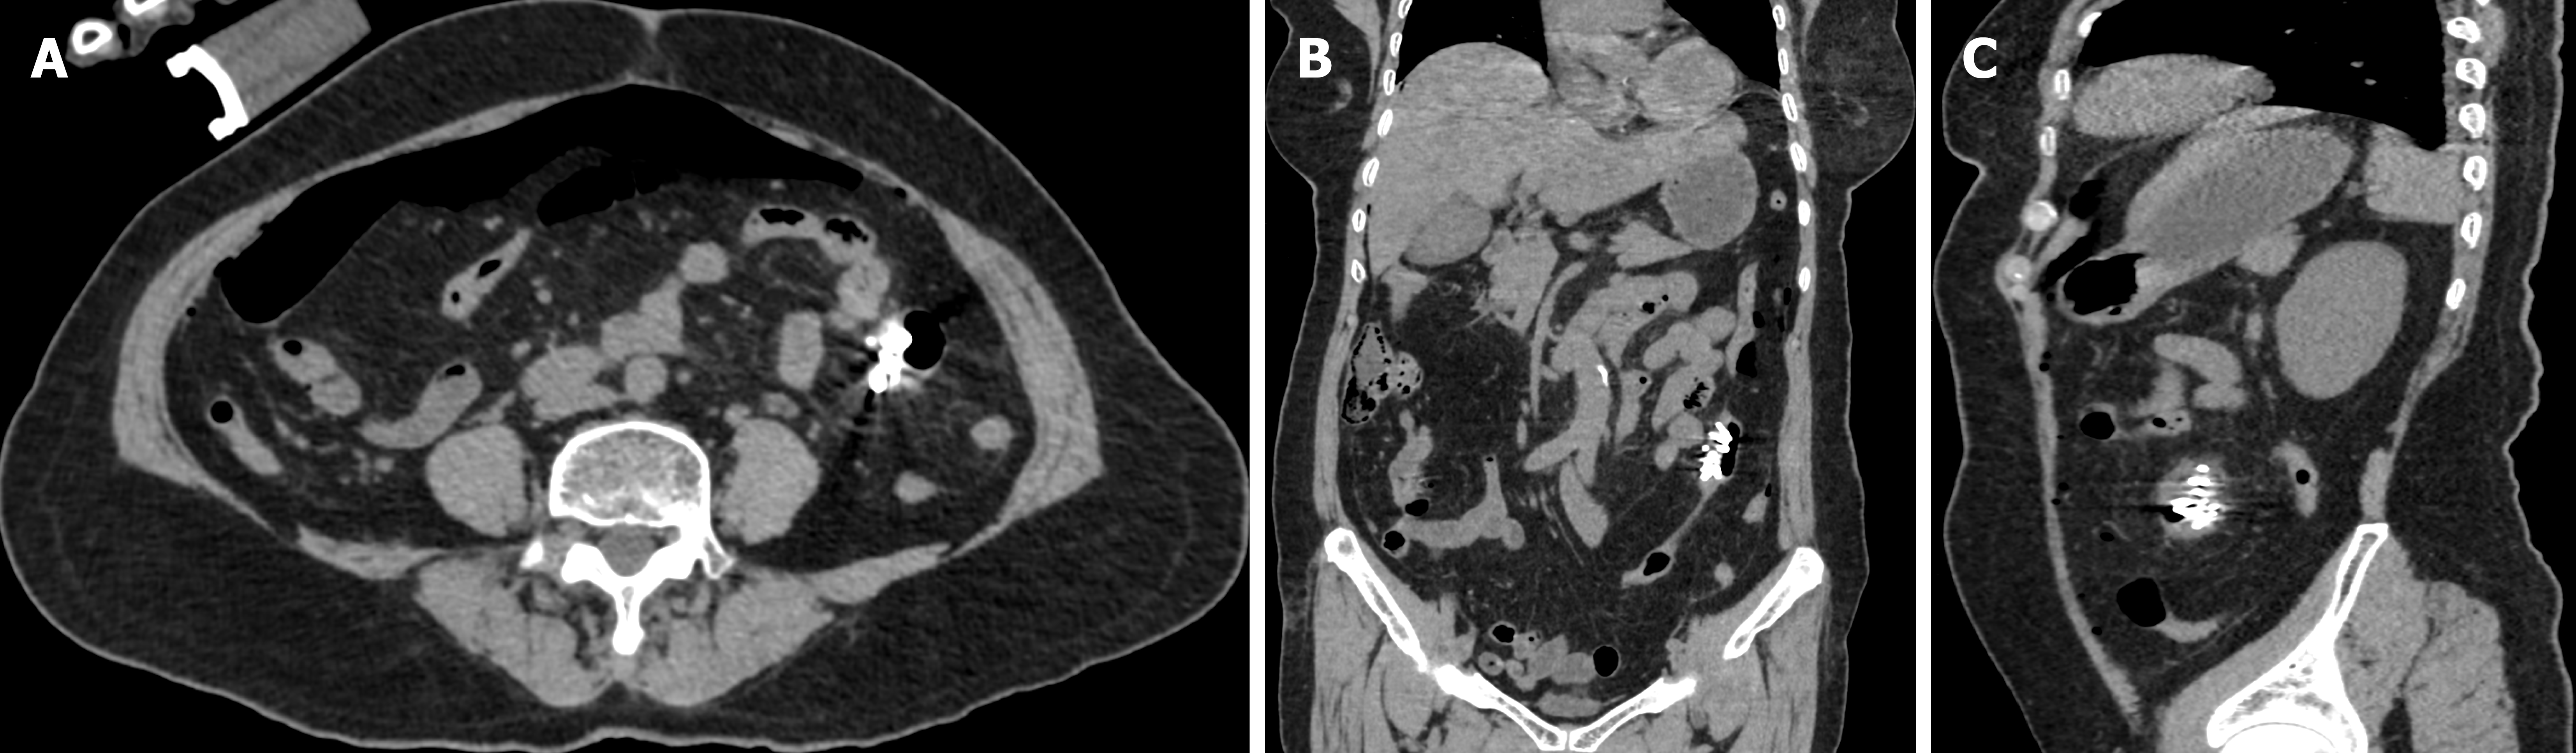
Figure 2 Abdominal computed tomography on postoperative day 1.
A-C: Axial, coronal, and sagittal views demonstrate multiple metallic clips in the upper sigmoid colon, with localized wall thickening, pericolonic fat stranding, and mild luminal narrowing. Small amounts of free air are present beneath the diaphragm, adjacent to the transverse colon, and within the left paracolic gutter.
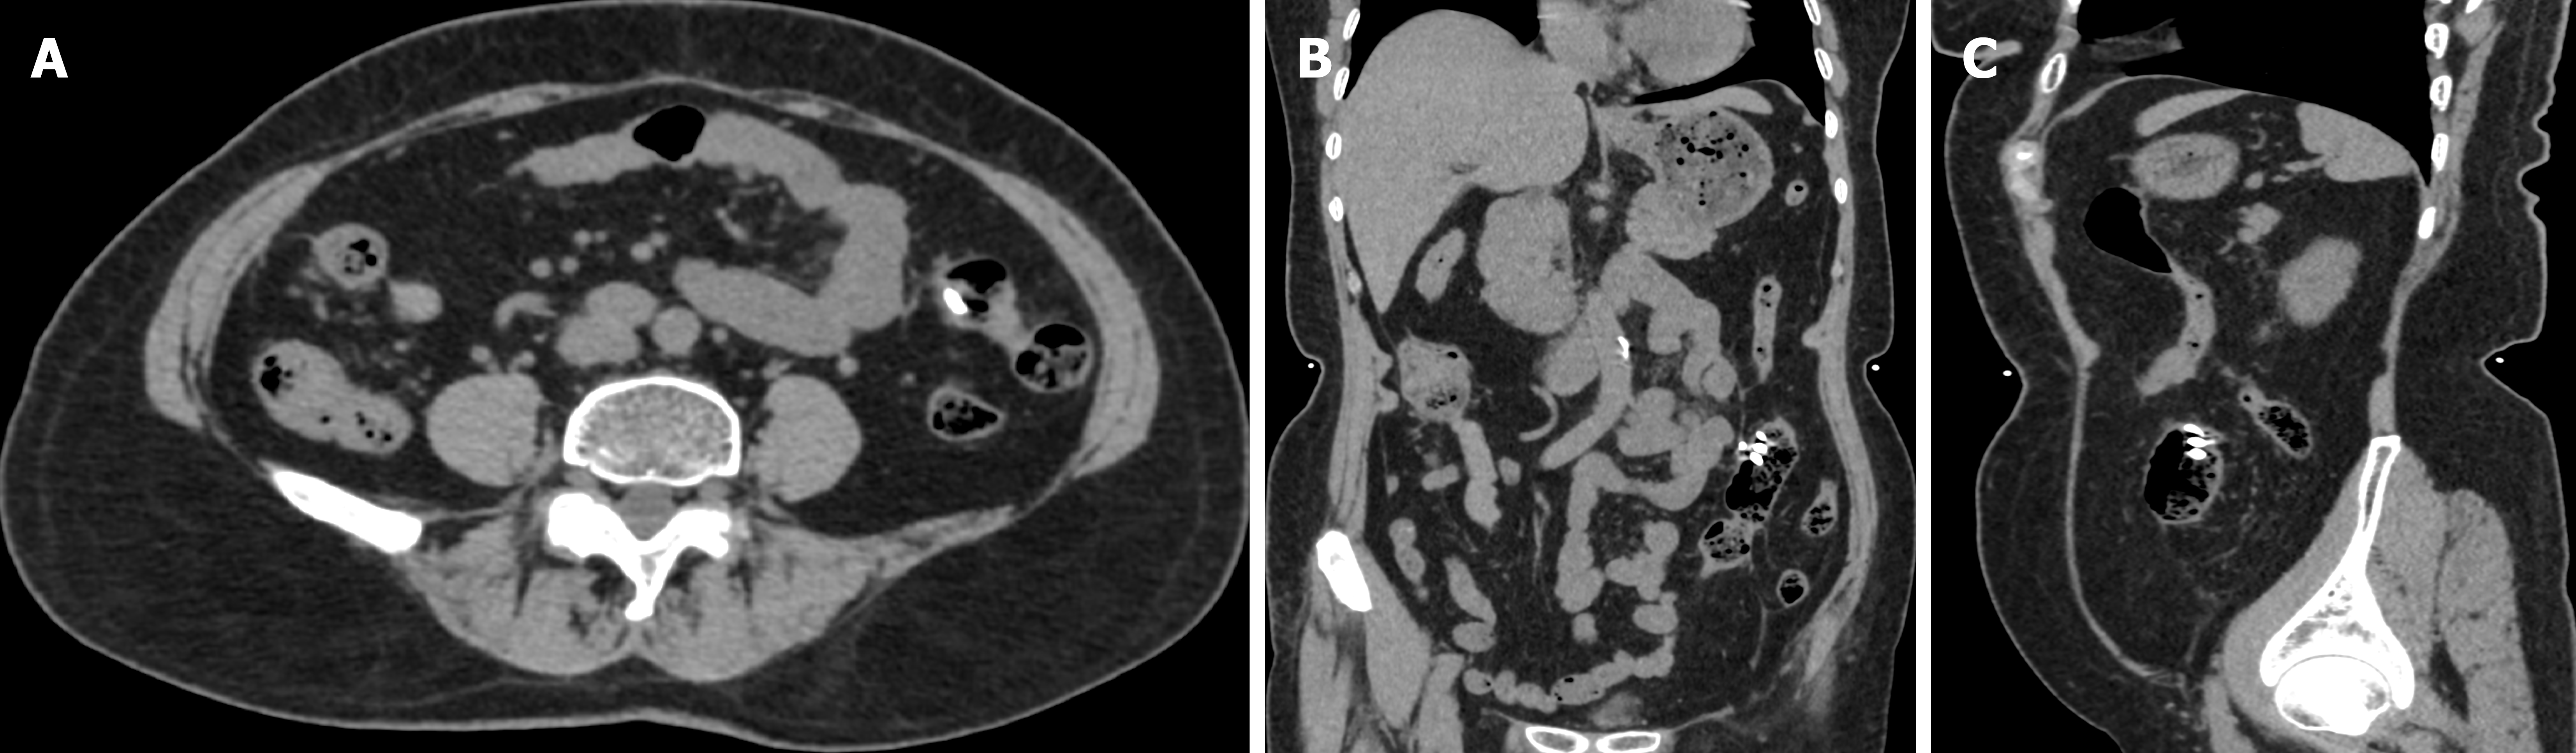
Figure 3 Abdominal computed tomography on postoperative day 35.
A-C: Axial, coronal, and sagittal views demonstrate several metallic clips at the repair site in the upper sigmoid colon, with mild localized wall thickening and intact serosa but no significant luminal narrowing; the pericolonic fat appears clear. Compared with the computed tomography obtained on postoperative day 1, fewer metallic clips are present, wall thickening and pericolonic fat stranding have markedly improved, the lumen remains patent, and the previously noted free air has completely resolved.
- Citation: Zeng X, Gong FR, Li Q, Shi YB, Lin F. Endoscopic closure of a giant iatrogenic sigmoid perforation using through-the-scope clips and a nylon loop: A case report. World J Gastroenterol 2027; 33(3): 124434
- URL: https://www.wjgnet.com/1007-9327/full/v33/i3/124434.htm
- DOI: https://dx.doi.org/10.3748/wjg.124434