
















Published online Sep 20, 2026. doi: 10.5493/wjem.120424
Revised: March 6, 2026
Accepted: June 11, 2026
Published online: September 20, 2026
Processing time: 205 Days and 22 Hours
Pulmonary tuberculosis (TB) remains a significant global health burden, with disease severity determined by the complex interplay between pathogen burden and host immune responses. Mycobacterial load and serum transforming growth factor-beta (TGF-β) are parameters potentially associated with disease progression and pulmonary tissue damage. TGF-β, as an immunoregulatory cytokine, plays a dual role in TB pathogenesis by suppressing protective immunity while contributing to fibrotic tissue remodeling. Despite their clinical relevance, the direct correlation between bacterial load, serum TGF-β, and radiological lesion extent in newly diagnosed patients remains insufficiently clarified in high-burden clinical settings.
To analyze the correlation between bacterial load, serum TGF-β, and radiological lesion extent in newly diagnosed pulmonary TB patients.
This observational study employed a cross-sectional design involving 60 newly diagnosed pulmonary TB patients at Haji Regional General Hospital, Makassar. Laboratory examinations were conducted at the Hasanuddin University Medical Research Laboratory, Faculty of Medicine. Bacterial load was assessed using semi-quantitative categories of the Xpert MTB/RIF rapid molecular test, serum TGF-β levels were measured using the enzyme-linked immunosorbent assay, and radiological lesion extent was classified based on chest radiography into minimal vs moderate-extensive categories. Bivariate statistical tests were performed for analysis.
A total of 60 newly diagnosed pulmonary TB patients were enrolled, with the majority being male (44 patients, 73.3%) and 16 female patients (26.7%). In terms of age, 70.0% were below 60 years and 30.0% were 60 years or older. Based on body mass index, 41.7% were underweight, 51.7% normal weight, and 6.7% overweight. Moderate-extensive lesions were observed in 85.0% of patients, while 56.7% had medium-high bacterial load. A statistically significant association was found between bacterial load and lesion extent (P = 0.032), with the medium-high group demonstrating a markedly higher risk of moderate-extensive lesions (odds ratio = 5.895; 95% confidence interval: 1.109-31.340). No significant associations were identified between serum TGF-β levels and lesion extent (P = 0.676) or bacterial load (P = 0.622).
High bacterial load predicts severe radiological lung damage in TB, but systemic TGF-β does not reflect disease extent, suggesting localized activity and need for further tissue-level investigation.
Core Tip: Pulmonary tuberculosis (TB) severity is shaped by the interplay between bacterial burden and host immune responses. This study examined their association with radiological lesion extent in newly diagnosed patients. Bacterial load was significantly associated with moderate-extensive lung damage, whereas systemic transforming growth factor-β levels did not reflect disease severity, suggesting a more localized immune role in TB pathogenesis.
- Citation: Kandi PN, Iskandar MH, Putrawan HA, Mubin RH, Bakri S, Kasim H, Alimuddin S, Rusman RD, Seweng A. Bacterial load and transforming growth factor-beta: Predicting the extent of lung damage in pulmonary tuberculosis patients. World J Exp Med 2026; 16(3): 120424
- URL: https://www.wjgnet.com/2220-315x/full/v16/i3/120424.htm
- DOI: https://dx.doi.org/10.5493/wjem.120424
Tuberculosis (TB) remains one of the most formidable global public health challenges of our time. According to the latest data from the World Health Organization (WHO) (2025), an estimated 10.8 million people fell ill with TB and the global total of deaths from the disease in 2024 was 1.23 million. The burden of TB is profoundly uneven, just eight countries account for two-thirds of all global cases, with India (25%), Indonesia (10%), the Philippines (6.8%), and China (6.5%) bearing the largest shares. This global context underscores the persistent and inequitable nature of the TB epidemic[1,2].
Indonesia ranks second globally as the country with the highest number of TB cases, with an estimated 867391 new cases in 2025. In South Sulawesi Province, a total of 29559 TB cases were reported in 2025. Among them, the city of Makassar accounted for the largest share, contributing 9877 newly detected cases[3]. However, suboptimal coverage of diagnosis and treatment led to delays in clinical management, which ultimately resulted in structural pulmonary complications such as cavitation and fibrosis. Studies in Makassar have shown that the incidence of fibrosis among post-TB patients can reach 78.2%, with 37.4% experiencing impaired lung function[4].
MTB is the organism that causes TB, which primarily and most frequently affects the lungs. Individuals with pulmo
Dendritic cells then migrate to the lymph nodes, secreting interleukin (IL)-12, attracting T lymphocytes, and activating the maturation of T-helper 1 (Th1) cells. At the same time, alveolar macrophages are destroyed by MTB and recruit other inflammatory cells such as neutrophils. Th1 activation triggers the production of interferon-γ and subsequent macro
One cytokine considered to have a crucial role in the immune response to TB infection is TGF-β. As a pleiotropic cytokine, TGF-β has complex dual functions: On one hand, it limits excessive inflammation and promotes fibrosis or tissue repair, while on the other hand, it may exert immunosuppressive effects that facilitate bacterial persistence within macrophages. Although its role in granuloma formation and fibrosis has been extensively studied in vitro, the correlation between systemic TGF-β levels and bacterial burden or the extent of radiological lesions in human TB patients has yielded conflicting results across different studies[8,9]. Radiological manifestations in pulmonary TB patients vary widely, ranging from minimal lesions to extensive tissue destruction (moderate-extensive). The extent of these radiological lesions is frequently regarded as a reflection of disease severity and the underlying bacterial burden within the patient[10,11].
Research by Christine et al[12] indicates that TGF-β levels are significantly higher in TB patients with pulmonary fibrosis. The results show an increase in the average TGF-β level in patients with extensive lung lesions compared to TGF-β levels in patients with minimal lung lesions among post-TB patients. Another study by Seyedhosseini et al[13] found that plasma or serum levels of IL-6, IL-17, and TGF-β were significantly higher in patients newly diagnosed with active TB compared to a healthy control group.
Bacterial load assessed semi-quantitatively using the rapid molecular test (RMT) has become a new standard for the rapid diagnosis of TB. In addition to detecting the presence of M. tuberculosis and rifampicin resistance, the RMT provides information on bacillary density, which is theoretically associated with infectivity and the degree of tissue damage. However, in clinical practice, the relationship between bacterial load detected in sputum and the anatomical extent of pulmonary damage observed on chest radiographs often shows inconsistencies. This observation suggests that host immunopathological mechanisms play a substantial role in determining disease progression[14,15].
To this point, conducting this research in Makassar is crucial given its status as the largest contributor to TB cases in South Sulawesi. Despite this substantial burden, clinical evidence exploring relationships between advanced diagnostic parameters including bacterial burden and cytokine profile and disease severity in this population remains limited. Current understanding of whether circulating TGF-β can serve as a reliable biomarker for assessing disease severity or pathogen burden is still insufficient. The majority of existing literature addresses isolated aspects of the disease process, lacking comprehensive evaluation of the interaction between pathogen burden measured through rapid molecular diagnostics and cytokine responses in relation to radiological outcomes. Accordingly, this study seeks to determine the degree to which bacterial load and serum TGF-β levels affect radiological lesion extent in newly diagnosed pulmonary TB patients. These findings are expected to contribute essential local evidence supporting targeted clinical interventions and informing public health strategies across this and comparable high-burden regions throughout Indonesia. A deeper understanding of this interaction may ultimately facilitate identification of more precise parameters for predicting disease severity and patient prognosis in routine healthcare settings.
We hypothesized that higher bacterial load, as quantified by semi-quantitative RMT results, would be significantly associated with more extensive radiological lesions, and that elevated serum TGF-β levels would correlate with both greater bacterial burden and more severe pulmonary involvement.
This study was conducted at Haji Regional General Hospital, Makassar and Hasanuddin University Medical Research Center Laboratory, Faculty of Medicine in Makassar, South Sulawesi. Ethical clearance was obtained from the relevant Health Research Ethics Committee, and all participants provided informed consent prior to data collection. This research was conducted over six months (June 2025 to December 2025).
This study included 60 newly diagnosed pulmonary TB patients. The minimum sample size was estimated using a single-proportion formula:
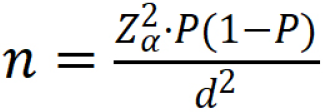
Where Zα = 1.96 [95% confidence interval (CI) level], P = 0.60 (expected proportion of moderate-extensive lesions based on prior literature), and d = 0.15 (margin of error). Substituting these values:
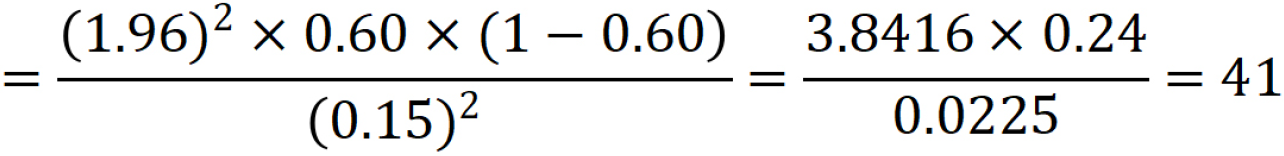
The minimum required sample was 41 subjects. To account for potential incomplete data and to strengthen the reliability of bivariate analyses (including χ2 and Spearman correlation tests), the total sample was increased to 60 patients. This sample size is also consistent with previous similar studies on TB biomarkers in Indonesia, which typically range from 45 subjects to 65 subjects, and is considered adequate for an exploratory cross-sectional study in a single-center setting.
Primary data were collected from patient interviews (anamnesis), physical examination, sputum examination, blood sample collection, and chest X-ray evaluation with signed informed consent. Participants were selected based on clearly defined inclusion and exclusion criteria to ensure sample homogeneity and data integrity. Patients were eligible for inclusion if they were newly diagnosed with pulmonary TB, aged over 18 years, bacteriologically confirmed through RMT, and willing to participate by providing signed informed consent. Conversely, patients were excluded from the study if they presented with comorbid conditions known to interfere with cytokine profiles, specifically human immunodeficiency virus infection, uncontrolled diabetes mellitus, or other immunodeficiency disorders. Patients with incomplete clinical or laboratory data were likewise excluded to maintain the reliability of the analysis.
Body mass index (BMI) was calculated by dividing each patient's body weight in kilograms by the square of their height in meters (kg/m²), and was subsequently categorized according to the WHO classification into underweight (less than 18.5 kg/m²), normal weight (18.5-24.9 kg/m²), overweight (25.0-29.9 kg/m²), and obese (30.0 kg/m² or above). The severity of lung involvement was assessed through postero-anterior chest radiographs, with lesion extent categorized into Minimal and Moderate-Extensive classifications by experienced radiologists. Bacterial load was determined semi-quantitatively using the Xpert MTB/RIF platform, with results dichotomized into low and medium-high categories for statistical robustness. To evaluate the systemic immune response, venous blood samples were collected from each subject before the initiation of anti-TB therapy. Serum TGF-β levels were measured using a sandwich enzyme-linked immu
Statistical processing was performed using SPSS v25. Demographic and clinical characteristics were summarized using descriptive statistics, including n (%). Bivariate associations between TGF-β levels, RMT results, and radiological lesion extent were analyzed using the χ2 test. Correlation between serum TGF-β levels and bacterial load was assessed using the Spearman rank correlation test, given the ordinal and non-parametric nature of both variables. Odds ratio (OR) with 95%CI was calculated to estimate the magnitude of risk. Binary logistic regression was additionally performed to obtain confounder-adjusted estimates. Sex, age, and BMI category were included as covariates based on their biological plausibility as potential confounders of the association between bacterial load and radiological lesion extent. Statistical significance was defined at a P value of less than 0.05 (P < 0.05).
Of all patients presenting with pulmonary TB symptoms during the study period, those who met all inclusion criteria and provided informed consent were enrolled. Patients were excluded if they had comorbid immunosuppressive conditions or incomplete data. A total of 60 patients were confirmed eligible and included in the final analysis (Figure 1).

A total of 60 newly diagnosed pulmonary TB patients were enrolled in this study. The majority of subjects were male, accounting for 73.3% of the sample, while female patients comprised 26.7%. In terms of age distribution, 70.0% of patients were younger than 60 years and the remaining 30.0% were aged 60 years or older. Nutritional status assessment based on BMI revealed that a substantial proportion of the cohort (41.7%) were classified as underweight. The distribution of serum TGF-β levels was relatively balanced across the three tertiles, with tertile 1 comprised 33.3%, tertile 2 comprised 33.3%, and tertile 3 comprised 33.0% of the subjects. Regarding RMT, more than half of the participants (56.7%) had medium-high bacterial load results, while the remaining 43.3% had low bacterial load results. Radiological evaluation demonstrated that the vast majority of subjects (85.0%) presented with moderate-to-extensive lung lesions, whereas only 15.0% showed minimal radiological changes at the time of diagnosis as shown in Table 1.
| Variable | n (%) | |
| Sex | Female | 16 (26.7) |
| Male | 44 (73.3) | |
| Age | < 60 years | 42 (70.0) |
| ≥ 60 years | 18 (30.0) | |
| Body mass index | Underweight | 25 (41.7) |
| Normal | 31 (51.7) | |
| Overweight | 4 (6.7) | |
| TGF-β tertile | Tertile 1 | 20 (33.3) |
| Tertile 2 | 20 (33.3) | |
| Tertile 3 | 20 (33.3) | |
| Rapid moleculer test | Low | 26 (43.3) |
| Medium-high | 34 (56.7) | |
| Extent of lung lesion | Minimal | 9 (15.0) |
| Moderate-extensive | 51 (85.0) |
Statistical analysis demonstrated a significant correlation between the bacterial load, quantified via RMT, and the extent of lung lesions (P = 0.032). Among 34 patients with medium-high bacterial load, 32 patients (53.3%) presented with moderate-extensive lesions, while only 2 patients (3.3%) had minimal lesions. In contrast, among 26 patients with low bacterial load, 19 patients (31.7%) had moderate-extensive lesions and 7 patients (11.7%) had minimal lesions. Patients in the medium-high bacterial load category demonstrated a markedly elevated risk of moderate-extensive pulmonary damage compared to those with low bacterial load, with an OR of 5.895 (95%CI: 1.109-31.340), indicating that patients with medium-high bacterial load were nearly six times more likely to present with moderate-extensive radiological lesions as shown in Table 2. These findings underscore the substantial role of pathogen burden in determining the severity of pulmonary tissue destruction in newly diagnosed pulmonary TB patients.
| RMT | Extent of lung lesion | P value | Unajdusted OR (95%CI) | Adjusted OR (95%CI) | |
| Minimal | Moderate-extensive | ||||
| Medium-high | 2 (3.3) | 32 (53.3) | 0.032 | 5.895 (1.109-31.340) | 5.792 (1.691-10.583) |
| Low | 7 (11.7) | 19 (31.7) | |||
| Total | 9 (15) | 51 (85) | |||
To further evaluate whether the association between bacterial load and radiological lesion extent was independent of potential confounding variables, binary logistic regression was performed adjusting for sex, age, and BMI category. After adjustment, the association remained statistically significant, with an adjusted odds ratio of 5.792 (95%CI: 1.691–10.583), indicating that medium-high bacterial load is an independent predictor of moderate-extensive radiological lesions beyond the influence of demographic and nutritional factors. Notably, the adjusted estimate was consistent with the unadjusted OR of 5.895, suggesting minimal confounding effect of the included covariates on the primary association.
Statistical analysis revealed no significant correlation between TGF-β tertiles and lesion classification (P = 0.676). In tertile 1 (lowest TGF-β levels), 17 subjects (28.3%) had moderate-extensive lesions, while 3 subjects (5.0%) had minimal lesions. Tertile 2 demonstrated the highest proportion of moderate-extensive lesions, with 18 subjects (30.0%), and only 2 subjects (3.3%) presenting with minimal lesions. Interestingly, in tertile 3 (highest TGF-β levels), the number of subjects with moderate-extensive lesions slightly decreased to 16 (26.7%), while minimal lesions were observed in 4 subjects (6.7%). Despite minor variations across tertiles, moderate-extensive lesions overwhelmingly dominated the study population, accounting for 85.0% of all subjects as shown in Table 3. The consistent pattern across all tertile groups suggests that circulating serum TGF-β levels do not significantly reflect the degree of pulmonary tissue involvement at the time of initial diagnosis, implying that the immunomodulatory role of this cytokine may be more relevant at the local tissue level rather than in systemic circulation.
| TGF-β | Extent of lung lesion | P value | |
| Minimal | Moderate-extensive | ||
| Tertile 1 | 3 (5) | 17 (28.3) | 0.676 |
| Tertile 2 | 2 (3.3) | 18 (30) | |
| Tertile 3 | 4 (6.7) | 16 (26.7) | |
| Total | 9 (15) | 51 (85) | |
Statistical analysis showed no significant relationship between TGF-β tertiles and molecular bacterial load (P = 0.622). In tertile 1, representing the lowest TGF-β levels, 11 subjects (18.3%) were classified in the medium-high RMT category, while 9 subjects (15.0%) were in the low RMT category. Tertile 2 showed an equal distribution between low and medium-high RMT results, with 10 subjects (16.7%) in each category. In tertile 3, which represented the highest TGF-β levels, a higher number of subjects were observed in the medium-high RMT category (13 subjects; 21.7%) compared to the low category (7 subjects; 11.7%) as shown in Table 4. The relatively even distribution of TGF-β tertiles across both bacterial load categories suggests that the magnitude of mycobacterial burden does not appear to directly influence systemic TGF-β concentrations, further supporting the notion that the immunological activity of this cytokine in TB pathogenesis may be compartmentalized within the pulmonary microenvironment rather than reflected in peripheral blood measurement.
| Rapid molecular test | TGF-β | P value | ||
| Tertile 1 | Tertile 2 | Tertile 3 | ||
| Low | 9 (15) | 10 (16.7) | 7 (11.7) | 0.622 |
| Medium-high | 11 (18.3) | 10 (16.7) | 13 (21.7) | |
| Total | 20 (33.3) | 20 (33.3) | 20 (33.3) | |
This study demonstrates that molecular bacterial burden, as assessed by the semi-quantitative results of the RMT assay, is correlated with the extent of pulmonary radiological lesions in newly diagnosed pulmonary TB patients. Patients with medium to high bacterial load were significantly more likely to present with moderate to extensive lung lesions, underscoring the importance of bacillary replication intensity in driving parenchymal damage[16,17].
These findings support the concept that active bacterial proliferation is closely linked to ongoing inflammatory destruction of lung tissue, which is subsequently visualized as more extensive radiological abnormalities. The semi-quantitative output of the RMT assay, therefore, provides clinically meaningful information beyond pathogen detection. Its association with lesion extent suggests that molecular bacterial load may function as an early surrogate marker of disease aggressiveness. In resource-limited settings, where access to advanced imaging or comprehensive immunological profiling may be restricted, this feature of RMT could be leveraged for rapid risk stratification. Patients identified with medium-high bacterial loads at diagnosis may warrant closer clinical surveillance, earlier radiological reassessment, and heightened attention to potential complications during the course of treatment[18].
Analysis of specific radiological characteristics revealed that high bacterial load was significantly correlated with findings indicative of active disease and more severe structural damage. This finding is consistent with a previous study conducted by Ko et al[19], which demonstrated that active radiological findings such as consolidation, and particularly cavitation, are closely associated with positive microbiological results. This consistency suggests that high bacterial load detected by RMT directly reflects a more anatomically aggressive disease process. This is further supported by findings from Horne et al[20], who reported that RMT results not only reflect the presence of MTB, but also represent the intensity of the pathological process occurring within pulmonary tissue.
In contrast, the absence of a significant relationship between serum TGF-β levels and both radiological lesion extent and bacterial load underscores the limitations of using systemic immunological markers to reflect localized pulmonary pathology. Although TGF-β is widely recognized as a key regulator of immune suppression, granuloma stability, and fibrotic remodeling in TB, its biological activity is highly compartmentalized within lung tissue. As a result, circulating levels may fail to mirror the intensity or spatial distribution of immune responses occurring at the site of infection, particularly during the early and active phases of disease[5,9,21].
The findings of this study suggest that TGF-β is more likely to represent downstream immunoregulatory and re
A finding by Shaukat et al[23] reporting downregulation of TGF-β gene expression in peripheral blood mononuclear cells of early-stage active TB patients suggests that TGF-β regulation is dynamic and phase-dependent. In early active TB, as observed in our study population, the dominance of pro-inflammatory immune responses aimed at controlling acute infection may obscure the direct relationship between systemic TGF-β levels and bacterial burden or tissue damage visible on chest radiography. In other words, TGF-β may more accurately represent a marker of long-term consequences associated with repair and fibrosis in post-TB states, rather than serving as a direct indicator of the severity of active tissue damage at the time of diagnosis[24].
Taken together, these results emphasize that TB severity is best understood through an integrated framework that prioritizes direct indicators of pathogen activity while acknowledging the contextual and phase-dependent nature of host immune responses. Molecular quantification of bacterial burden, when interpreted alongside radiological findings, offers a more reliable and pragmatic approach to assessing disease severity than systemic cytokine measurements alone[25,26].
Several limitations of this study should be noted. First, TGF-β was measured in serum rather than at the pulmonary infection site, which may not reflect local cytokine activity within the granulomatous microenvironment. Second, the use of conventional chest radiography, as opposed to high-resolution computed tomography, may have limited the detection of subtle abnormalities such as early cavitation or minimal fibrotic changes, potentially affecting the accuracy of lesion severity classification. Third, although binary logistic regression adjusting for sex, age, and BMI category was performed, the limited number of subjects with minimal lesions (n = 9) constrains the stability of the multivariable model and results should therefore be interpreted with caution. Additionally, the TGF-β tertile boundaries were determined from the observed distribution within this study population rather than from pre-established clinical thresholds, which may limit the generalizability of these groupings and direct comparisons with future studies.
Despite these limitations, the findings offer preliminary insights into the relationship between bacterial burden and radiological severity in pulmonary TB. Further studies incorporating tissue-level immunological assessments and more advanced imaging modalities are warranted to validate and expand upon these results.
Future studies should consider incorporating tissue-level measurements of TGF-β, such as through bronchoalveolar lavage fluid, to better capture localized pulmonary immune activity that systemic serum measurements appear unable to reflect. Longitudinal studies tracking bacterial load and TGF-β throughout anti-TB treatment would further clarify the dynamic relationship between pathogen burden, cytokine regulation, and radiological outcomes over time. The inclusion of additional immune markers such as IL-10 and TNF-α may also allow for a more comprehensive characterization of host immune responses in relation to disease severity.
Clinically, early identification of patients with high bacterial burden through RMT may serve as a practical risk stratification tool, enabling closer radiological monitoring and more intensive follow-up for those at greatest risk of severe pulmonary damage. Multicenter studies across other high-burden regions of Indonesia are warranted to validate these findings and establish locally relevant thresholds for bacterial load as a predictor of disease severity.
In conclusion, the present study highlights molecular bacterial load as a robust determinant of radiological severity in pulmonary TB, while demonstrating that systemic TGF-β levels do not accurately reflect either bacillary density or lesion extent at diagnosis. These findings support a shift toward incorporating semi-quantitative molecular data into routine clinical assessment and prognostic evaluation.
We thank the staff and medical team at the Department of Pulmonology and Respiratory Medicine, Haji Regional General Hospital, Makassar, for their support and cooperation during the data collection process of this study.
| 1. | World Health Organization. Global Tuberculosis Report 2025. 2025. Available from: https://www.who.int/teams/global-programme-on-tuberculosis-and-lung-health/tb-reports/global-tuberculosis-report-2025/tb-disease-burden/1-1-tb-incidence. |
| 2. | Sasindran SJ, Torrelles JB. Mycobacterium Tuberculosis Infection and Inflammation: what is Beneficial for the Host and for the Bacterium? Front Microbiol. 2011;2:2. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 182] [Cited by in RCA: 192] [Article Influence: 12.8] [Reference Citation Analysis (0)] |
| 3. | Indonesia KKR. Capaian Notifikasi TB Tahun 2025 Per Provinsi. 2025. Available from: http://tbdashboard.sitb.id/dashboard_capaian_dashboard.php. |
| 4. | Putrawan HA, Idris I, Santoso A, Iskandar H, Muttaqin Z, Zaini J, Natzir R, Bahrun U, Tawali S. Evaluation of Small Mothers against Decapentaplegic 3 and Transforming Growth Factor Beta Levels in Relation to Lung Fibrosis and Function in Treated Pulmonary Tuberculosis Patients. Int J Mycobacteriol. 2025;14:239-245. [RCA] [PubMed] [DOI] [Full Text] [Cited by in RCA: 1] [Reference Citation Analysis (0)] |
| 5. | de Martino M, Lodi L, Galli L, Chiappini E. Immune Response to Mycobacterium tuberculosis: A Narrative Review. Front Pediatr. 2019;7:350. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 282] [Cited by in RCA: 227] [Article Influence: 32.4] [Reference Citation Analysis (0)] |
| 6. | Allwood BW, Byrne A, Meghji J, Rachow A, van der Zalm MM, Schoch OD. Post-Tuberculosis Lung Disease: Clinical Review of an Under-Recognised Global Challenge. Respiration. 2021;100:751-763. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 66] [Cited by in RCA: 169] [Article Influence: 33.8] [Reference Citation Analysis (0)] |
| 7. | Wahyuningrum WH, Indrati AR, Rachmayati S, Turbawaty DK. Uji Diagnostik Pemeriksaan Kadar Transforming Growth Factor Beta 1 Cairan Pleura pada Pleuritis Tuberkulosis. Majalah Kedokteran Bandung. 2017;49:259-266. [RCA] [DOI] [Full Text] [Cited by in RCA: 1] [Reference Citation Analysis (0)] |
| 8. | Astuti T, Chozin IN, Damayanti NS, Nugrahenny D. The levels of pro-fibrotic cytokines in pulmonary tuberculosis with minimal and extensive lesions. Lung India. 2018;35:204-208. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 2] [Cited by in RCA: 7] [Article Influence: 0.9] [Reference Citation Analysis (0)] |
| 9. | Fernandez IE, Eickelberg O. The impact of TGF-β on lung fibrosis: from targeting to biomarkers. Proc Am Thorac Soc. 2012;9:111-116. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 420] [Cited by in RCA: 580] [Article Influence: 41.4] [Reference Citation Analysis (1)] |
| 10. | Sulistiana R. Correlation between Chest X-Rays and TCM (Rapid Molecular Tests) in Pulmonary Tuberculosis Patients at Anutapura Hospital Palu under a Creative. J Edu Health. 2023;14:581-585. |
| 11. | Nel M, Franckling-Smith Z, Pillay T, Andronikou S, Zar HJ. Chest Imaging for Pulmonary TB-An Update. Pathogens. 2022;11:161. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 2] [Cited by in RCA: 19] [Article Influence: 4.8] [Reference Citation Analysis (0)] |
| 12. | Christine T, Tarigan AP, Ananda FR. The Correlation between Levels of Transforming Growth Factor-β with Pulmonary Fibrosis in Post Pulmonary Tuberculosis in Medan, North Sumatera - Indonesia. Open Access Maced J Med Sci. 2019;7:2075-2078. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 4] [Cited by in RCA: 9] [Article Influence: 1.3] [Reference Citation Analysis (0)] |
| 13. | Seyedhosseini FS, Mohammadi S, Zare Ebrahimabad M, Khodabakhshi B, Abbasi A, Yazdani Y. Interleukin-6, Interleukin-17 and Transforming Growth Factor-Beta are Overexpressed in Newly Diagnosed Tuberculosis Patients; Potent Biomarkers of Mycobacterial Infection. Arch Clin Infect Dis. 2019;14. [RCA] [DOI] [Full Text] [Cited by in Crossref: 5] [Cited by in RCA: 7] [Article Influence: 1.0] [Reference Citation Analysis (4)] |
| 14. | Craciun OM, Torres MDR, Llanes AB, Romay-Barja M. Tuberculosis Knowledge, Attitudes, and Practice in Middle- and Low-Income Countries: A Systematic Review. J Trop Med. 2023;2023:1014666. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in RCA: 29] [Reference Citation Analysis (0)] |
| 15. | Detjen AK, DiNardo AR, Leyden J, Steingart KR, Menzies D, Schiller I, Dendukuri N, Mandalakas AM. Xpert MTB/RIF assay for the diagnosis of pulmonary tuberculosis in children: a systematic review and meta-analysis. Lancet Respir Med. 2015;3:451-461. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 174] [Cited by in RCA: 244] [Article Influence: 22.2] [Reference Citation Analysis (0)] |
| 16. | Rachmi Merrina, Yanti B, Yunita Arliny. Correlation Between MTB/RIF Gene Xpert Cycle Threshold Values and Clinical Radiological Severity of Pulmonary Tuberculosis. Int J Trop Infect Dis. 2024;12:73-81. [DOI] [Full Text] |
| 17. | Pandey D, Yadav A. Efficacy of gene xpert over other diagnostic modalities of tuberculosis among children. Int J Contemp Pediatr. 2019;6:1545. [DOI] [Full Text] |
| 18. | Zhu XH, Tao NN, Zhang QY, Song WM, An QQ, Liu SQ, Li YF, Long F, Li HC. Association between diagnostic delay and prognosis of pulmonary tuberculosis in Shandong, China: a retrospective study. BMC Pulm Med. 2022;22:309. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in RCA: 10] [Reference Citation Analysis (0)] |
| 19. | Ko Y, Lee HY, Park YB, Hong SJ, Shin JH, Choi SJ, Kim C, Park SY, Jeong JY. Correlation of microbiological yield with radiographic activity on chest computed tomography in cases of suspected pulmonary tuberculosis. PLoS ONE. 2018;13:e0201748. [RCA] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 2] [Cited by in RCA: 6] [Article Influence: 0.8] [Reference Citation Analysis (0)] |
| 20. | Horne DJ, Kohli M, Zifodya JS, Schiller I, Dendukuri N, Tollefson D, Schumacher SG, Ochodo EA, Pai M, Steingart KR. Xpert MTB/RIF and Xpert MTB/RIF Ultra for pulmonary tuberculosis and rifampicin resistance in adults. Cochrane Database Syst Rev. 2019;6:CD009593. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 84] [Cited by in RCA: 139] [Article Influence: 19.9] [Reference Citation Analysis (0)] |
| 21. | Ruiz-Ortega M, Rodríguez-Vita J, Sanchez-Lopez E, Carvajal G, Egido J. TGF-beta signaling in vascular fibrosis. Cardiovasc Res. 2007;74:196-206. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 369] [Cited by in RCA: 411] [Article Influence: 21.6] [Reference Citation Analysis (0)] |
| 22. | Frangogiannis N. Transforming growth factor-β in tissue fibrosis. J Exp Med. 2020;217:e20190103. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 202] [Cited by in RCA: 1032] [Article Influence: 172.0] [Reference Citation Analysis (4)] |
| 23. | Shaukat SN, Eugenin E, Nasir F, Khanani R, Kazmi SU. Identification of immune biomarkers in recent active pulmonary tuberculosis. Sci Rep. 2023;13:11481. [RCA] [PubMed] [DOI] [Full Text] [Cited by in RCA: 20] [Reference Citation Analysis (0)] |
| 24. | Santoso A, Rasiha R, Zainal ATF, Khairunnisa IN, Fais MK, Gunawan AMAK. Transforming growth factor-β and matrix metalloproteinases as potential biomarkers of fibrotic lesions induced by tuberculosis: a systematic review and meta-analysis. BMJ Open. 2023;13:e070377. [RCA] [PubMed] [DOI] [Full Text] [Cited by in RCA: 7] [Reference Citation Analysis (0)] |
| 25. | van Crevel R, Ottenhoff TH, van der Meer JW. Innate immunity to Mycobacterium tuberculosis. Clin Microbiol Rev. 2002;15:294-309. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 399] [Cited by in RCA: 396] [Article Influence: 16.5] [Reference Citation Analysis (0)] |
| 26. | Tiwari D, Martineau AR. Inflammation-mediated tissue damage in pulmonary tuberculosis and host-directed therapeutic strategies. Semin Immunol. 2023;65:101672. [RCA] [PubMed] [DOI] [Full Text] [Cited by in RCA: 73] [Reference Citation Analysis (0)] |