
















Copyright: ©Author(s) 2026.
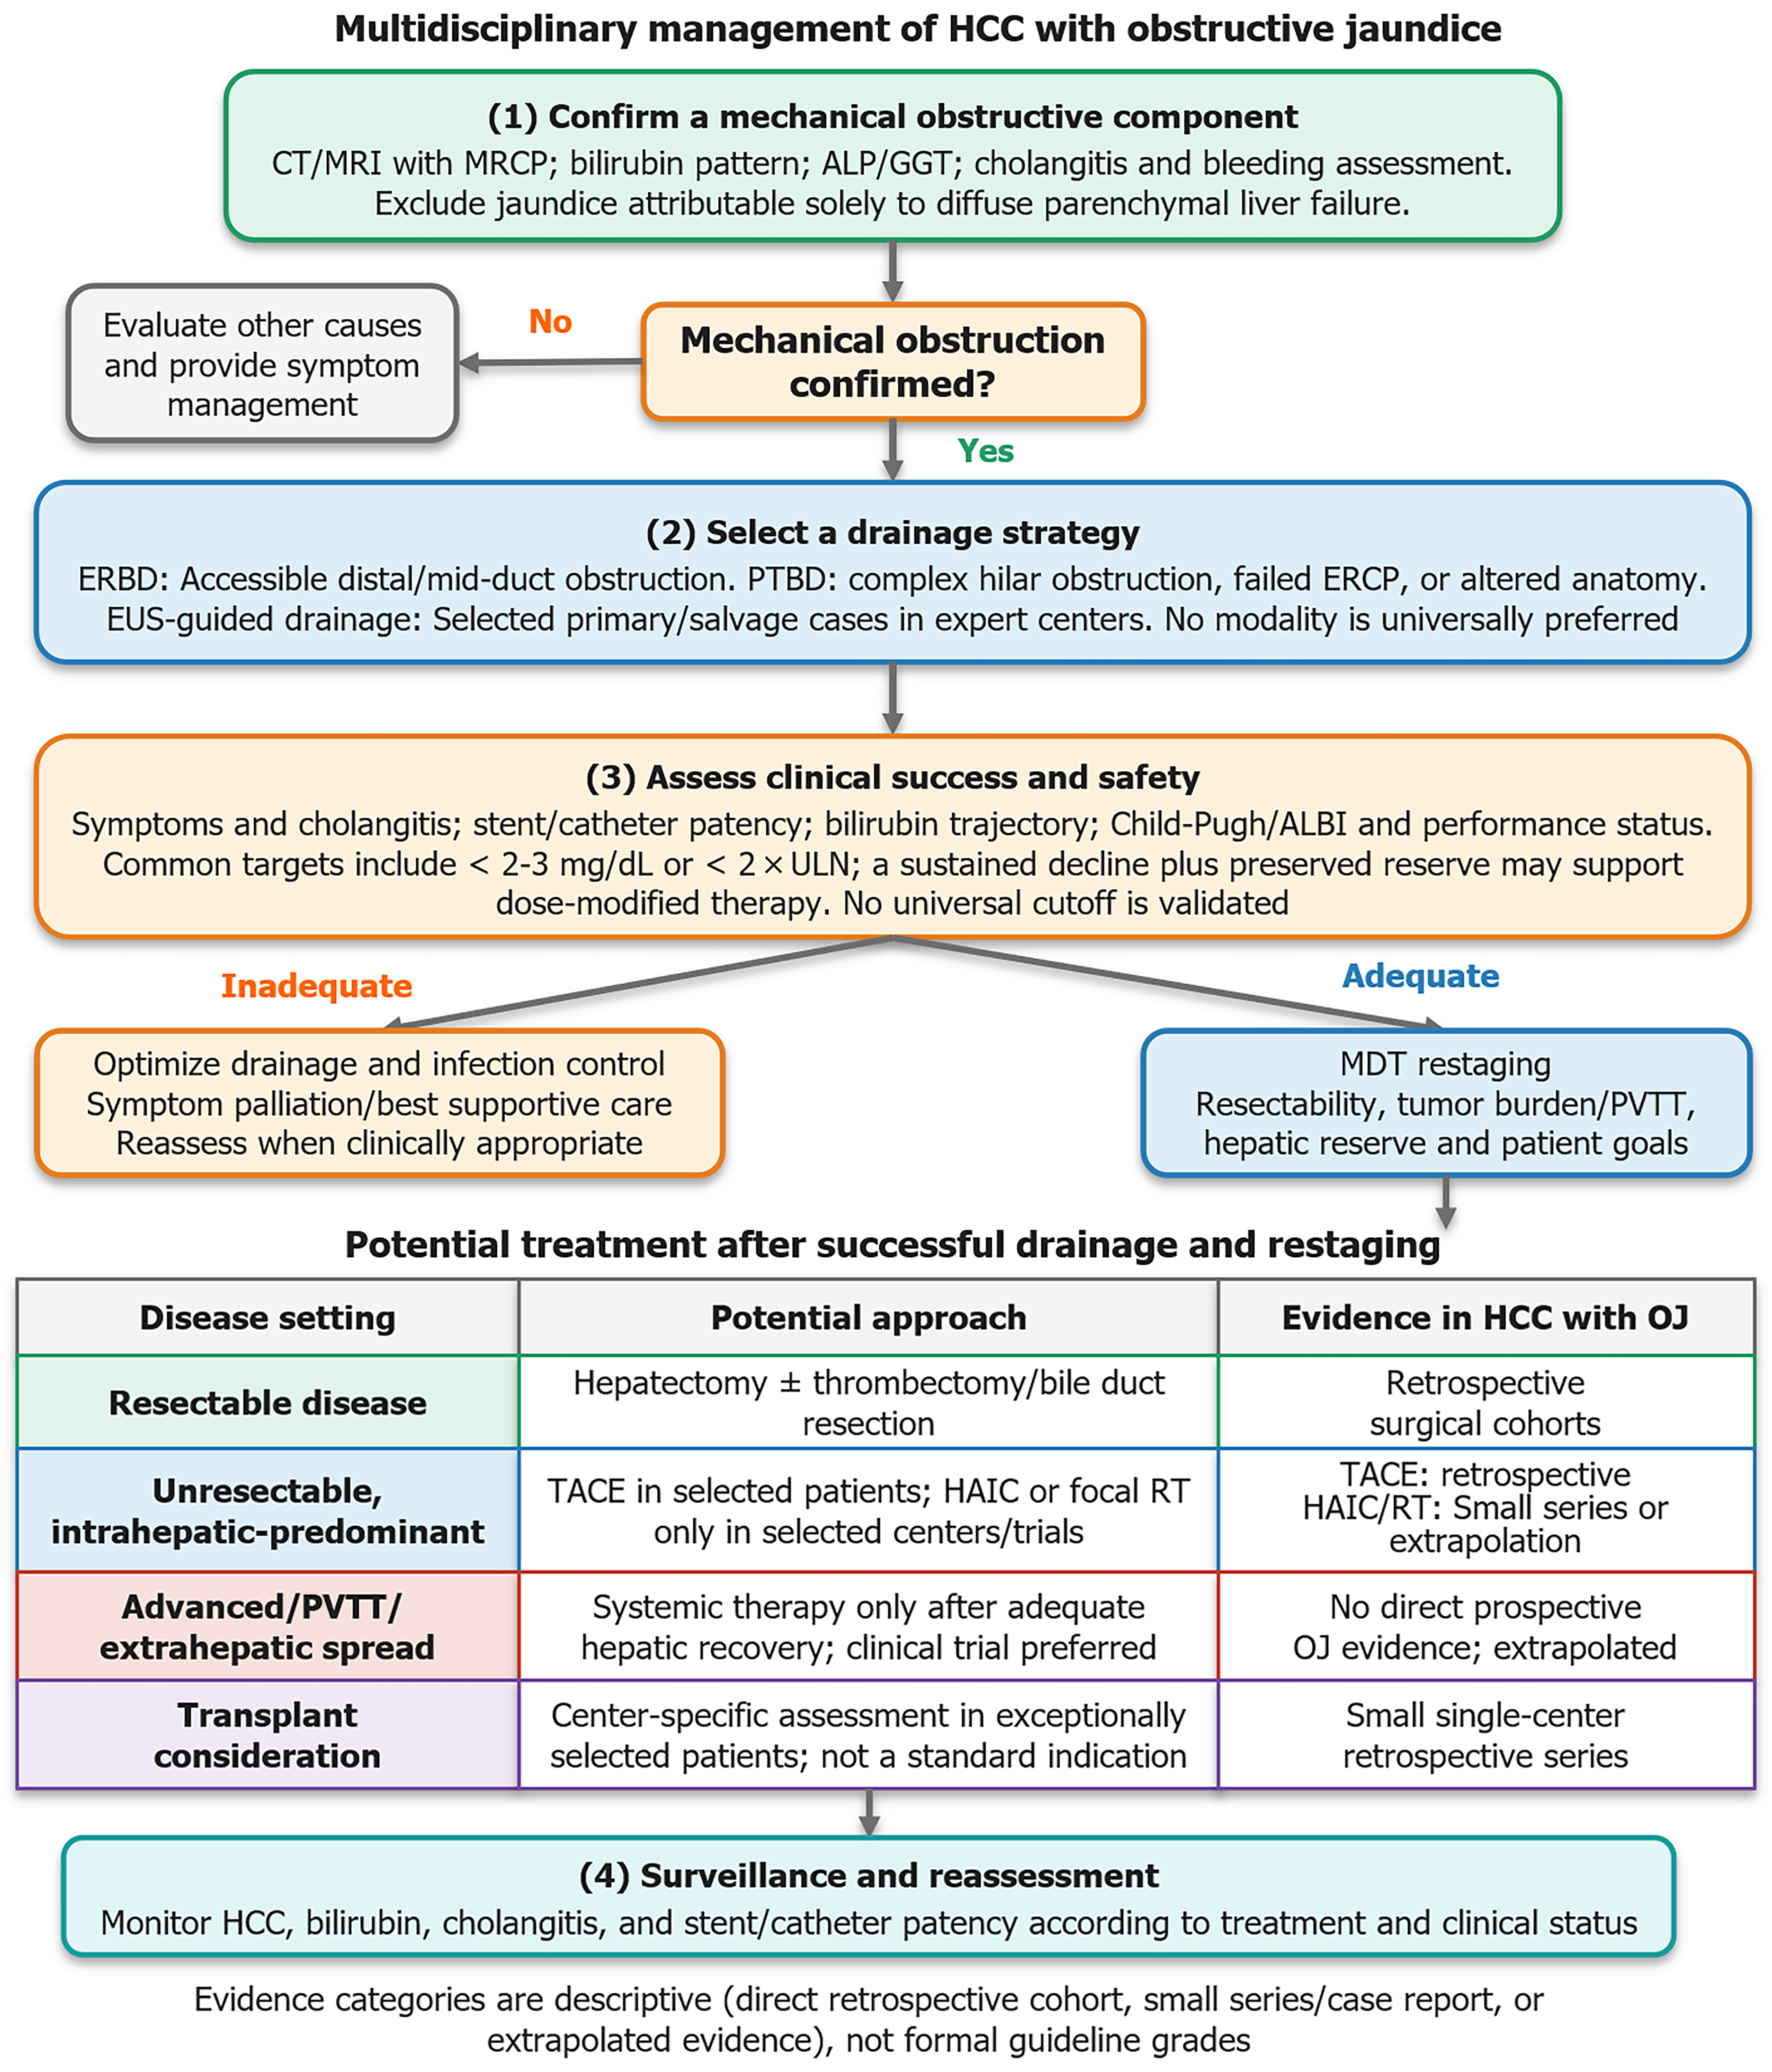
Figure 2 Evidence-calibrated multidisciplinary framework for hepatocellular carcinoma with obstructive jaundice.
Management begins by confirming a mechanical obstructive component and excluding jaundice caused solely by diffuse hepatic failure. Drainage modality is selected according to anatomy and expertise. Treatment after drainage depends on clinical response, hepatic reserve, tumor extent, and patient goals. Evidence labels are descriptive rather than formal guideline grades. HCC: Hepatocellular carcinoma; CT: Computed tomography; MRI: Magnetic resonance imaging; MRCP: Magnetic resonance cholangiopancreatography; ALP: Alkaline phosphatase; GGT: Gamma-glutamyl transferase; PTBD: Percutaneous transhepatic biliary drainage; ERBD: Endoscopic retrograde biliary drainage; ERCP: Endoscopic retrograde cholangiopancreatography; EUS: Endoscopic ultrasound; ALBI: Albumin-bilirubin; ULN: Upper limit of normal; MDT: Multidisciplinary team; PVTT: Portal vein tumor thrombus; OJ: Obstructive jaundice; TACE: Transarterial chemoembolization; HAIC: Hepatic arterial infusion chemotherapy; RT: Radiation therapy.
- Citation: Xiao P, Chen KX, Jiang LL, Zhang L. Hepatocellular carcinoma with obstructive jaundice: Biliary drainage and multimodal therapy. World J Hepatol 2026; 18(9): 124789
- URL: https://www.wjgnet.com/1948-5182/full/v18/i9/124789.htm
- DOI: https://dx.doi.org/10.4254/wjh.124789