
















Copyright: ©Author(s) 2026.
World J Gastroenterol. Dec 21, 2026; 32(47): 122272
Published online Dec 21, 2026. doi: 10.3748/wjg.122272
Published online Dec 21, 2026. doi: 10.3748/wjg.122272
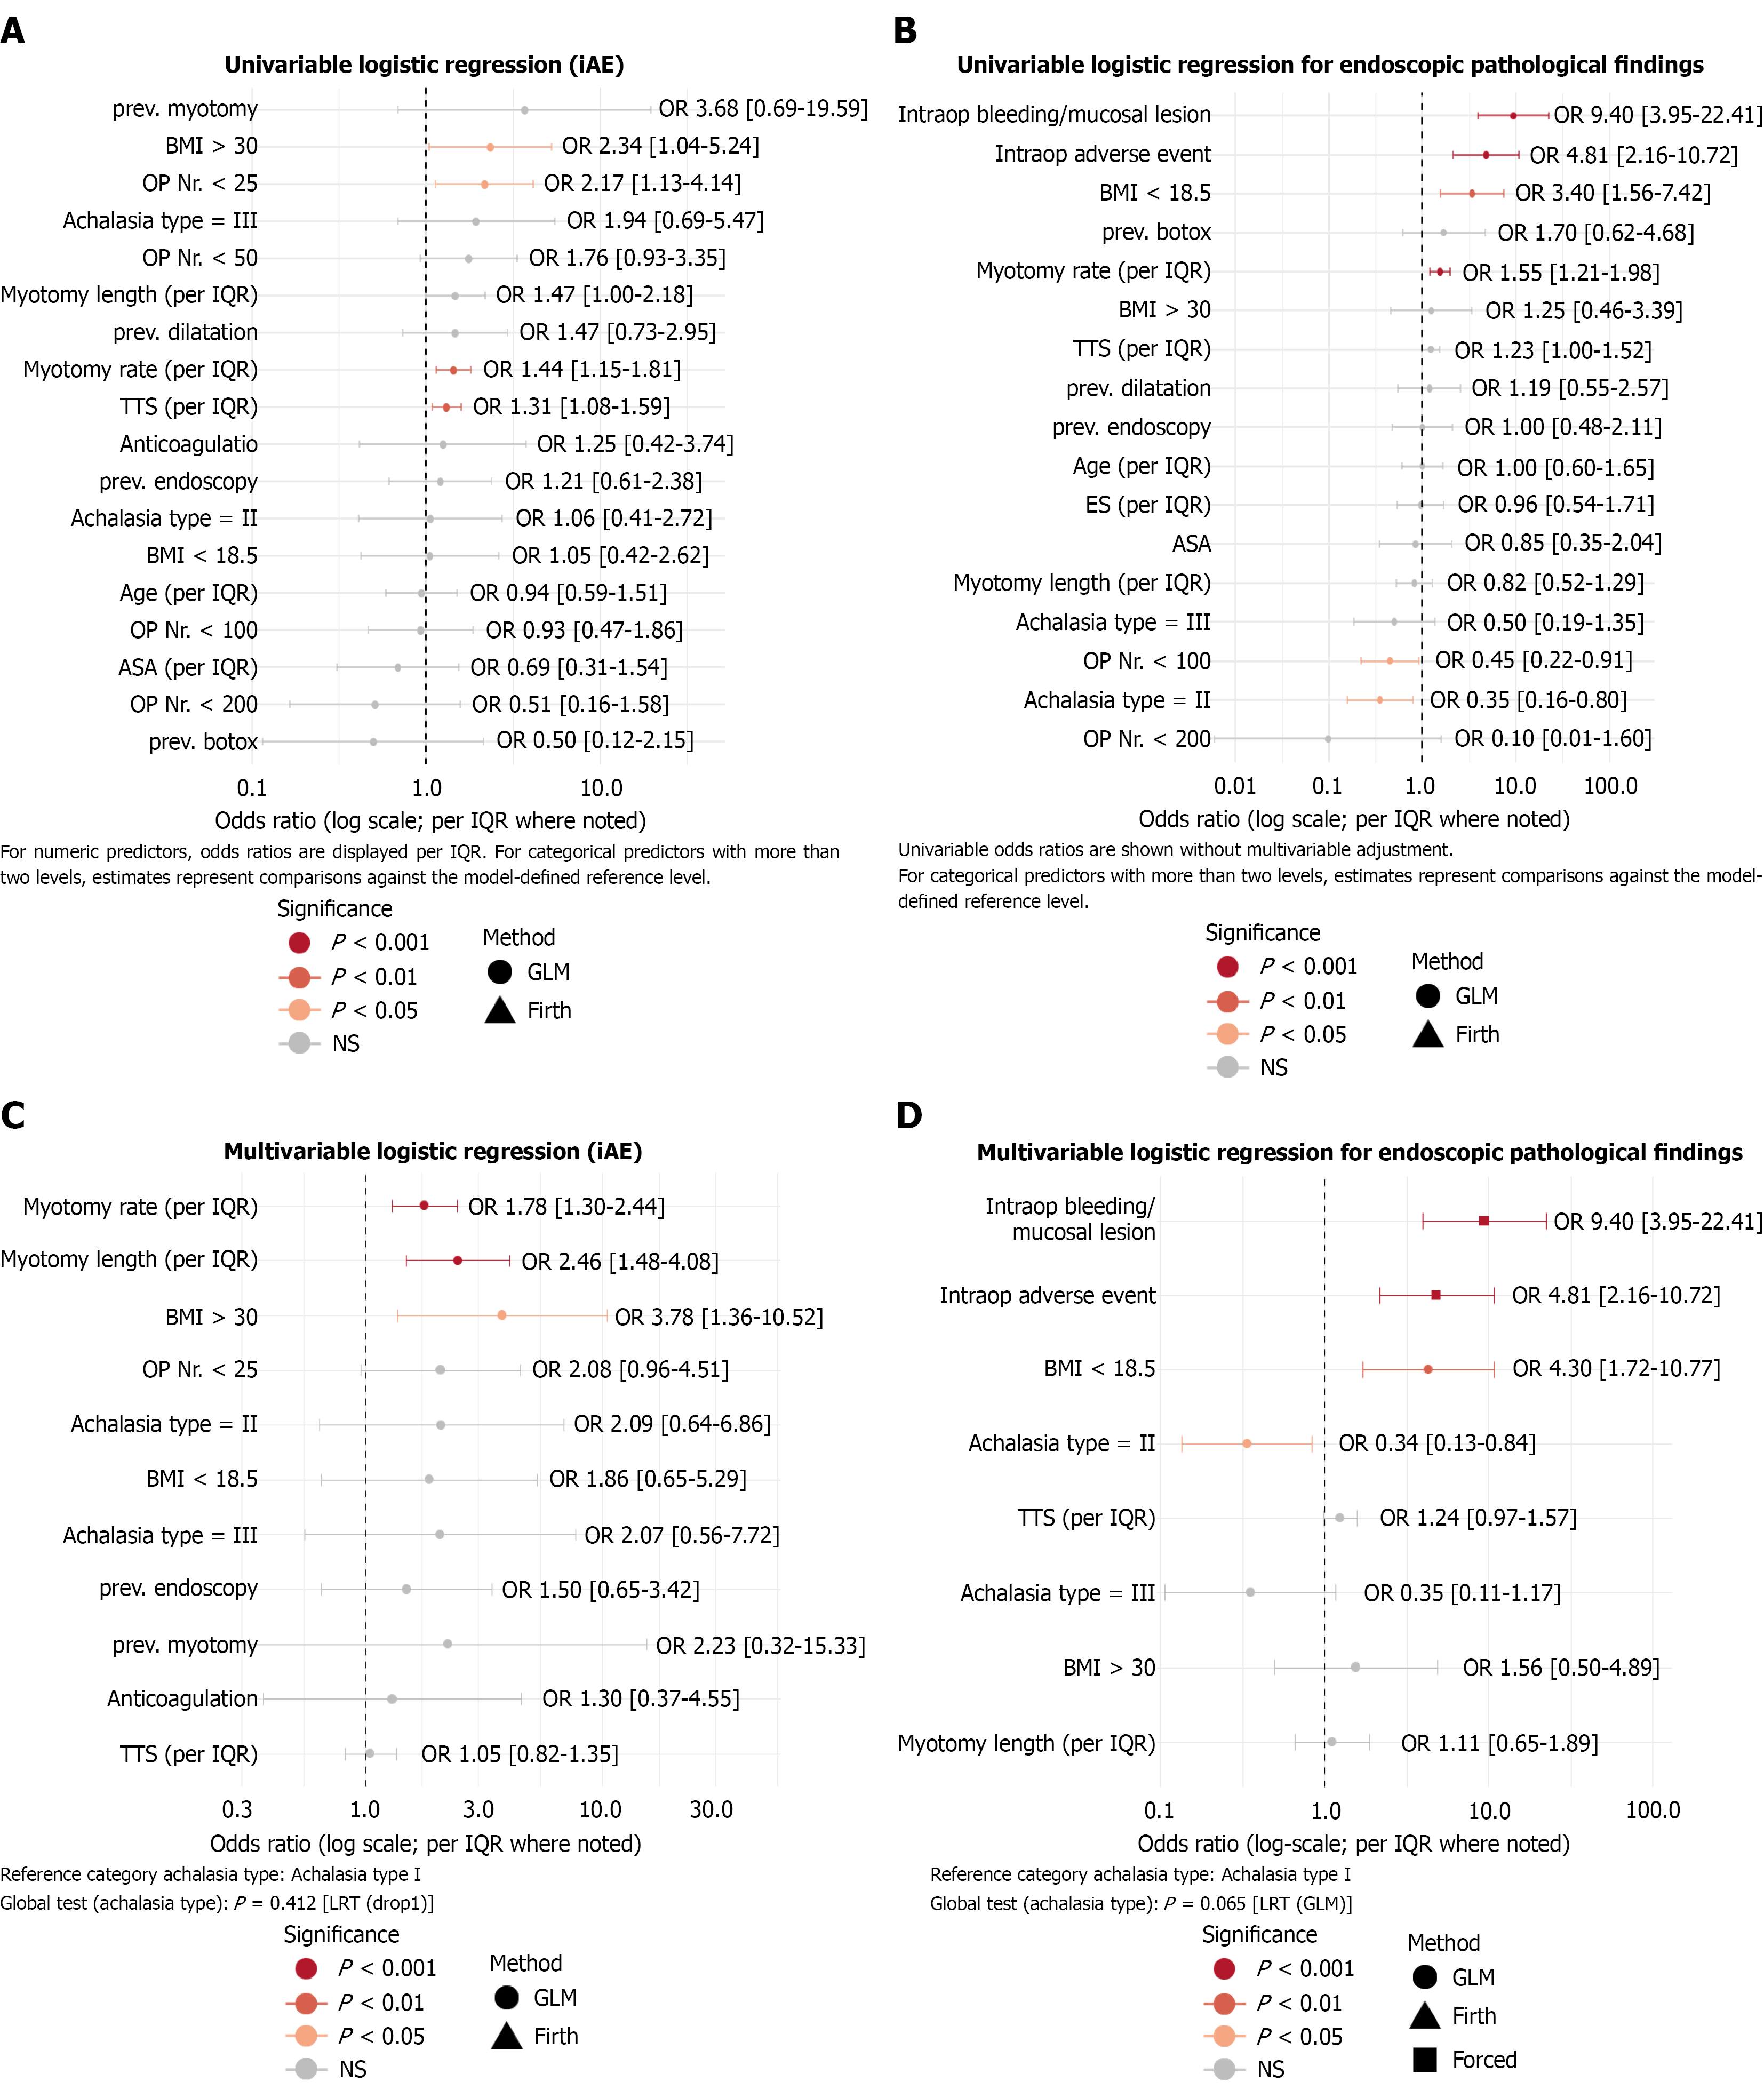
Figure 1 Forest plots of univariable and multivariable logistic regression analyses for intraoperative adverse events and pathological findings on postoperative endoscopy.
A and B: Odds ratios with 95% confidence intervals are shown for univariable models; C and D: Odds ratios with 95% confidence intervals are shown for multivariable models. Achalasia type was modeled as a categorical variable with three levels (types I-III), with type I serving as the reference category. Continuous variables are expressed per unit increase or per interquartile range, as indicated. Procedural experience thresholds, with the number of peroral endoscopic myotomy procedures performed at our center by a surgeon as markers of cumulative surgeon’s experience. iAE: Intraoperative adverse events; OR: Odds ratio; IQR: Interquartile range; GLM: Generalized linear model; BMI: Body mass index; myotomy rate: Time required to perform the myotomy, expressed as minutes per centimeter (minute/cm); prev. myotomy: Previous myotomy; OP Nr.: Cumulative number of procedures performed; prev. dilatation: Previous dilatation; prev. endoscopy: Any kind of previous endoscopic intervention (botox injection and/or dilatation) before the first peroral endoscopic myotomy at our center; TTS: Time to surgery (period from initial disease onset/initial diagnosis to first peroral endoscopic myotomy at our center); prev. botox: Previous botox injection; ASA: American Society of Anesthesiologists; LRT: Likelihood ratio test; ES: Eckardt score; NS: Not significant.
- Citation: Kastner C, Aktanova M, Kollmann L, Marschalek A, Meyer F, Anger J, Flemming I, Lauerer J, Weich A, Brand M, Hann A, von Rahden BH, Flemming S, Germer CT, Seyfried F. Role of postoperative endoscopy after peroral endoscopic myotomy: Evidence from a large cohort study. World J Gastroenterol 2026; 32(47): 122272
- URL: https://www.wjgnet.com/1007-9327/full/v32/i47/122272.htm
- DOI: https://dx.doi.org/10.3748/wjg.122272