
















Copyright: ©Author(s) 2026.
World J Gastroenterol. Nov 28, 2026; 32(44): 120736
Published online Nov 28, 2026. doi: 10.3748/wjg.120736
Published online Nov 28, 2026. doi: 10.3748/wjg.120736
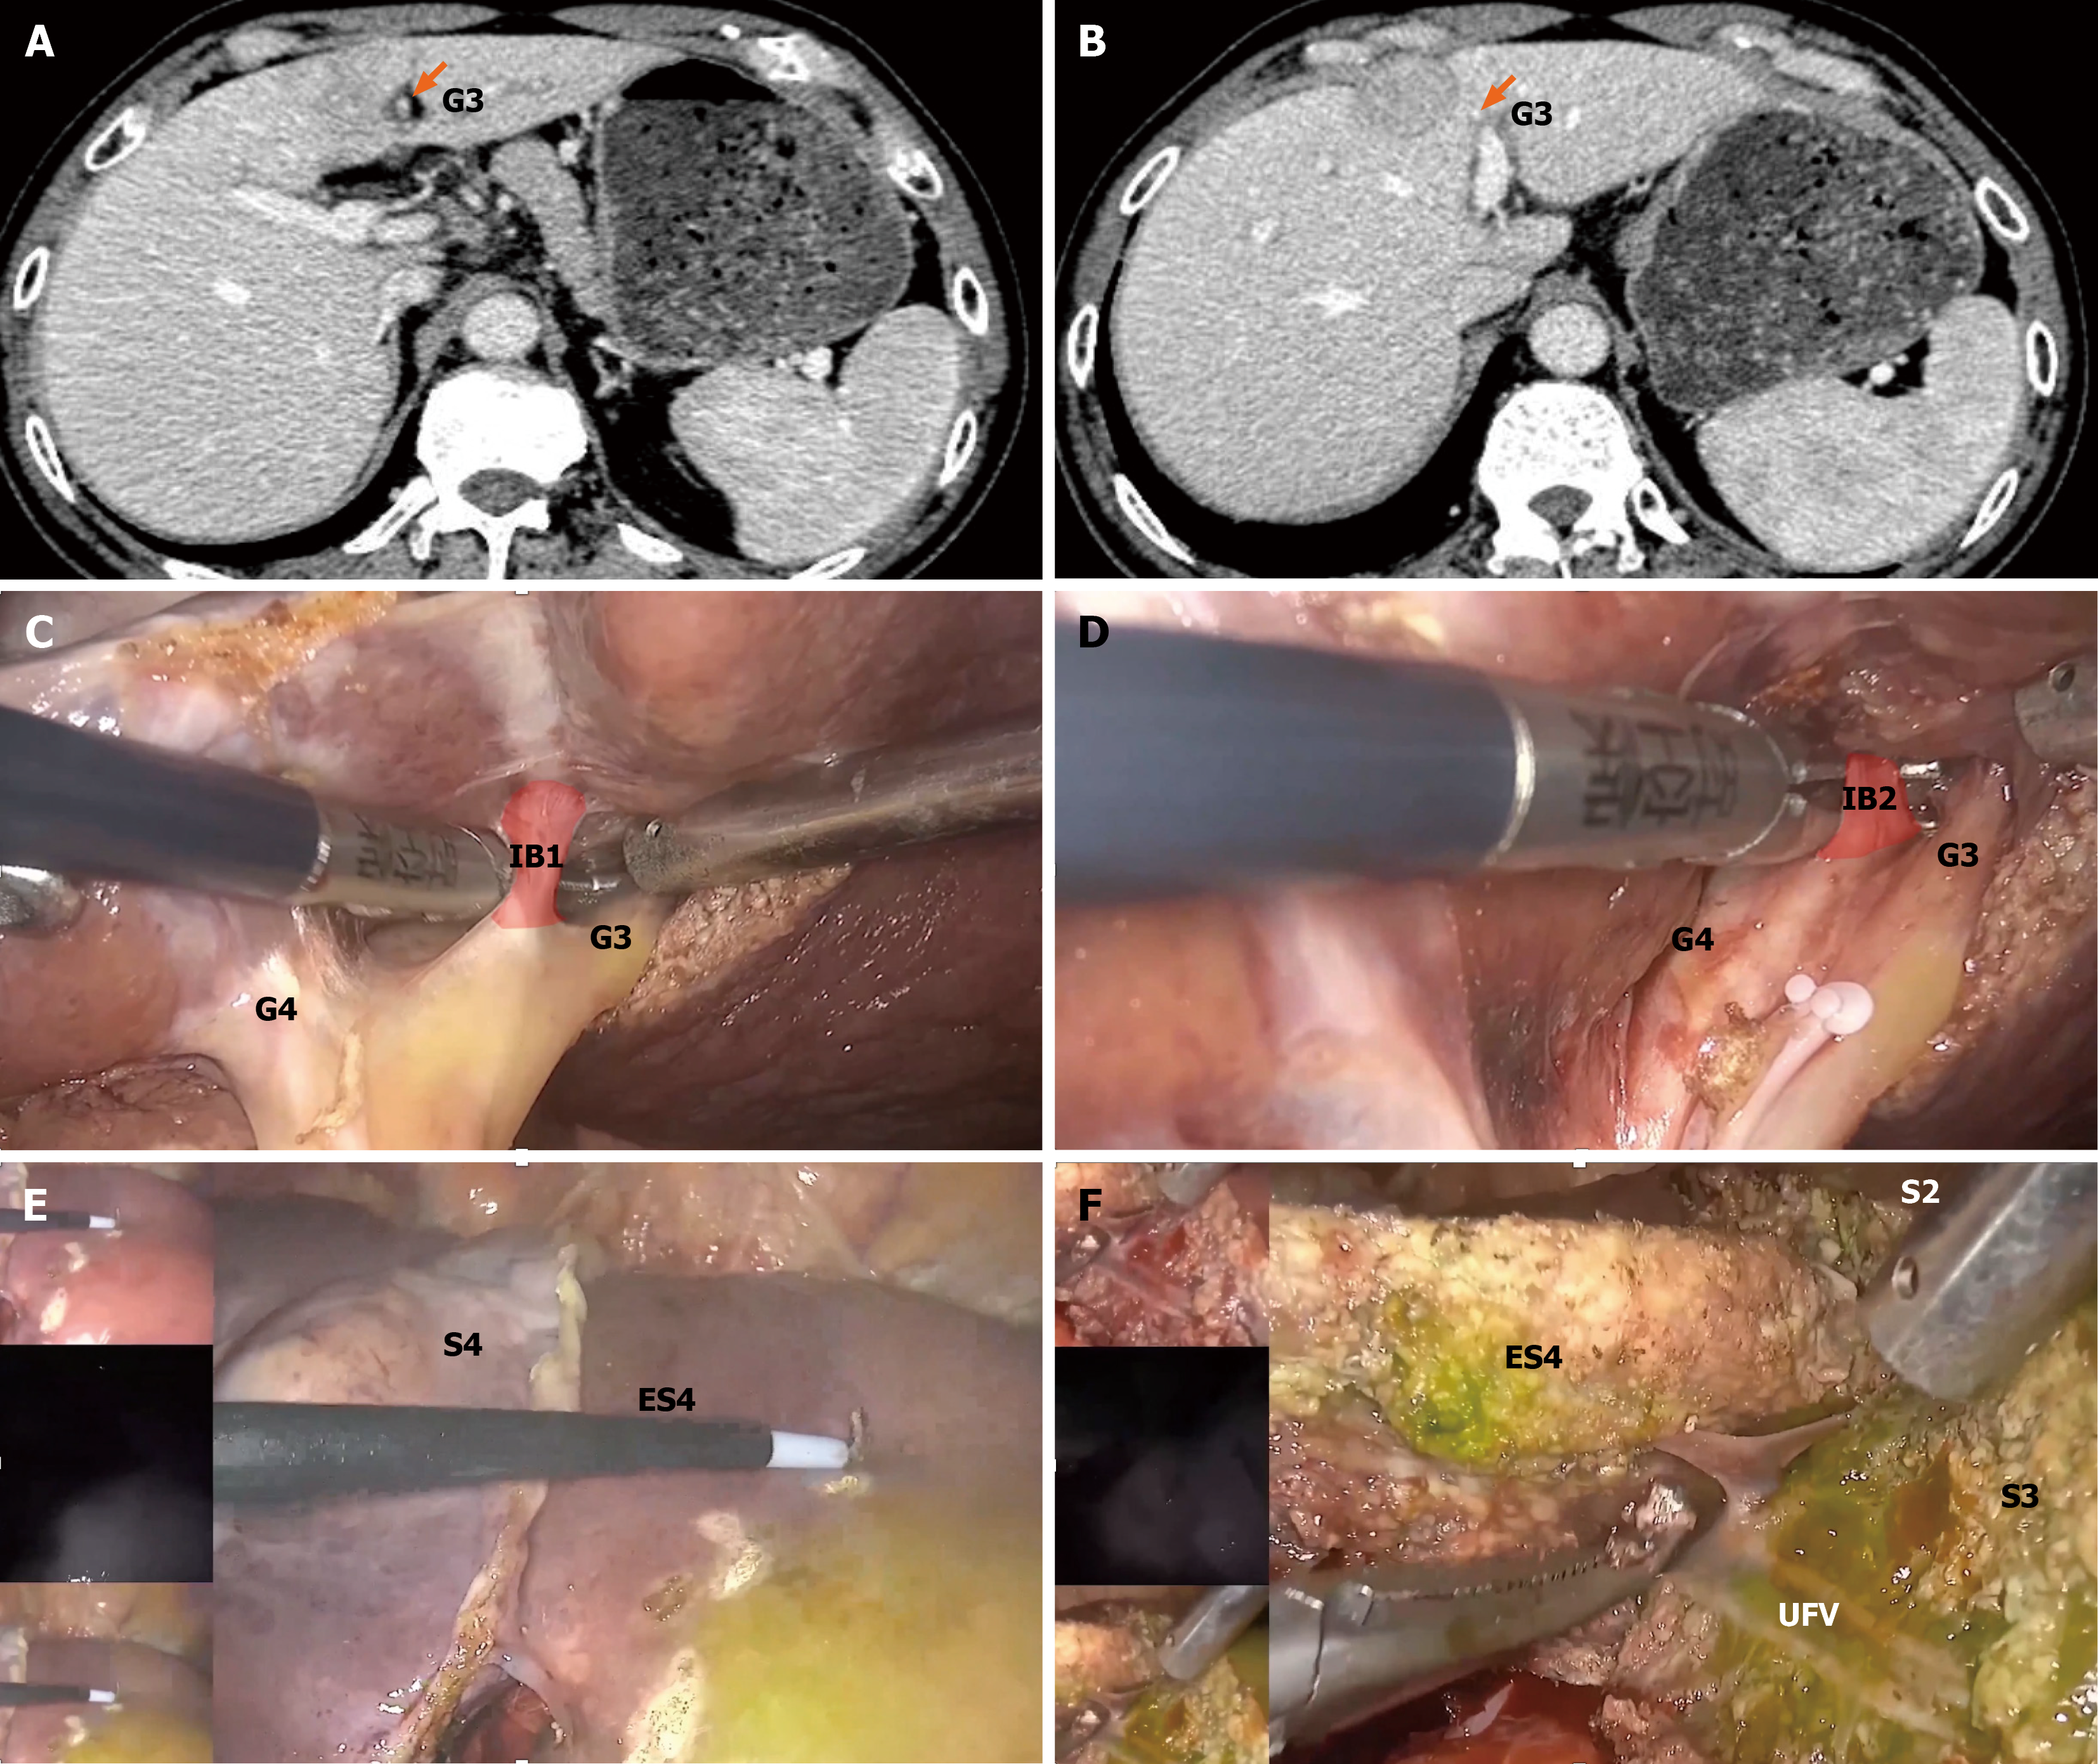
Figure 2 Portal territory-guided anatomical resection of extended segment 4.
A and B: Axial contrast-enhanced computed tomography images showing a lesion abutting the falciform ligament (orange arrows), a location that would typically require left hemihepatectomy under conventional anatomical definitions; C and D: Intraoperative laparoscopic views identifying two intermediate branches (IBs; IB1 and IB2) arising between the Glissonean pedicles of segments 3 and 4, supplying the parenchyma lateral to the falciform ligament; E: Indocyanine green (ICG) fluorescence negative staining delineating the extended segment 4 territory, corresponding to the perfusion zones of IB1 and IB2; F: Parenchymal transection guided by ICG staining and anatomical landmarks preserving segments 2 and 3, while achieving a negative surgical margin (R0). The umbilical fissure vein serves as a reference for the posterior limit of resection. IB: Intermediate branch; G3: Glissonean pedicles of segment 3; G4: Glissonean pedicles of segment 4; S2: Segment 2; S3: Segment 3; S4: Segment 4; ES4: Extended segment 4; UFV: Umbilical fissure vein serves.
- Citation: Huang K, Hu HY, Chen K, Chen XY, Chen Z, Sun Y, Du CY, Chang GX, Fu H, Hu C, Xiao H, Lan X. Portal vein-based subsegmental classification of liver segment four for parenchyma-sparing laparoscopic resection: A retrospective study. World J Gastroenterol 2026; 32(44): 120736
- URL: https://www.wjgnet.com/1007-9327/full/v32/i44/120736.htm
- DOI: https://dx.doi.org/10.3748/wjg.120736